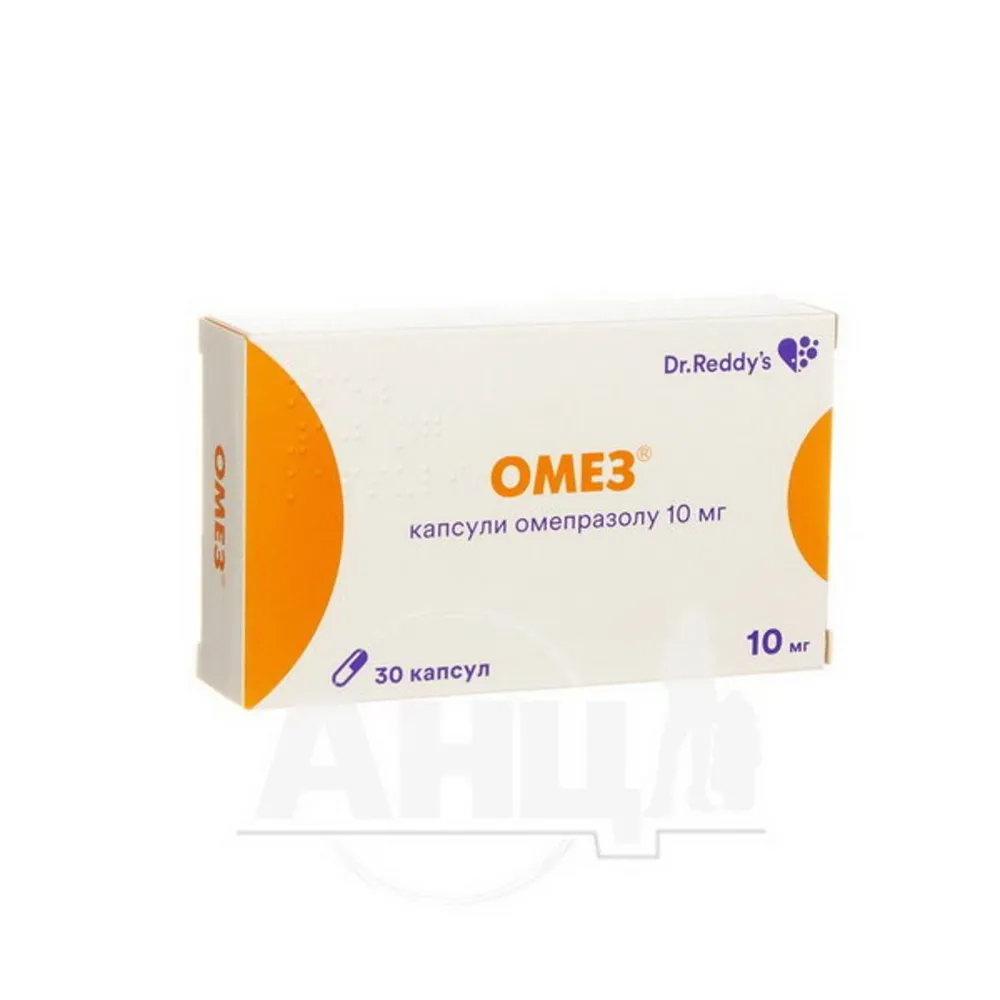
OMEZ
UkraineThe drug is used for the treatment and prevention of gastric and duodenal ulcers (including those caused by non-steroidal anti-inflammatory drugs), for the eradication of H. pylori bacteria in combination with antibiotics, for gastroesophageal reflux disease (reflux esophagitis), and Zollinger-Ellison syndrome. In children, it is prescribed for the treatment of reflux esophagitis and heartburn symptoms.
Frequently asked questions
How should Omez be taken correctly?
It is recommended to take the capsules in the morning, preferably before a meal, swallowing them with a small amount of water. The capsules must not be chewed or crushed. If the patient has difficulty swallowing, the contents of the capsule can be poured into semi-solid food (e.g., apple puree) or mixed with a non-acidic liquid (fruit juice, unsalted water) and consumed immediately.
What are the possible side effects of Omez?
The most frequent reactions include headache, abdominal pain, constipation, diarrhea, abdominal bloating, and nausea. Dizziness, dry mouth, skin rash, muscle weakness, or changes in vision are also possible. In rare cases, serious skin reactions, kidney dysfunction, or decreased magnesium levels in the body may occur.
Who should not take this drug?
The drug should not be used by people with hypersensitivity to omeprazole, other benzimidazoles, or any of the excipients included in the composition. Co-administration with nelfinavir is also contraindicated.
Does Omez affect the action of other medicines?
Yes, the drug may change the absorption of other agents. For example, it may reduce the effectiveness of ketoconazole, itraconazole, and erlotinib, but increase digoxin levels. Co-administration with clopidogrel and atazanavir is also not recommended.
Can the drug be used during pregnancy or breastfeeding?
Omeprazole can be used during pregnancy if the benefit to the mother outweighs the risk to the fetus. Since the drug passes into breast milk, it is recommended to discontinue breastfeeding during treatment.
Instructions for use
INSTRUCTION FOR MEDICAL USE OF THE MEDICINAL PRODUCT OMEZ® (OMEZ)
Composition:
Active ingredient: omeprazole;
1 capsule contains 40 mg of omeprazole;
Excipients: mannitol (E 421), crospovidone, poloxamer, hypromellose, meglumine, povidone, methacrylic acid copolymer (type C), triethyl citrate, magnesium stearate.
Pharmaceutical form. Capsules.
Main physico-chemical characteristics: nearly white to light-yellow pellets of elliptical and/or spherical shape contained in an opaque hard gelatin capsule size "0" with a yellow cap and a lavender-colored body, marked with black print “OMEZ 40” on both cap and body of the capsule.
Pharmacotherapeutic group. Drugs for treatment of peptic ulcer and gastroesophageal reflux disease. Proton pump inhibitors.
ATC code A02BC01.
Pharmacological Properties.
Pharmacodynamics.
Mechanism of action. Omeprazole, a racemic mixture of two enantiomers, reduces gastric acid secretion through a targeted mechanism of action. It is a specific inhibitor of the gastric proton pump in parietal cells. It acts rapidly and provides controlled, reversible suppression of gastric acid secretion with once-daily dosing.
Omeprazole is a weak base that accumulates and is converted into its active form in the acidic environment of intracellular canaliculi of parietal cells, where it inhibits the enzyme H+K+-ATPase—the acid pump. This effect on the final stage of gastric acid production is dose-dependent and results in highly effective suppression of both basal and stimulated acid secretion, regardless of the nature of the stimulus.
Pharmacodynamic effects. All observed pharmacodynamic effects can be explained by omeprazole's effect on acid secretion.
Effect on gastric acid secretion.
Oral administration of 20 mg omeprazole once daily leads to rapid and effective inhibition of daytime and nighttime gastric acid secretion, with maximum effect achieved within 4 days of treatment. In patients with duodenal ulcer, an average reduction in gastric acidity of approximately 80% occurs within 24 hours after taking 20 mg omeprazole. The average reduction in peak acid output following pentagastrin stimulation is about 70% at 24 hours after omeprazole administration.
Oral administration of 20 mg omeprazole maintains intragastric pH ≥ 3 for an average of 17 hours over a 24-hour period in patients with duodenal ulcer. Due to reduced acid secretion and intragastric acidity, in a dose-dependent manner, omeprazole reduces/normalizes esophageal acid exposure in patients with gastroesophageal reflux disease. Acid secretion inhibition correlates with the area under the plasma concentration-time curve (AUC) of omeprazole, rather than with actual plasma concentration at any given time.
No tachyphylaxis has been observed during omeprazole treatment.
Effect on H. pylori.
Peptic ulcer is associated with H. pylori, including duodenal and gastric ulcers. H. pylori is considered the primary causative factor in the development of gastritis. H. pylori and gastric acid are the main factors in the pathogenesis of peptic ulcer disease. H. pylori is a major factor in the development of atrophic gastritis, which is associated with an increased risk of gastric cancer.
Lowering of gastric pH with omeprazole in combination with antimicrobial agents is associated with rapid symptom relief, high healing rates of mucosal lesions, and long-term remission of peptic ulcer disease.
Other effects related to acid suppression.
During long-term treatment, a slightly increased frequency of gastric fundic gland polyps has been reported. These changes are a physiological consequence of sustained acid suppression, the polyps are benign, and appear to be reversible.
Reducing gastric acidity with any agent, including proton pump inhibitors, increases the number of bacteria normally present in the gastrointestinal tract. Treatment with acid-reducing agents may lead to a slightly increased risk of gastrointestinal infections, such as those caused by Salmonella and Campylobacter.
Pediatric use.
In an uncontrolled study involving children (aged 1 to 16 years) with severe erosive esophagitis, omeprazole at doses of 0.7–1.4 mg/kg improved esophagitis in 90% of cases and significantly reduced reflux symptoms. In a blinded study without a comparator, infants and toddlers aged 0 to 24 months diagnosed with gastroesophageal reflux disease were treated with omeprazole at doses of 0.5 mg/kg, 1.0 mg/kg, and 1.5 mg/kg. The frequency of vomiting/regurgitation episodes decreased by 50% after 8 weeks of treatment, regardless of dose.
Eradication of H. pylori in children.
In a randomized, double-blind clinical trial (the Héliot study), it was concluded that omeprazole in combination with two antibiotics (amoxicillin and clarithromycin) was safe and effective in treating H. pylori infection in children aged 4 years and older with gastritis: the H. pylori eradication rate was 74.2% (23/31 patients) in the omeprazole + amoxicillin + clarithromycin group, compared to 9.4% (3/32 patients) in the amoxicillin + clarithromycin group. However, no clinical benefit regarding dyspeptic symptoms was demonstrated. This study does not provide information on children under 4 years of age.
Pharmacokinetics.
Absorption. Omeprazole absorption is rapid, with peak plasma levels occurring approximately 1–2 hours after dose administration. Absorption of omeprazole occurs in the small intestine and is usually complete within 3–6 hours. Concomitant food intake does not affect bioavailability. Systemic availability (bioavailability) of omeprazole after a single oral dose is approximately 40%. After repeated once-daily administration, bioavailability increases to approximately 60%.
Distribution. The apparent volume of distribution in healthy individuals is approximately 0.3 L/kg body weight. Omeprazole plasma protein binding is 97%.
Metabolism. Omeprazole is completely metabolized by the cytochrome P450 system. The majority of omeprazole metabolism depends on CYP2C19, which is responsible for the formation of hydroxyomeprazole, the main metabolite in plasma. The remaining portion depends on another specific isoenzyme, CYP3A4, responsible for the formation of omeprazole sulfone. Due to the high affinity of omeprazole for CYP2C19, there is potential for competitive inhibition and metabolic interactions with other drugs that are substrates for CYP2C19. However, due to its low affinity for CYP3A4, omeprazole has no potential to inhibit the metabolism of other CYP3A4 substrates. Furthermore, omeprazole does not inhibit major CYP enzymes.
Approximately 3% of the Caucasian population and 15–20% of Asian populations lack functional CYP2C19 enzyme. In these individuals, omeprazole metabolism is likely primarily catalyzed by CYP3A4. After repeated once-daily administration of 20 mg omeprazole, the mean AUC was 5–10 times higher in poor metabolizers than in individuals with functional CYP2C19 (extensive metabolizers). Mean peak plasma concentrations were also 3–5 times higher. These observations have no relevance to omeprazole dosing.
Elimination. The terminal half-life of omeprazole in plasma is typically less than 1 hour, both after single and multiple once-daily oral doses. Omeprazole is completely cleared from plasma between doses, with no tendency for accumulation during once-daily administration. Approximately 80% of an oral dose of omeprazole is excreted in urine as metabolites, and the remainder is excreted in feces, primarily via biliary secretion.
With repeated administration, the AUC of omeprazole increases. This increase is dose-dependent and results in a non-linear relationship between dose and AUC after repeated dosing. This time- and dose-dependence is related to reduced presystemic metabolism and systemic clearance, possibly due to inhibition of the CYP2C19 enzyme by omeprazole and/or its metabolites (e.g., sulfone).
No metabolite has been found to have any effect on gastric acid secretion.
Special populations. Hepatic impairment. In patients with impaired liver function, omeprazole metabolism is altered, leading to increased AUC. Omeprazole has not shown any tendency toward accumulation with once-daily dosing.
Renal impairment. The pharmacokinetics of omeprazole, including systemic bioavailability and elimination rate, are not altered in patients with reduced renal function.
Elderly patients. The rate of omeprazole metabolism is slightly reduced in elderly patients (75–79 years).
Children. Plasma concentrations similar to those in adults are achieved in children aged 1 year and older when treated with recommended doses. In children under 6 months of age, omeprazole clearance is low due to limited capacity to metabolize omeprazole.
Clinical characteristics.
Indications.
For adults:
-
treatment and prevention of recurrence of duodenal ulcer and benign gastric ulcer, including those associated with the use of nonsteroidal anti-inflammatory drugs (NSAIDs);
-
eradication of Helicobacter pylori (H. pylori) in peptic ulcer disease in combination with appropriate antibiotics;
-
treatment of gastroesophageal reflux disease (GERD), including reflux esophagitis;
-
treatment of Zollinger–Ellison syndrome.
For children:
Children aged 1 year and older with body weight over 10 kg:
-
treatment of reflux esophagitis;
-
symptomatic treatment of heartburn and acid regurgitation in gastroesophageal reflux disease.
Children aged 4 years and older:
- treatment of duodenal ulcer caused by H. pylori, in combination with antibiotics.
Contraindications.
Hypersensitivity to omeprazole, substituted benzimidazoles, or to any excipient. Omeprazole, like other proton pump inhibitors (PPIs), should not be used concomitantly with nelfinavir (see "Interaction with other medicinal products and other forms of interaction").
Interaction with other medicinal products and other forms of interaction.
Effect of omeprazole on the pharmacokinetics of other medicinal products.
Medicinal products whose absorption depends on gastric pH.
Suppression of gastric acid secretion during treatment with omeprazole and other PPIs may reduce or increase the absorption of drugs whose absorption is pH-dependent. As with other agents that reduce gastric acidity, absorption of drugs such as ketoconazole, itraconazole, and erlotinib may be decreased, whereas absorption of drugs such as digoxin may be increased during omeprazole treatment. Concomitant administration of omeprazole (20 mg once daily) and digoxin in healthy volunteers increased digoxin bioavailability by 10% (in two out of ten subjects, by up to 30%).
Nelfinavir, atazanavir.
Plasma levels of nelfinavir and atazanavir are reduced when administered concomitantly with omeprazole.
Concomitant use of omeprazole and nelfinavir is contraindicated. Co-administration of omeprazole (40 mg once daily) reduced the average exposure to nelfinavir by approximately 40%, and the exposure to its pharmacologically active metabolite M8 decreased by approximately 75–90%. This interaction may also be due to inhibition of CYP2C19 activity.
Concomitant use of omeprazole with atazanavir is not recommended. Co-administration of omeprazole (40 mg once daily) with atazanavir 300 mg/ritonavir 100 mg in healthy volunteers resulted in a 75% reduction in atazanavir exposure. Increasing the atazanavir dose to 400 mg did not compensate for the effect of omeprazole on atazanavir exposure. Concomitant administration of omeprazole (20 mg once daily) with atazanavir 400 mg/ritonavir 100 mg in healthy volunteers resulted in approximately 30% lower atazanavir exposure compared to atazanavir 300 mg/ritonavir 100 mg once daily.
Digoxin.
Concomitant treatment with omeprazole (20 mg daily) and digoxin in healthy volunteers increased digoxin bioavailability by 10%. Rare cases of digoxin toxicity have been reported. However, caution should be exercised when prescribing high doses of omeprazole to elderly patients. Therapeutic drug monitoring of digoxin should be intensified.
Clopidogrel.
In a cross-over clinical study, clopidogrel (loading dose 300 mg followed by 75 mg/day) was administered alone and together with omeprazole (80 mg administered simultaneously with clopidogrel) for 5 days. When clopidogrel and omeprazole were used concomitantly, exposure to the active metabolite of clopidogrel decreased by 46% (day 1) and by 42% (day 5). Mean inhibition of platelet aggregation was reduced by 47% (after 24 hours) and by 30% (day 5) when clopidogrel and omeprazole were administered together. Another study showed that administering clopidogrel and omeprazole at different times did not prevent their interaction, likely due to omeprazole's inhibitory effect on CYP2C19. Conflicting data on the clinical significance of this pharmacokinetic/pharmacodynamic (PK/PD) interaction regarding major cardiovascular events have been reported in observational and clinical studies.
Other medicinal products.
Absorption of posaconazole, erlotinib, ketoconazole, and itraconazole is significantly reduced, and thus clinical efficacy may be diminished. Concomitant use with posaconazole and erlotinib should be avoided.
Medicinal products metabolized by CYP2C19.
Omeprazole is a moderate inhibitor of CYP2C19, the main enzyme responsible for omeprazole metabolism. Therefore, metabolism of concomitantly administered drugs that are also metabolized by CYP2C19 may be reduced, and systemic exposure to these drugs may increase. Examples include R-warfarin and other vitamin K antagonists, cilostazol, diazepam, and phenytoin.
In healthy volunteers, a pharmacokinetic/pharmacodynamic interaction was observed between clopidogrel (loading dose 300 mg/maintenance dose 75 mg daily) and omeprazole (80 mg daily orally, i.e., a dose four times higher than the standard daily dose), resulting in a mean 46% reduction in exposure to the active metabolite of clopidogrel and a mean 16% reduction in maximum inhibitory effect (ADP-induced platelet aggregation). The clinical significance of this interaction remains unclear. As a precautionary measure, concomitant use of omeprazole and clopidogrel should be avoided.
Cilostazol.
In healthy volunteers, administration of omeprazole 40 mg increased the Cmax and AUC of cilostazol by 18% and 26%, respectively, and of one of its active metabolites by 29% and 69%, respectively.
Phenytoin.
Plasma phenytoin concentration monitoring is recommended during the first two weeks after initiating omeprazole treatment. If phenytoin dosage adjustment has been made, monitoring and further dose adjustments should be performed after discontinuation of omeprazole.
Unknown mechanism.
Saquinavir.
Concomitant administration of omeprazole with saquinavir/ritonavir increased saquinavir plasma levels by approximately 70%, which was associated with acceptable tolerability in HIV-infected patients.
Tacrolimus.
Increased serum tacrolimus levels have been reported with concomitant use of omeprazole. Intensified monitoring of tacrolimus concentration and renal function (creatinine clearance) is required, and dose adjustment of tacrolimus may be necessary.
Methotrexate.
Elevated methotrexate levels have been reported in some patients when co-administered with proton pump inhibitors. In cases where high-dose methotrexate is required, temporary discontinuation of omeprazole should be considered.
Effect of other medicinal products on the pharmacokinetics of omeprazole.
Inhibitors of CYP2C19 and/or CYP3A4.
Since omeprazole is metabolized by CYP2C19 and CYP3A4 enzymes, medicinal products known to inhibit the activity of CYP2C19 or CYP3A4 or both enzymes (such as clarithromycin and voriconazole) may increase omeprazole serum levels due to reduced metabolic rate. Concomitant administration of voriconazole led to more than a twofold increase in omeprazole exposure. Since high doses of omeprazole are generally well tolerated, dose adjustment of omeprazole is usually not required. However, dose adjustment should be considered in patients with severe hepatic impairment and in cases of long-term treatment.
Omeprazole is partially metabolized by CYP3A4 as well, but does not inhibit this enzyme. Therefore, omeprazole does not affect the metabolism of drugs metabolized by CYP3A4, such as cyclosporine, lidocaine, quinidine, estradiol, erythromycin, and budesonide.
Inducers of CYP2C19 and/or CYP3A4.
Medicinal products known to induce the activity of CYP2C19 or CYP3A4 or both enzymes (such as rifampicin and St. John’s wort) may reduce omeprazole serum levels due to accelerated metabolism.
Special precautions for use.
In the presence of any alarming symptom (e.g., significant unintentional weight loss, frequent vomiting, dysphagia, hematemesis, or melena) in a patient with gastric ulcer or suspected gastric ulcer, malignancy should be excluded, as the use of the medicinal product may mask its symptoms and delay correct diagnosis.
Concomitant use of atazanavir with proton pump inhibitors is not recommended. If a combination of atazanavir with a proton pump inhibitor cannot be avoided, careful clinical monitoring (e.g., viral load) combined with an increased dose of atazanavir to 400 mg with 100 mg ritonavir is recommended; the dose of omeprazole should not exceed 20 mg.
Omeprazole, like all medicinal products that suppress gastric acid secretion, may reduce absorption of vitamin B12 (cyanocobalamin) due to hypo- or achlorhydria. This should be considered in patients with cachexia or risk factors for reduced vitamin B12 absorption during long-term therapy.
Omeprazole is an inhibitor of CYP2C19. At the beginning or end of omeprazole treatment, potential interactions with medicinal products metabolized by CYP2C19 should be considered. An interaction has been observed between clopidogrel and omeprazole. The clinical significance of this interaction remains unclear. As a precautionary measure, concomitant use of omeprazole and clopidogrel should be avoided.
In patients taking proton pump inhibitors, including omeprazole, for at least three months, clinically significant hypomagnesemia may occur (in most cases, patients had been taking the drug for about one year). Hypomagnesemia may be suspected based on serious manifestations such as fatigue, muscle spasms, seizures, delirium, dizziness, or ventricular arrhythmias. However, it should be noted that in some cases, symptoms may be masked, which may delay timely recognition of this complication. In most patients, symptoms of hypomagnesemia resolve and levels normalize after administration of magnesium supplements and discontinuation of proton pump inhibitors.
Prolonged reduction in gastric acidity may lead to increased bacterial counts in the gastrointestinal tract.
Treatment with proton pump inhibitors may lead to a slightly increased risk of gastrointestinal infections caused by Salmonella and Campylobacter.
In healthy volunteers, a pharmacokinetic/pharmacodynamic interaction between clopidogrel (loading dose 300 mg/daily maintenance dose – 75 mg) and omeprazole (80 mg daily orally, i.e., a dose four times higher than the standard daily dose) was observed, resulting in a mean reduction of 46% in exposure to the active metabolite of clopidogrel and a mean reduction of 16% in maximum inhibitory effect (ADP-induced) on platelet aggregation.
Some data suggest that proton pump inhibitor therapy may be associated with a small increased risk of osteoporosis-related fractures. Although a causal relationship between omeprazole/esomeprazole and osteoporotic fracture has not been established, patients at risk of progressive osteoporosis or osteoporotic fracture should be recommended appropriate clinical monitoring according to current clinical guidelines for this condition.
During treatment with antisecretory agents, plasma gastrin concentration increases as a result of reduced hydrochloric acid secretion. Due to decreased hydrochloric acid secretion, chromogranin A (CgA) levels increase. Elevated CgA levels may affect test results for detecting neuroendocrine tumors. To prevent such interference, proton pump inhibitor therapy should be discontinued at least 5 days before measuring CgA levels. If CgA and gastrin levels have not returned to reference ranges after initial measurements, these parameters should be re-measured 14 days after discontinuation of proton pump inhibitor therapy.
For treatment of chronic conditions in children, the drug should not be used longer than recommended.
As with all long-term treatments, especially when the treatment period lasts more than one year, the patient should be under regular medical supervision.
Subacute cutaneous lupus erythematosus (SCLE)
Use of proton pump inhibitors may be associated with very rare cases of SCLE. If skin lesions, particularly in sun-exposed areas, occur and are accompanied by arthralgia, the patient should seek immediate medical attention, and the healthcare provider should consider discontinuing omeprazole. SCLE following prior treatment with a proton pump inhibitor may increase the risk of developing SCLE upon subsequent use of other proton pump inhibitors.
Risk of allergic reactions
Omeprazole may cause serious skin reactions. Symptoms may include: skin redness, blistering, rash (see section "Adverse reactions").
If a patient experiences an allergic reaction, they should discontinue the medicinal product and seek immediate medical attention.
Renal function impairment
Acute tubulointerstitial nephritis (ATIN) has been reported in patients taking omeprazole. It may occur at any time during omeprazole therapy. Acute tubulointerstitial nephritis may progress to renal failure.
If ATIN is suspected, omeprazole should be discontinued and appropriate treatment initiated immediately.
Use during pregnancy or breastfeeding. Research findings indicate no adverse effects of omeprazole on pregnancy, fetal health, or newborn infants. Omeprazole may be used during pregnancy if the expected benefit to the mother outweighs the potential risk to the fetus. Omeprazole passes into breast milk in small amounts, but its effect on the infant is unknown; therefore, breastfeeding should be discontinued during treatment with the drug.
Ability to affect reaction speed when driving or operating machinery. It is unlikely that the medicinal product affects the ability to drive vehicles or operate machinery. Undesirable reactions such as dizziness and visual disturbances may occur (see section "Adverse reactions"). If such disorders occur, patients should not drive vehicles or operate machinery.
Administration and Dosage.
Dosage for adults.
Treatment and prevention of duodenal ulcer and benign gastric ulcer, including those associated with use of nonsteroidal anti-inflammatory drugs (NSAIDs).
The recommended dose for patients with duodenal ulcer is 20 mg of omeprazole once daily. In most patients, duodenal ulcer heals within 2 weeks. For patients who do not achieve complete healing after the initial course, an additional 2 weeks of treatment is recommended. In severe or recurrent cases, 40 mg of omeprazole daily is recommended, and healing is usually achieved within 4 weeks.
For prevention of recurrence of duodenal ulcer in patients with a negative H. pylori test, the recommended dose is 20 mg of omeprazole once daily. A daily dose of 10 mg may be sufficient for some patients. In case of inadequate response, the dose may be increased to 40 mg.
In the treatment of gastric ulcer, the recommended dose is 20 mg of omeprazole once daily. In most patients, gastric ulcer heals within 4 weeks. Patients who do not achieve complete healing after the initial course are recommended to continue treatment for an additional 4 weeks. In severe or recurrent cases, 40 mg of omeprazole daily is recommended, and healing is usually achieved within 8 weeks.
For prevention of recurrence in patients with gastric ulcer and insufficient response to treatment, the recommended dose is 20 mg of omeprazole once daily. If necessary, the dose may be increased to 40 mg once daily.
For treatment of gastric and duodenal ulcers associated with use of nonsteroidal anti-inflammatory drugs, the recommended dose is 20 mg of omeprazole once daily. In most patients, healing occurs within 4 weeks. Patients who do not achieve complete healing after the initial course are recommended to continue treatment for an additional 4 weeks.
For prevention of gastric and duodenal ulcers associated with use of nonsteroidal anti-inflammatory drugs in patients at increased risk (age > 60, history of gastric or duodenal ulcers, upper gastrointestinal bleeding), the recommended dose is 20 mg of omeprazole once daily.
Eradication of H. pylori in peptic ulcer disease.
When selecting antibacterial agents for H. pylori eradication, individual drug tolerability should be considered, and local treatment guidelines should be followed.
- Omeprazole 20 mg + clarithromycin 500 mg + amoxicillin 1000 mg twice daily for 1 week, or
- Omeprazole 20 mg + clarithromycin 250 mg (if necessary, 500 mg) + metronidazole 400 mg (if necessary, 500 mg) or tinidazole 500 mg, twice daily for 1 week, or
- Omeprazole 40 mg once daily + amoxicillin 500 mg + metronidazole 400 mg (if necessary, 500 mg) or tinidazole 500 mg, three times daily for 1 week.
Treatment of gastroesophageal reflux disease, including reflux esophagitis.
The recommended dose is 20 mg of omeprazole once daily. In most patients, recovery occurs within 4 weeks. Patients who do not achieve complete recovery after the initial course are recommended to continue treatment for an additional 4 weeks. For patients with severe esophagitis, 40 mg of omeprazole daily is recommended, with recovery usually achieved within 8 weeks.
For long-term treatment of patients with gastroesophageal reflux disease, the recommended dose is 10 mg of omeprazole once daily. If necessary, the dose may be increased to 20–40 mg of omeprazole once daily.
For treatment of symptoms of gastroesophageal reflux disease, the recommended dose is 20 mg of omeprazole once daily. A dose of 10 mg may be sufficient for some patients. The dose should be adjusted individually. If the desired effect is not achieved after 4 weeks of treatment with 20 mg of omeprazole daily, the patient should be further examined.
Treatment of Zollinger–Ellison syndrome.
Dosage for patients with Zollinger–Ellison syndrome should be individually adjusted. Treatment continues until clinical manifestations disappear. The recommended initial dose is 60 mg of omeprazole once daily. Observations in over 90% of patients with severe disease and insufficient response to other treatments have shown the effectiveness of maintenance therapy with doses of 20–120 mg daily. Daily doses exceeding 80 mg should be divided and administered in two doses.
Dosage for children.
Children aged 1 year and older with body weight ≥ 10 kg.
Treatment of reflux esophagitis.
Symptomatic treatment of heartburn and acid regurgitation in gastroesophageal reflux disease.
Dosage recommendations:
| Age |
Body weight |
Dosage |
| ≥ 1 year |
10–20 kg |
10 mg once daily. If necessary, the dose can be increased to 20 mg once daily. |
| Children with body weight over 20 kg |
20 mg once daily. If necessary, the dose can be increased to 40 mg once daily. |
|
Treatment of reflux esophagitis: treatment duration is 4–8 weeks.
Symptomatic treatment of heartburn and acid regurgitation in gastroesophageal reflux disease: treatment duration is 2–4 weeks. If the desired result is not achieved after 2–4 weeks, the patient should be further examined.
Children and adolescents aged 4 years and older.
Treatment of duodenal ulcer caused by H. pylori.
Selection of an appropriate combination therapy should follow official national, regional, and local guidelines regarding bacterial resistance. The duration of treatment (from 7 to 14 days) and proper use of antibacterial agents should also be considered. Treatment must be conducted under physician supervision.
Dosing recommendations:
| Body weight |
Dosage |
| 15–30 kg |
Omeprazole 10 mg + amoxicillin 25 mg/kg body weight + clarithromycin 7.5 mg/kg body weight. Take the medications together twice daily for 1 week |
| 31–40 kg |
Omeprazole 20 mg + amoxicillin 750 mg + clarithromycin 7.5 mg/kg body weight. Take the medications together twice daily for 1 week. |
| > 40 kg |
Omeprazole 20 mg + amoxicillin 1000 mg + clarithromycin 500 mg. Take the medications together twice daily for 1 week. |
If a dose of 10 mg or 20 mg is required, use the preparation in the corresponding dosage strength.
Special patient groups.
Renal impairment. Dose adjustment is not required in patients with renal impairment (see section "Pharmacokinetics").
Hepatic impairment. In patients with hepatic impairment, a daily dose of 10–20 mg is sufficient (see section "Pharmacokinetics").
Elderly patients (>65 years of age). Dose adjustment is not required in elderly patients (see section "Pharmacokinetics").
It is recommended to take the capsules in the morning, preferably before a meal, without damaging the capsule (capsules must not be chewed or crushed), with a small amount of water.
For patients with swallowing difficulties and for children who can drink or swallow semisolid food. The capsules may be opened and the contents swallowed directly, followed by half a glass of water, or mixed with a weakly acidic liquid, such as any fruit juice or apple puree, or in unsalted water. This mixture should be taken immediately after preparation or within 30 minutes. Before administration, the mixture should be stirred and followed by half a glass of water. Milk or carbonated water must not be used.
Children. The medicinal product may be administered to children aged 1 year and older with body weight above 10 kg, under medical supervision, for the indication of reflux esophagitis and symptomatic treatment of heartburn and acid regurgitation in gastroesophageal reflux disease, and to children aged 4 years and older for the treatment of duodenal ulcer associated with H. pylori, under medical supervision.
Overdose. Data on the effects of omeprazole overdose in humans are very limited. In scientific literature, there have been reports of omeprazole doses up to 560 mg, and isolated cases of single oral doses reaching 2400 mg omeprazole (120 times higher than the usual recommended clinical dose). Symptoms reported include nausea, vomiting, dizziness, abdominal pain, diarrhea, and headache. In isolated cases, lethargy, depression, and confusion have also been reported.
The described symptoms are transient in nature. Elimination kinetics remain unchanged (first-order kinetics) with increasing dose. Treatment, if necessary, is symptomatic.
Adverse reactions.
The most commonly observed adverse effects are headache, abdominal pain, constipation, diarrhea, bloating, and nausea/vomiting. The adverse reactions listed below were identified during clinical trials with omeprazole or from post-marketing experience. Adverse reactions are classified according to system organ classes.
Blood and lymphatic system disorders: leukopenia, thrombocytopenia, agranulocytosis, pancytopenia.
Immune system disorders: hypersensitivity reactions, e.g., fever, angioedema, anaphylactic reaction/shock.
Metabolism and nutrition disorders: hyponatremia, hypomagnesemia; severe hypomagnesemia may lead to hypocalcemia. Hypomagnesemia may also be associated with hypokalemia.
Psychiatric disorders: insomnia, agitation, confusion, depression, aggression, hallucinations.
Nervous system disorders: headache, dizziness, paresthesia, somnolence, taste disturbance.
Eye disorders: blurred vision.
Ear and labyrinth disorders: tinnitus, vertigo.
Respiratory, thoracic and mediastinal disorders: bronchospasm.
Gastrointestinal disorders: abdominal pain, constipation, diarrhea, bloating, nausea/vomiting, dry mouth, stomatitis, gastrointestinal candidiasis, microscopic colitis, fundic gland polyps (benign).
Hepatobiliary disorders: increased liver enzymes, hepatitis with or without jaundice, hepatic failure, encephalopathy in patients with pre-existing liver disease.
Skin and subcutaneous tissue disorders: dermatitis, pruritus, erythema, vesicles, rash, urticaria, alopecia, photosensitivity, polymorphic erythema, Stevens-Johnson syndrome, toxic epidermal necrolysis, subacute cutaneous lupus erythematosus (see section "Special precautions").
Musculoskeletal and connective tissue disorders: arthralgia, myalgia, muscle weakness, increased risk of fractures with long-term use (see section "Special precautions").
Renal and urinary disorders: tubulointerstitial nephritis (with possible progression to renal failure).
Reproductive system and breast disorders: gynecomastia.
General disorders: discomfort, malaise, peripheral edema, increased sweating.
Pediatric population.
The safety of omeprazole has been evaluated in 310 children aged 0 to 16 years with acid-related disorders. Limited data are available from long-term safety studies in 46 children who received maintenance therapy with omeprazole for the treatment of severe erosive esophagitis over 749 days. The adverse reaction profile is similar to that observed in adults during both short-term and long-term treatment. There are no long-term data on the effects of omeprazole treatment on sexual maturation and growth.
Shelf life. 3 years.
Storage conditions. Store in the original packaging, protected from light, at a temperature not exceeding 25 °C. Keep out of the reach of children.
Packaging. 10 capsules per blister, 1 or 3 blisters per cardboard box. 7 capsules per blister, 4 blisters per cardboard box.
Prescription status. Prescription only.
Manufacturer. Dr. Reddy’s Laboratories Ltd, FTO – 3
Manufacturer’s address. Survey Nos. 41, 42R, 45R and 46R, Bachupally and Mandal, Medchal-Malkajgiri District – 500090, Telangana, India
Similar drugs
| Brand name | Dosage form | Active substance / Dosage | Manufacturer |
|---|---|---|---|
| OMEPRAZOLE | capsules |
|
PJSC "Kyivmedpreparat" |
| OMEPRAZOLE | capsules |
|
Farmak JSC |
| OMEPRAZOLE | capsules |
|
Farmak JSC |
| OMEPRAZOLE | capsules |
|
Farmak JSC |
| OMEPRAZOLE | capsules |
|
ASTRAFARM LLC |
| OMEPRAZOLE 20 ANANTA | capsules |
|
Flamingo Pharmaceuticals Ltd. |
| OMEPRAZOLE KRKA | capsules |
|
KRKA, d.d., Novo mesto |
| OMEPRAZOLE-DARNITSA | capsules |
|
PJSC «Pharmaceutical Company «Darnitsa» |
| OMEZ | capsules |
|
Dr. Reddy's Laboratories Ltd, FTO – II |
| OMEZ | capsules |
|
Dr. Reddy's Laboratories Ltd, FTO – 3 |
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026