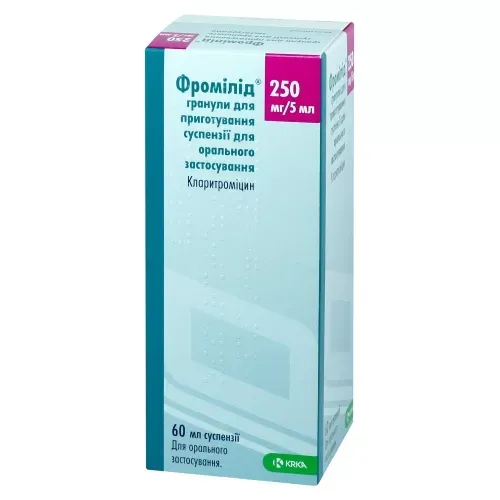
FROMILID
UkraineThe drug is used to treat infections caused by susceptible bacteria, specifically lower and upper respiratory tract infections (bronchitis, pneumonia, tonsillitis, pharyngitis), otitis, skin infections, as well as mycobacterial infections.
Frequently asked questions
How should children take Fromilid correctly?
The dosage depends on the child's body weight and the type of infection. For non-mycobacterial infections, the usual dose is 7.5 mg/kg of body weight twice daily. The suspension can be taken regardless of food (can be taken with milk). Before each use, the bottle should be shaken, and after administration, the syringe should be rinsed with water.
What are the possible side effects of Fromilid?
The most common side effects are abdominal pain, diarrhea, nausea, vomiting, and taste changes. Headache, skin rash, dizziness, and hearing impairment are also possible. In rare cases, serious reactions may occur, such as liver dysfunction or cardiac arrhythmia.
Who should not take this drug?
The drug is contraindicated in individuals with hypersensitivity to clarithromycin or other macrolide antibiotics. It should also not be used in cases of certain cardiac arrhythmias, electrolyte imbalances, severe hepatic or renal impairment, or by women who are breastfeeding.
Can the drug be combined with other medicines?
Special caution is required. Co-administration with certain drugs is prohibited (e.g., astemizole, cisapride, pimozide, terfenadine, oral midazolam, and certain statins such as lovastatin or simvastatin). Caution should also be exercised when taking it with anticoagulants (e.g., warfarin), antiarrhythmics, and certain drugs used to treat HIV.
How should the prepared suspension be stored?
The prepared suspension should be used within 14 days, stored in the bottle in a place protected from light at a temperature not exceeding 25 °C.
Instructions for use
INSTRUCTIONS FOR MEDICAL USE OF THE MEDICINAL PRODUCT Fromilid® (Fromilid®)
Composition:
Active substance: clarithromycin;
5 ml of suspension (1 syringe) contains 250 mg of clarithromycin;
Excipients: carbomer, povidone, hypromellose phthalate (HP 55), talc, purified castor oil, xanthan gum, orange flavor, citric acid, sodium saccharin, monoammonium glycyrrhizinate, neohesperidin dihydrochalcone, colloidal anhydrous silicon dioxide, titanium dioxide (E 171), sucrose, potassium sorbate.
Pharmaceutical form. Granules for the preparation of oral suspension.
Main physicochemical properties: small, heterogeneous granules ranging from white to almost white in color, with an orange flavor.
Pharmacotherapeutic group. Antimicrobial agents for systemic use. Macrolides, lincosamides and streptogramins. Clarithromycin.
ATC code J01FA09.
Pharmacological properties.
Pharmacodynamics.
Clarithromycin is a semi-synthetic antibiotic of the macrolide group. The antibacterial action of clarithromycin is determined by its binding to the 5OS ribosomal subunit of susceptible bacteria and inhibition of protein biosynthesis. The drug demonstrates high in vitro efficacy against a broad spectrum of aerobic and anaerobic gram-positive and gram-negative microorganisms, including hospital strains. Minimum inhibitory concentrations (MICs) of clarithromycin are usually two times lower than those of erythromycin.
Clarithromycin is highly effective against Legionella pneumophila and Mycoplasma pneumoniae. It exerts bactericidal activity against Helicobacter pylori; the activity of clarithromycin is higher at neutral pH than at acidic pH. Clarithromycin is effective against clinically significant strains of mycobacteria. In vitro studies have shown that strains of Enterobacteriaceae and Pseudomonas, as well as non-lactose-producing gram-negative bacteria, are insensitive to clarithromycin.
Clarithromycin is active in vitro and in clinical practice against most strains of the following microorganisms:
Aerobic gram-positive microorganisms: Staphylococcus aureus, Streptococcus pneumoniae, Streptococcus pyogenes, Listeria monocytogenes.
Aerobic gram-negative microorganisms: Haemophilus influenzae, Haemophilus parainfluenzae, Moraxella catarrhalis, Neisseria gonorrhoeae, Legionella pneumophila.
Other microorganisms: Mycoplasma pneumoniae, Chlamydia pneumoniae (TWAR).
Mycobacteria: Mycobacterium leprae, Mycobacterium kansasii, Mycobacterium chelonae, Mycobacterium fortuitum, Mycobacterium avium complex (MAC), which includes Mycobacterium avium, Mycobacterium intracellulare.
Beta-lactamases produced by microorganisms do not affect the efficacy of clarithromycin.
Most methicillin (oxacillin)-resistant strains of staphylococci are insensitive to clarithromycin.
Helicobacter: Helicobacter pylori.
Clarithromycin is active in vitro against most strains of the following microorganisms; however, clinical efficacy and safety of its use have not been established:
Aerobic gram-positive microorganisms: Streptococcus agalactiae, Streptococci (groups C, F, G), Viridans group streptococci.
Aerobic gram-negative microorganisms: Bordetella pertussis, Pasteurella multocida.
Other microorganisms: Chlamydia trachomatis.
Anaerobic gram-positive microorganisms: Clostridium perfringens, Peptococcus niger, Propionibacterium acnes.
Anaerobic gram-negative microorganisms: Bacteroides melaninogenicus.
Spirochetes: Borrelia burgdorferi, Treponema pallidum.
Camphylobacters: Campylobacter jejuni.
Clarithromycin exerts bactericidal action against several bacterial strains: Haemophilus influenzae, Streptococcus pneumoniae, Streptococcus pyogenes, Streptococcus agalactiae, Moraxella (Branhamella) catarrhalis, Neisseria gonorrhoeae, Helicobacter pylori, and Campylobacter spp.
For most microorganisms, the microbiological activity of the metabolite is equal to or 1–2 times weaker than that of the parent compound, except for H. influenzae, against which the metabolite is twice as effective. The parent compound and its main metabolite exhibit either additive or synergistic effects against Haemophilus influenzae, depending on the microbial strain.
Pharmacokinetics.
Clarithromycin is rapidly and well absorbed from the gastrointestinal tract. The microbiologically active metabolite 14-OH-clarithromycin is formed during the first pass through the liver. Food does not significantly affect the bioavailability of the drug. Although the pharmacokinetics of clarithromycin is nonlinear, steady-state concentrations are achieved within two consecutive days of drug administration.
Concentrations of clarithromycin in body tissues are several times higher than in blood plasma. Elevated concentrations of clarithromycin are observed in tonsillar and lung tissues. Concentrations in middle ear fluid exceed those in plasma. At therapeutic doses, clarithromycin is approximately 80% bound to plasma proteins. 14-OH-clarithromycin is the main metabolite excreted by the kidneys, accounting for approximately 10–15% of the administered dose. The majority of the remaining dose is excreted primarily via bile. 5–10% of the parent compound is excreted in feces.
Steady-state concentrations of clarithromycin in patients with hepatic impairment do not differ from those in healthy volunteers, except for lower concentrations of 14-OH-clarithromycin in cases of hepatic dysfunction.
In patients with renal impairment receiving 500 mg of clarithromycin, pharmacokinetic parameters increased proportionally to the degree of renal insufficiency.
Patient age does not affect the pharmacokinetic parameters of clarithromycin.
In HIV-infected children receiving clarithromycin at doses of 15–30 mg/kg/day (divided into two doses), higher plasma concentrations of clarithromycin and a longer elimination half-life were observed.
Clinical characteristics.
Indications.
Infections caused by microorganisms sensitive to clarithromycin:
- Lower respiratory tract infections (bronchitis, acute lobar pneumonia, primary atypical pneumonia);
- Upper respiratory tract infections (tonsillitis, pharyngitis) and infections of the paranasal sinuses;
- Acute otitis media;
- Skin and soft tissue infections (folliculitis, impetigo, erysipelas, furunculosis, infected wounds);
- Disseminated or localized mycobacterial infections caused by Mycobacterium avium or Mycobacterium intracellulare. Localized infections caused by Mycobacterium chelonae, Mycobacterium fortuitum, Mycobacterium kansasii.
Contraindications.
- Hypersensitivity to clarithromycin or to other macrolide antibiotics or to any of the excipients of the medicinal product.
- Concomitant use with the following drugs: astemizole, cisapride, domperidone, pimozide, terfenadine — as this may lead to QT interval prolongation and development of cardiac arrhythmias, including ventricular tachycardia, ventricular fibrillation, and torsades de pointes (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Concomitant use of ergot alkaloids, e.g., ergotamine, dihydroergotamine — as this may lead to ergot toxicity.
- Concomitant use of HMG-CoA reductase inhibitors (statins) that are predominantly metabolized by CYP3A4 (lovastatin or simvastatin) — due to increased risk of myopathy, including rhabdomyolysis (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Concomitant use of clarithromycin and oral midazolam (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Concomitant use of clarithromycin with lomitapide (see section "Interaction with other medicinal products and other forms of interaction").
- Congenital or documented acquired QT interval prolongation or history of ventricular cardiac arrhythmias, including torsades de pointes (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Electrolyte disturbances (hypokalemia or hypomagnesemia) — due to risk of QT interval prolongation.
- Severe hepatic insufficiency and concomitant renal insufficiency (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Concomitant use of clarithromycin (and other potent CYP3A4 inhibitors) with colchicine in patients with renal or hepatic impairment (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
- Concomitant use of clarithromycin with ticagrelor, ivabradine, or ranolazine.
Interaction with other medicinal products and other forms of interaction.
Concomitant use of the following medicinal products is strictly contraindicated due to the potential for severe interaction consequences
Astemizole, cisapride, domperidone, pimozide, and terfenadine
Increased serum levels of cisapride have been observed when used concomitantly with clarithromycin, which may cause QT interval prolongation and arrhythmias, including ventricular tachycardia, ventricular fibrillation, and torsades de pointes. Similar effects have been reported with concomitant use of pimozide and clarithromycin (see section "Contraindications").
Macrolides have been reported to alter the metabolism of terfenadine, leading to increased serum levels of terfenadine, which has sometimes been associated with cardiac arrhythmias such as QT interval prolongation, ventricular tachycardia, ventricular fibrillation, and torsades de pointes (see section "Contraindications"). In a study involving 14 volunteers, concomitant use of terfenadine and clarithromycin resulted in a 2–3-fold increase in serum levels of the acid metabolite of terfenadine and QT interval prolongation, without any clinically apparent effect. Similar effects have been observed with concomitant use of astemizole and other macrolides.
Ergotamine/dihydroergotamine
Post-marketing reports indicate that concomitant use of clarithromycin and ergotamine or dihydroergotamine has been associated with signs of acute ergotism, characterized by vasospasm and ischemia of extremities and other tissues, including the central nervous system. Concomitant use of clarithromycin and ergot alkaloids is contraindicated (see section "Contraindications").
Oral midazolam
When midazolam was administered with clarithromycin tablets (500 mg twice daily), the AUC of midazolam increased 7-fold after oral administration of midazolam. Concomitant use of oral midazolam and clarithromycin is contraindicated (see section "Contraindications").
HMG-CoA reductase inhibitors (statins)
Concomitant use of clarithromycin with lovastatin or simvastatin is contraindicated (see section "Contraindications"), as these statins are predominantly metabolized by CYP3A4; concomitant use with clarithromycin increases their plasma concentration, thereby increasing the risk of myopathy, including rhabdomyolysis. Cases of rhabdomyolysis have been reported in patients receiving clarithromycin concomitantly with these statins. If clarithromycin therapy cannot be avoided, treatment with lovastatin or simvastatin should be discontinued during the course of clarithromycin therapy.
Clarithromycin should be used with caution when administered concomitantly with statins. If concomitant use of clarithromycin with statins cannot be avoided, it is recommended to use the lowest effective dose of the statin. It may be possible to use a statin not dependent on CYP3A metabolism (e.g., fluvastatin). Patients should be monitored for signs and symptoms of myopathy.
Lomitapide
Concomitant use of clarithromycin with lomitapide is contraindicated due to the potential for significant increases in transaminase levels (see section "Contraindications").
Effect of other medicinal products on the pharmacokinetics of clarithromycin
Medicinal products that are CYP3A inducers (e.g., rifampicin, phenytoin, carbamazepine, phenobarbital, St. John's wort preparations) may induce the metabolism of clarithromycin. This may lead to subtherapeutic levels of clarithromycin and reduced efficacy. Additionally, monitoring of plasma levels of the CYP3A inducer may be necessary, as they may be increased due to CYP3A inhibition by clarithromycin (see also the prescribing information for the respective CYP3A4 inducer). Concomitant use of rifabutin and clarithromycin has led to increased rifabutin levels and decreased clarithromycin serum levels, with an increased risk of uveitis.
It is known or suspected that the following medicinal products may affect clarithromycin blood concentrations; therefore, dose adjustment or alternative therapy may be required.
Efavirenz, nevirapine, rifampicin, rifabutin, and rifapentine
Potent inducers of cytochrome P450 enzymes, such as efavirenz, nevirapine, rifampicin, rifabutin, and rifapentine, may accelerate the metabolism of clarithromycin, reducing its plasma concentration but increasing the concentration of 14-OH-clarithromycin — a microbiologically active metabolite. Since the microbiological activity of clarithromycin and 14-OH-clarithromycin varies against different bacteria, the expected therapeutic effect may not be achieved with concomitant use of clarithromycin and cytochrome P450 enzyme inducers.
Etravirine
The effect of clarithromycin was reduced by etravirine, although concentrations of the active metabolite 14-OH-clarithromycin were increased. Since 14-OH-clarithromycin has reduced activity against MAC, the overall activity against this pathogen may be altered. Therefore, for treatment of MAC, consideration should be given to using alternative agents to clarithromycin.
Fluconazole
Steady-state concentrations of the active metabolite 14-OH-clarithromycin were not significantly altered when used concomitantly with fluconazole. Dose adjustment of clarithromycin is not required.
Ritonavir
Administration of 200 mg ritonavir every 8 hours and 500 mg clarithromycin every 12 hours resulted in significant inhibition of clarithromycin metabolism. Cmax of clarithromycin increased by 31%, Cmin by 182%, and AUC by 77%. Complete inhibition of 14-OH-clarithromycin formation was observed. Due to the wide therapeutic window, dose reduction of clarithromycin is not required for patients with normal renal function. However, dose adjustment is necessary for patients with renal impairment: for patients with CLCR 30–60 mL/min, the clarithromycin dose should be reduced by 50%. For patients with severe renal impairment (CLCR < 30 mL/min), the clarithromycin dose should be reduced by 75%. Clarithromycin doses exceeding 1 g per day should not be used concomitantly with ritonavir.
The same dose adjustment should be applied to patients with renal impairment when ritonavir is used as a pharmacokinetic booster with other HIV protease inhibitors, including atazanavir and saquinavir (see below "Bidirectional drug interactions").
Effect of clarithromycin on other medicinal products
CYP3A-related interactions
Concomitant use of clarithromycin, a known CYP3A enzyme inhibitor, with a drug primarily metabolized by CYP3A, may result in increased plasma concentration of the latter, thereby potentially enhancing or prolonging its therapeutic effect and increasing the risk of adverse reactions.
Use of clarithromycin is contraindicated in patients receiving CYP3A substrates astemizole, cisapride, domperidone, pimozide, and terfenadine, due to the risk of QT interval prolongation and cardiac arrhythmias, including ventricular tachycardia, ventricular fibrillation, and torsades de pointes (see sections "Contraindications" and "Special precautions for use").
Also contraindicated is the use of clarithromycin with ergot alkaloids, oral midazolam, HMG-CoA reductase inhibitors predominantly metabolized by CYP3A4 (e.g., lovastatin and simvastatin), colchicine, ticagrelor, ivabradine, and ranolazine (see section "Contraindications").
Caution is required when using clarithromycin concomitantly with other drugs that are CYP3A substrates, especially if the CYP3A substrate has a narrow safety margin (e.g., carbamazepine) and/or is extensively metabolized by this enzyme. In such cases, dose adjustment may be necessary, and, if possible, serum concentrations of drugs predominantly metabolized by CYP3A should be closely monitored. Medicinal products or classes of medicinal products known or suspected to be metabolized by the same CYP3A isoenzyme include (list not exhaustive): alprazolam, carbamazepine, cilostazol, cyclosporine, disopyramide, ibrutinib, methylprednisolone, midazolam, omeprazole, oral anticoagulants (e.g., warfarin, rivaroxaban, apixaban), atypical antipsychotics (e.g., quetiapine), quinidine, rifabutin, sildenafil, sirolimus, tacrolimus, triazolam, and vinblastine.
A similar interaction mechanism has been observed with phenytoin, theophylline, and valproate, which are metabolized by other isoenzymes of the cytochrome P450 system.
Direct oral anticoagulants (DOACs)
DOACs dabigatran and edoxaban are substrates of the efflux transporter P-gp (P-glycoprotein). Rivaroxaban and apixaban are metabolized via CYP3A4 and are also P-gp substrates. Caution should be exercised when using clarithromycin concomitantly with these agents, especially in patients at high risk of bleeding (see "Special precautions for use").
Antiarrhythmic agents
Post-marketing reports describe cases of torsades de pointes occurring with concomitant use of clarithromycin with quinidine or disopyramide. ECG monitoring is recommended for early detection of QT interval prolongation. During clarithromycin therapy, serum concentrations of these drugs should be monitored.
Post-marketing use has also reported hypoglycemia with concomitant use of these agents.
Hydroxychloroquine and chloroquine
Clarithromycin should be used with caution in patients receiving hydroxychloroquine or chloroquine, which are known to prolong the QT interval, due to the potential for inducing cardiac arrhythmias and serious cardiovascular events.
Oral hypoglycemic agents/insulin
When used concomitantly with certain hypoglycemic agents, such as nateglinide and repaglinide, clarithromycin may inhibit the CYP3A enzyme, potentially causing hypoglycemia. Close monitoring of glucose levels is recommended.
Omeprazole
Use of clarithromycin in combination with omeprazole in healthy adult volunteers resulted in increased steady-state concentrations of omeprazole. When omeprazole was used alone, the mean gastric pH measured over 24 hours was 5.2; with concomitant use of omeprazole and clarithromycin, it was 5.7.
Sildenafil, tadalafil, and vardenafil
There is a potential for increased plasma concentrations of phosphodiesterase inhibitors, which are at least partially metabolized by CYP3A (sildenafil, tadalafil, and vardenafil); therefore, when used concomitantly with clarithromycin, consideration should be given to reducing the dose of phosphodiesterase inhibitors.
Theophylline, carbamazepine
Clinical studies have shown a slight but statistically significant (p<0.05) increase in plasma concentrations of theophylline or carbamazepine when used concomitantly with clarithromycin. Dose reduction may be necessary.
Tolterodine
Tolterodine is primarily metabolized by the cytochrome P450 2D6 isoenzyme (CYP2D6). However, in patients lacking CYP2D6, metabolism occurs via CYP3A. In this population, inhibition of CYP3A leads to a significant increase in tolterodine plasma concentrations. Dose reduction of tolterodine may be necessary in such patients when used concomitantly with CYP3A inhibitors such as clarithromycin.
Triazolobenzodiazepines (e.g., alprazolam, midazolam, triazolam)
When midazolam was administered with clarithromycin tablets (500 mg twice daily), the AUC of midazolam increased 2.7-fold after intravenous administration and 7-fold after oral administration. Combined use of oral midazolam and clarithromycin should be avoided. With intravenous midazolam and clarithromycin, careful monitoring of the patient is required for timely dose adjustment.
The same precautions should be observed when using other benzodiazepines metabolized by CYP3A, including triazolam and alprazolam. For benzodiazepines whose elimination does not depend on CYP3A (temazepam, nitrazepam, lorazepam), clinically significant interaction with clarithromycin is unlikely.
Post-marketing reports describe drug interactions and adverse effects on the central nervous system (e.g., somnolence and confusion) with concomitant use of clarithromycin and triazolam. Patients should be monitored, considering the potential for increased pharmacological effects on the CNS.
Corticosteroids
Caution is advised when using clarithromycin concomitantly with systemic and inhaled corticosteroids that are primarily metabolized by CYP3A, due to the potential for increased systemic exposure to corticosteroids. Patients should be closely monitored for adverse effects of systemic corticosteroids when used concomitantly.
Other types of interactions
Colchicine
Colchicine is a substrate of CYP3A and P-glycoprotein (Pgp). Clarithromycin and other macrolides are known to inhibit CYP3A and Pgp. Concomitant use of clarithromycin and colchicine may result in increased colchicine exposure due to inhibition of Pgp and CYP3A by clarithromycin. Concomitant use of clarithromycin with colchicine in patients with renal or hepatic impairment is contraindicated (see sections "Contraindications", "Special precautions for use"). Patients should be monitored for clinical signs of colchicine toxicity.
Digoxin
Digoxin is considered a Pgp substrate. Clarithromycin is known to inhibit Pgp. Concomitant use may lead to increased digoxin exposure due to Pgp inhibition. Post-marketing reports have described increased serum digoxin concentrations in patients receiving clarithromycin concomitantly with digoxin. In some patients, signs of digoxin toxicity developed, including potentially fatal arrhythmias. Serum digoxin concentrations should be closely monitored when used concomitantly with clarithromycin.
Zidovudine
Concomitant use of immediate-release clarithromycin tablets and zidovudine in HIV-infected patients may lead to decreased steady-state serum concentrations of zidovudine. Clarithromycin may interfere with the absorption of oral zidovudine when taken simultaneously, but this can largely be avoided by maintaining a 4-hour interval between administration of clarithromycin and zidovudine. Such interaction has not been reported with clarithromycin suspension and zidovudine or didanosine in children. This interaction is unlikely with intravenous infusion of clarithromycin.
Phenytoin, valproate
Spontaneous or published reports describe interactions between CYP3A inhibitors, including clarithromycin, and drugs not metabolized by CYP3A (e.g., phenytoin and valproate). Monitoring of serum levels of such drugs is recommended when used concomitantly with clarithromycin. Increased serum levels have been reported.
Bidirectional drug effects
Atazanavir
Concomitant use of clarithromycin (500 mg twice daily) and atazanavir (400 mg once daily), both substrates and inhibitors of CYP3A, resulted in a doubling of clarithromycin exposure and a 70% reduction in 14-OH-clarithromycin exposure, with a 28% increase in atazanavir AUC. Since clarithromycin has a wide therapeutic range, dose reduction is not necessary for patients with normal renal function. The clarithromycin dose should be reduced by 50% for patients with creatinine clearance of 30–60 mL/min and by 75% for patients with creatinine clearance <30 mL/min. Clarithromycin doses exceeding 1000 mg per day should not be used concomitantly with protease inhibitors.
Calcium channel blockers
Due to the risk of arterial hypotension, clarithromycin should be used with caution concomitantly with calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem). Plasma concentrations of both clarithromycin and calcium channel blockers may increase with interaction. In patients receiving clarithromycin with verapamil, arterial hypotension, bradyarrhythmia, and lactic acidosis have been observed.
Itraconazole
Clarithromycin and itraconazole are both substrates and inhibitors of CYP3A, thus clarithromycin may increase plasma levels of itraconazole and vice versa. When itraconazole is used concomitantly with clarithromycin, patients should be closely monitored for signs or symptoms of enhanced or prolonged pharmacological effect.
Saquinavir
Concomitant use of clarithromycin (500 mg twice daily) with saquinavir (soft gelatin capsules, 1200 mg three times daily), both substrates and inhibitors of CYP3A, resulted in a 177% increase in AUC and 187% increase in Cmax at steady state compared to saquinavir alone. Meanwhile, AUC and Cmax of clarithromycin increased by approximately 40% compared to clarithromycin alone. Dose adjustment is not necessary if both medicinal products are used concomitantly for a limited period and at the above-mentioned doses/forms. Results from drug interaction studies using soft gelatin capsules may not reflect effects observed with hard gelatin capsules of saquinavir. Results from drug interaction studies with saquinavir alone may not reflect effects observed with saquinavir/ritonavir therapy. When saquinavir is used with ritonavir, possible effects of ritonavir on clarithromycin should be considered (see section above).
Special precautions for use.
Clarithromycin should not be prescribed to pregnant women without careful assessment of the benefit/risk ratio, especially during the first trimester of pregnancy (see section "Use during pregnancy or lactation").
Caution is recommended in patients with severe renal impairment (see section "Dosage and administration").
Prolonged or repeated use of antibiotics may lead to overgrowth of resistant bacteria and fungi. If superinfection occurs, clarithromycin should be discontinued and appropriate therapy initiated.
Clarithromycin is primarily eliminated via the liver. Therefore, caution should be exercised when administering the drug to patients with moderate to severe hepatic impairment (see section "Dosage and administration").
Hepatic function abnormalities, including elevated liver enzymes, as well as hepatocellular and/or cholestatic hepatitis, with or without jaundice, have been reported during clarithromycin therapy. Liver function abnormalities may be severe but are usually reversible. Fatal cases of hepatic failure have been reported (see section "Adverse reactions"), primarily in patients with serious underlying diseases and/or concomitant medications. Clarithromycin therapy should be discontinued immediately if signs or symptoms of hepatitis occur, such as anorexia, jaundice, dark urine, pruritus, or abdominal pain.
Diarrhea, ranging from mild to severe pseudomembranous colitis caused by Clostridium difficile (CDAD), has been reported with nearly all antibacterial agents, including clarithromycin. Antibacterial therapy alters the normal flora of the colon, potentially leading to overgrowth of Clostridium difficile. Clostridium difficile-associated diarrhea should always be considered in any patient presenting with diarrhea following antibiotic use. A careful medical history is essential, as cases have been reported up to two months after antibiotic administration. If pseudomembranous colitis develops, clarithromycin therapy should be discontinued regardless of the indication for which it was prescribed. Microbiological testing should be performed and appropriate treatment initiated. Antiperistaltic agents should be avoided.
Colchicine
Cases of colchicine toxicity (including fatal outcomes) have been reported with concomitant use of clarithromycin and colchicine, particularly in elderly patients and those with renal impairment. Concomitant use of clarithromycin with colchicine in patients with renal or hepatic impairment is contraindicated (see section "Contraindications").
Caution should be exercised when clarithromycin is used concomitantly with triazolobenzodiazepines, such as triazolam, or intravenous midazolam (see section "Interaction with other medicinal products and other forms of interaction").
Clarithromycin should be used cautiously with other ototoxic agents, particularly aminoglycosides. Monitoring of vestibular and auditory function during treatment is recommended.
Cardiovascular complications
QT interval prolongation, reflecting effects on cardiac repolarization and increasing the risk of cardiac arrhythmias including torsades de pointes, has been observed in patients treated with macrolides, including clarithromycin (see section "Adverse reactions"). Due to the increased risk of QT prolongation and ventricular arrhythmias (including torsades de pointes), clarithromycin is contraindicated in patients taking astemizole, cisapride, domperidone, pimozide, or terfenadine; in patients with hypokalemia; and in patients with a history of QT prolongation or ventricular arrhythmias (see section "Contraindications").
In addition, clarithromycin should be used with caution in the following patient groups:
- Patients with ischemic heart disease, severe heart failure, conduction disorders, or clinically significant bradycardia.
- Patients who are concurrently taking other drugs that may prolong the QT interval, except those that are contraindicated.
Epidemiological studies on the cardiovascular risks associated with macrolide use have yielded mixed results. Some observational studies have identified a rare, short-term risk of arrhythmias, myocardial infarction, and fatal cardiovascular events associated with macrolide use, including clarithromycin. These findings should be balanced against the therapeutic benefits when prescribing clarithromycin.
Pneumonia
Due to potential resistance of Streptococcus pneumoniae to macrolides, susceptibility testing is important when prescribing clarithromycin for community-acquired pneumonia. For hospital-acquired pneumonia, clarithromycin should be used in combination with other appropriate antibiotics.
Skin and soft tissue infections of mild to moderate severity
These infections are most commonly caused by Staphylococcus aureus and Streptococcus pyogenes, both of which may be macrolide-resistant. Therefore, susceptibility testing is essential. When beta-lactam antibiotics cannot be used (e.g., due to allergy), alternative agents such as clindamycin may be considered as first-line therapy. Currently, macrolides play a limited role in treating certain skin and soft tissue infections, such as those caused by Corynebacterium minutissimum (erythrasma), acne vulgaris, and folliculitis, or in situations where penicillins cannot be used.
In the event of severe hypersensitivity reactions, such as anaphylaxis or serious skin reactions (e.g., acute generalized exanthematous pustulosis, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms (DRESS syndrome)), or Henoch-Schönlein purpura, clarithromycin therapy should be immediately discontinued and appropriate treatment initiated.
HMG-CoA reductase inhibitors (statins)
Concomitant use of clarithromycin with lovastatin or simvastatin is contraindicated (see section "Contraindications"). Clarithromycin should be used cautiously with other statins. Cases of rhabdomyolysis have been reported with concomitant use of clarithromycin and statins. Patients should be monitored for signs and symptoms of myopathy. If concomitant use cannot be avoided, the lowest registered dose of the statin should be prescribed. Consider using a statin not metabolized by CYP3A (e.g., fluvastatin) (see section "Interaction with other medicinal products and other forms of interaction").
Oral hypoglycemic agents/insulin
Combination therapy with clarithromycin and oral hypoglycemic agents (such as sulfonylureas) and/or insulin may result in marked hypoglycemia. Close monitoring of blood glucose levels is recommended (see section "Interaction with other medicinal products and other forms of interaction").
Oral anticoagulants
Concomitant use of clarithromycin with warfarin increases the risk of serious bleeding, significantly elevated INR (International Normalized Ratio), and prolonged prothrombin time. The INR and prothrombin time should be monitored closely while patients are receiving both clarithromycin and oral anticoagulants.
Caution is advised when clarithromycin is used concomitantly with direct oral anticoagulants such as dabigatran, rivaroxaban, apixaban, and edoxaban, particularly in patients at high risk of bleeding (see section "Interaction with other medicinal products and other forms of interaction").
Use of any antimicrobial therapy, including clarithromycin, for Helicobacter pylori infection may lead to the development of microbial resistance.
Cross-resistance between clarithromycin and other macrolides, as well as with lincomycin and clindamycin, should be considered.
Patients with known hypersensitivity to lincomycin or clindamycin should be given clarithromycin with caution due to possible cross-sensitivity.
Clarithromycin should be used cautiously with inducers of the CYP3A4 enzyme (see section "Interaction with other medicinal products and other forms of interaction").
Exacerbation of symptoms of myasthenia gravis has been reported in patients receiving clarithromycin.
Sucrose
The product contains sucrose. Therefore, patients with rare hereditary fructose intolerance, glucose-galactose malabsorption syndrome, or sucrase-isomaltase deficiency should not take this medicine. The sucrose content should also be considered when prescribing this product to diabetic patients.
Use during pregnancy or lactation.
Pregnancy
The safety of clarithromycin use during pregnancy or lactation has not been established. Based on animal studies and human experience, a potential adverse effect on embryonic development cannot be excluded. Some observational studies assessing the impact of clarithromycin during the first and second trimesters have shown an increased risk of miscarriage compared to no antibiotic use or use of other antibiotics during the same period. Epidemiological data on the risk of major congenital malformations associated with macrolide use, including clarithromycin, during pregnancy are conflicting.
Clarithromycin should only be prescribed if the expected benefit to the mother outweighs the potential risk to the fetus, particularly during the first three months of pregnancy.
Lactation
Clarithromycin is excreted in small amounts in human breast milk. An exclusively breastfed infant is expected to receive approximately 1.7% of the maternal dose of clarithromycin (adjusted for body weight).
Therefore, clarithromycin is contraindicated in women who are breastfeeding.
Fertility
Fertility studies in rats revealed no evidence of harmful effects.
Ability to influence the speed of reactions while driving or operating machinery.
Data on this effect are lacking. However, potential adverse reactions affecting the nervous system, such as convulsions, dizziness, vertigo, hallucinations, confusion, and disorientation, which may impair psychomotor performance, should be considered.
Dosage and Administration.
For the treatment of non-mycobacterial infections, the recommended dose of Fromilid® for children aged 6 months to 12 years is 7.5 mg/kg body weight twice daily. The maximum dose is 500 mg (10 ml) twice daily (every 12 hours). The duration of treatment is usually 5–10 days, depending on the type of pathogen and severity of the disease. The suspension should be administered independently of food intake (it may be taken with milk).
Table 1.
Dosage according to the child's body weight
| Child's body weight* (kg) |
250 mg/5 ml (syringe) |
Dose, mg |
| 8–11 |
1.25 ml twice daily (¼) |
62.5 mg |
| 12–19 |
2.5 ml twice daily (½) |
125 mg |
| 20–29 |
3.75 ml twice daily (¾) |
187.5 mg |
| 30–40 |
5 ml twice daily (1) |
250 mg |
*For children with body weight up to 8 kg, the dose should be calculated per kilogram of body weight (7.5 mg/kg twice daily).
Dosing in renal impairment
In children with creatinine clearance less than 0.5 mL/sec (30 mL/min) or serum creatinine levels exceeding 290 µmol/L (3.3 mg/100 mL), the dose should be reduced by 50% or the dosing interval should be doubled. Treatment should not exceed 14 days.
Mycobacterial infections
For treatment of mycobacterial infections, the recommended pediatric dose of Fromilid® suspension is 7.5 to 15 mg/kg body weight twice daily, based on individual clinical assessment by the physician regarding the patient's condition and severity of the disease.
Treatment should continue as long as clinical efficacy is observed (additional anti-mycobacterial agents may be required).
Table 2.
Recommended dosing for children with mycobacterial infection according to body weight
| Child's body weight* (kg) |
Amount of Fromilid® 250 mg/5 ml suspension (per day) |
|
| 7.5 mg/kg twice daily |
15 mg/kg twice daily |
|
| 8–11 |
1.25 ml |
2.5 ml |
| 12–19 |
2.5 ml |
5 ml |
| 20–29 |
3.75 ml |
7.5 ml |
| 30–40 |
5 ml |
10 ml |
*For children with body weight up to 8 kg, the dose should be calculated per kilogram of body weight (7.5–15 mg/kg twice daily).
Preparation of suspension. The oral suspension contains small granules that should not be chewed, as their contents have a bitter taste. An oral syringe is provided for measuring the dose. One full syringe contains 5 mL of suspension (250 mg of clarithromycin). After each use, the syringe should be rinsed with water.
To prepare 60 mL of suspension (250 mg/5 mL), 42 mL of purified or boiled cooled water is required. Shake the bottle to separate the granules. Add approximately half of the required amount of water and shake thoroughly until all solid particles are converted into a suspension. Then add the remaining water up to the mark on the bottle and shake well. Avoid vigorous and/or prolonged shaking. The bottle should be shaken before each use to re-suspend the suspension.
Children.
For use in children aged 6 months to 12 years.
Overdose.
Symptoms. Available reports indicate that clarithromycin overdose may cause gastrointestinal disturbances. In one patient with a history of bipolar disorder who ingested 8 g of clarithromycin, altered mental status, paranoid behavior, hypokalemia, and hypoxemia developed.
Treatment. There is no specific antidote for clarithromycin overdose. As with other macrolides, hemodialysis or peritoneal dialysis is unlikely to significantly affect serum clarithromycin levels. Adverse reactions associated with overdose should be managed by immediate gastric lavage and administration of symptomatic therapy.
Adverse Reactions
The most common and frequently reported adverse reactions associated with clarithromycin therapy in both adults and children were abdominal pain, diarrhea, nausea, vomiting, and altered taste. These adverse reactions were generally mild in intensity and consistent with the known safety profile of macrolide antibiotics. There was no significant difference in the frequency of these gastrointestinal adverse reactions between patient populations with mycobacterial infections and those without such infections during clinical studies.
The table below lists adverse reactions observed during clinical trials and post-marketing use of clarithromycin immediate-release, oral suspension granules, and extended-release tablets.
Reactions considered at least possibly related to clarithromycin are listed by system organ classes and frequency: common (≥ 1/100 — < 1/10), uncommon (≥ 1/1000 — < 1/100), and frequency not known (reactions reported during post-marketing experience; frequency cannot be estimated from available data).
| System Organ Class |
Adverse Reactions |
||
| Common |
Uncommon |
Unknown |
|
| Infections and infestations |
Cellulitis1, oral candidiasis, gastroenteritis2, infection3, vaginal infection |
Pseudomembranous colitis, shigellosis, erythrasma |
|
| Blood and lymphatic system disorders |
Leukopenia, neutropenia4, thrombocytosis3, eosinophilia4 |
Agranulocytosis, thrombocytopenia |
|
| Immune system disorders |
Anaphylactoid reactions1, hypersensitivity |
Anaphylactic reactions, angioedema |
|
| Metabolism and nutrition disorders |
Anorexia, decreased appetite |
||
| Psychiatric disorders |
Insomnia |
Anxiety, nervousness3 |
Psychosis, confusion, depersonalization, depression, disorientation, hallucinations, nightmares, mania |
| Nervous system disorders |
Dysgeusia (disturbance of taste), headache |
Loss of consciousness1, dyskinesia1, dizziness, somnolence, tremor |
Seizures, ageusia (loss of taste), parosmia, anosmia, paresthesia |
| Ear and labyrinth disorders |
Dizziness, hearing impairment, tinnitus |
Deafness |
|
| Cardiac disorders |
Cardiac arrest1, atrial fibrillation1, QT interval prolongation, extrasystoles1, palpitations |
Torsades de pointes, ventricular tachycardia |
|
| Vascular disorders |
Vasodilation1 |
Ecchymosis |
|
| Respiratory, thoracic and mediastinal disorders |
Nosebleed2, asthma1, pulmonary embolism1 |
||
| Gastrointestinal disorders |
Diarrhea, vomiting, dyspepsia, nausea, abdominal pain |
Esophagitis1, gastroesophageal reflux disease2, gastritis, proctalgia2, stomatitis, glossitis, abdominal distension4, constipation, dry mouth, belching, flatulence |
Acute pancreatitis, tongue discoloration, tooth discoloration |
| Hepatobiliary disorders |
Abnormal liver function tests |
Cholestasis4, hepatitis4, increased ALT, AST, GGT4 |
Liver failure, cholestatic jaundice, hepatocellular jaundice |
| Skin and subcutaneous tissue disorders |
Rash, hyperhidrosis |
Bullous dermatitis1, pruritus, urticaria, maculopapular rash3 |
Severe skin adverse reactions (e.g., acute generalized exanthematous pustulosis, Stevens-Johnson syndrome4, toxic epidermal necrolysis4, DRESS syndrome, acne, Henoch-Schönlein purpura |
| Musculoskeletal and connective tissue disorders |
Muscle spasms3, skeletal muscle rigidity1, myalgia2 |
Rhabdomyolysis2 (in some reports, rhabdomyolysis occurred when clarithromycin was used concomitantly with other medicinal products known to be associated with rhabdomyolysis (such as statins, fibrates, colchicine or allopurinol)), myopathy |
|
| Renal and urinary disorders |
Increased blood creatinine1, increased blood urea1 |
Renal failure, interstitial nephritis |
|
| General disorders and administration site conditions |
Phlebitis at injection site1, pain, inflammation at injection site1 |
Malaise4, fever3, asthenia, chest pain4, chills4, fatigue4 |
|
| Laboratory investigations |
Increased blood alkaline phosphatase4, increased blood lactate dehydrogenase4, change in albumin/globulin ratio1 |
Increased MCV, prolonged prothrombin time, change in urine color |
|
1,2,3,4 The adverse reactions listed below were reported only when the drug was used in the following forms: 1 – lyophilized powder for infusion solution, 2 – prolonged-release tablets, 3 – suspension, 4 – immediate-release tablets.
The frequency, type, and severity of adverse reactions in children are similar to those observed in adults.
Other patient groups
Patients with impaired immune system.
In patients with AIDS and other patients with impaired immune system who received high doses of clarithromycin for longer than recommended for the treatment of mycobacterial infections, it is not always possible to distinguish adverse reactions related to the drug from symptoms of the underlying or concomitant diseases.
In adult patients who received clarithromycin at daily doses of 1000 mg and 2000 mg, the most commonly reported adverse effects were nausea, vomiting, taste disturbance, abdominal pain, diarrhea, rash, abdominal distension, headache, constipation, and hearing impairment. According to this criterion, significant abnormal elevations in ALT and AST levels and abnormal decreases in white blood cell and platelet counts were observed in 2–3% of these patients. A smaller percentage of patients experienced increased blood urea nitrogen levels.
Reporting suspected adverse reactions
Reporting of adverse reactions after drug registration is important. It allows continuous monitoring of the benefit-risk balance of the medicinal product. Healthcare professionals, pharmacists, patients, or their legal representatives should report all suspected adverse reactions and lack of efficacy to the State Expert Center of the Ministry of Health of Ukraine via the following link: https://aisf.dec.gov.ua.
Shelf life. 2 years.
Storage conditions. Store in the original packaging at a temperature not exceeding 30 °C.
The prepared suspension should be used within 14 days when stored in the original packaging at a temperature not exceeding 25 °C, protected from light.
Keep out of reach and sight of children.
Packaging. Granules for the preparation of 60 ml (250 mg/5 ml) oral suspension in a glass bottle; 1 bottle with an oral syringe in a cardboard box.
Prescription status. Prescription only.
Manufacturer. KRKA, d.d., Novo mesto, Slovenia.
Manufacturer's address and location of business operations.
Smarjeska cesta 6, 8501 Novo mesto, Slovenia.
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026