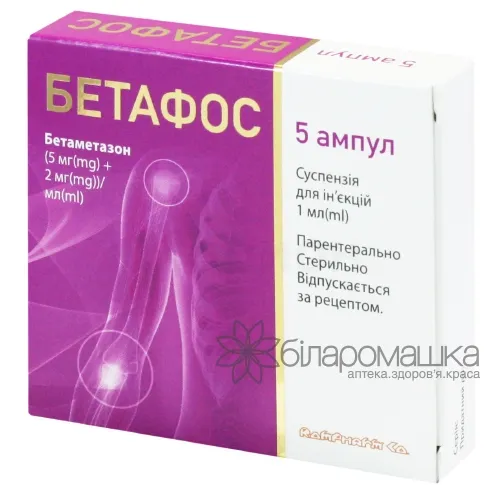
BETAPHOS
UkraineThe drug is used to treat a wide range of diseases: dermatological (eczema, psoriasis, dermatitis), rheumatic (arthritis, osteoarthritis, bursitis, tendinitis), allergic conditions (bronchial asthma, hay fever, edema), as well as certain oncological and other diseases.
Frequently asked questions
How should Betaphos be taken correctly?
The drug is administered intramuscularly (into the buttock) or locally (into joints or the skin). Dosage and frequency of administration are determined individually by a physician depending on the severity of the disease. It is important not to administer the drug intravenously or subcutaneously.
What side effects can Betaphos cause?
Possible side effects include disturbances in water-electrolyte balance (e.g., sodium retention or potassium excretion), increased blood pressure, weight changes, skin atrophy, gastric ulcers, sleep disturbances, mood changes, as well as effects on vision (glaucoma, cataract).
Who should not use this drug?
Contraindications include hypersensitivity to the components of the drug or to corticosteroids, systemic fungal infections, as well as idiopathic thrombocytopenic purpura (for intramuscular administration).
Can the drug be taken with other medicines?
Caution is required when combining with diuretics, anticoagulants, salicylates, cardiac glycosides, and certain other drugs, as this may alter their effect or increase the risk of complications. Additionally, smallpox vaccination should not be performed during therapy.
Is it safe to use the drug in children?
Due to a lack of sufficient data, the use of the drug in children is undesirable, as it may cause growth retardation and adrenal dysfunction.
What are the specific considerations for use during pregnancy and breastfeeding?
Prescribing the drug to pregnant or breastfeeding women is only possible after a thorough assessment by a physician of the risks to both mother and child, as corticosteroids pass through the placenta and into breast milk.
Instructions for use
INSTRUCTIONS FOR MEDICAL USE OF THE MEDICINAL PRODUCT BETAPOS
Composition:
Active substance: betamethasone;
1 ml of suspension contains 6.43 mg of betamethasone dipropionate (equivalent to 5 mg of betamethasone) and 2.63 mg of betamethasone sodium phosphate (equivalent to 2 mg of betamethasone);
Excipients: methylparahydroxybenzoate (E 218), propylparahydroxybenzoate (E 216), benzyl alcohol, polyethylene glycol (macrogol) 4000, sodium carmellose, disodium phosphate dodecahydrate, disodium edetate, sodium chloride, polysorbate 80, 1 M hydrochloric acid solution, water for injections.
Pharmaceutical form. Injection suspension.
Main physicochemical properties: a suspension containing particles from white to almost white, which resuspend easily upon shaking to form a suspension free from foreign particles, white or slightly yellowish in color, without agglomerates.
Pharmaco-therapeutic group
Corticosteroids for systemic use. Glucocorticoids. ATC code H02A B01.
Pharmacological Properties
Pharmacodynamics
Betamethasone is a synthetic glucocorticoid (9 alpha-fluoro-16 beta-methylprednisolone). Betamethasone exerts a potent anti-inflammatory, antiallergic, and immunosuppressive effect.
Betamethasone does not produce clinically significant mineralocorticoid activity.
Glucocorticosteroids are distributed through cell membranes and form complexes with specific cytoplasmic receptors. These complexes then penetrate the cell nucleus, bind to DNA (chromatin), and stimulate transcription of messenger RNA and subsequent synthesis of proteins of various enzymes. These proteins are ultimately responsible for the effects observed during systemic administration of glucocorticoids. In addition to their significant effects on inflammatory and immune processes, glucocorticoids also affect carbohydrate, protein, and lipid metabolism, as well as exert actions on the cardiovascular system, skeletal muscles, and central nervous system.
Effects on inflammatory and immune processes
The therapeutic use of glucocorticoids is based primarily on their anti-inflammatory, immunosuppressive, and antiallergic properties. The main aspects of these properties include reduction in the number of immunocompetent cells at the site of inflammation, decreased vasodilation, stabilization of lysosomal membranes, inhibition of phagocytosis, and reduced production of prostaglandins and related compounds.
The anti-inflammatory effect is approximately 25 times greater than that of hydrocortisone and 8–10 times greater than that of prednisolone (on a weight basis).
Effects on carbohydrate and protein metabolism
Glucocorticoids stimulate protein catabolism. In the liver, the released amino acids are converted into glucose and glycogen through the process of gluconeogenesis. Glucose absorption into peripheral tissues is reduced, leading to hyperglycemia and glucosuria, particularly in patients predisposed to diabetes.
Effects on lipid metabolism
Glucocorticoids exert a lipolytic effect. This lipolysis is more pronounced in the extremities. Additionally, lipolytic activity is manifested particularly in the trunk, neck, and head. This combination of effects results in redistribution of fat deposits.
The maximum pharmacological effect of corticosteroids occurs later than the peak serum concentration, indicating that the efficacy of these drugs is primarily due to modification of enzyme activity rather than direct pharmacological action.
Pharmacokinetics
Betamethasone sodium phosphate and betamethasone dipropionate are absorbed from the site of administration and produce both local and systemic therapeutic and other pharmacological effects.
Betamethasone sodium phosphate is well water-soluble and is metabolized in the body to form betamethasone—the biologically active steroid. 2.63 mg of betamethasone sodium phosphate is equivalent to 2 mg of betamethasone.
The presence of betamethasone dipropionate provides prolonged activity of the drug. This component is practically insoluble and forms a depot at the injection site, resulting in slow absorption and sustained symptom relief over a longer period.
| Concentration in blood |
Intramuscular injection |
|
| betamethasone |
||
| sodium phosphate |
dipropionate |
|
| Maximum plasma concentration |
1 hour after administration |
slow absorption |
| Plasma half-life after a single dose |
3–5 hours |
progressive metabolism |
| Excretion |
24 hours |
more than 10 days |
| Biological half-life |
36–54 hours |
|
Metabolism of betamethasone occurs in the liver. Betamethasone is predominantly bound to albumin. In patients with impaired liver function, clearance of betamethasone is slower or delayed.
Clinical Characteristics
Indications
Corticosteroid therapy is an adjunctive, not an alternative, to conventional treatment.
Dermatological Diseases
Atopic dermatitis (nummular eczema), neurodermatitis (lichen simplex chronicus), contact dermatitis, severe solar dermatitis, urticaria, lichen planus, insulin-induced lipodystrophy, alopecia areata, discoid lupus erythematosus, psoriasis, keloid scars, pemphigus vulgaris, herpetic dermatitis, cystic acne.
Rheumatic Diseases
Rheumatoid arthritis, osteoarthritis, bursitis, tenosynovitis, tendinitis, peritendinitis, ankylosing spondylitis, epicondylitis, radiculitis, coccygodynia, sciatica, lumbar pain, torticollis, ganglion cyst, exostosis, fasciitis, acute gouty arthritis, synovial cysts, Morton's disease, cuboiditis, foot disorders, bursitis associated with hard callus, heel spurs, hallux rigidus.
Allergic Conditions
Bronchial asthma, status asthmaticus, hay fever, severe allergic bronchitis, seasonal and perennial allergic rhinitis, angioneurotic edema, contact dermatitis, atopic dermatitis, serum sickness, hypersensitivity reactions to drugs or insect bites.
Collagen Diseases
Systemic lupus erythematosus, scleroderma, dermatomyositis, polyarteritis nodosa.
Oncological Diseases
Palliative therapy of leukemia and lymphoma in adults, acute leukemia in children.
Other Diseases
Adrenogenital syndrome, ulcerative colitis, Crohn's disease, sprue, hematological disorders requiring corticosteroid therapy, nephritis, nephrotic syndrome.
Primary and secondary adrenal insufficiency (with concomitant administration of mineralocorticoids mandatory).
Contraindications
- Hypersensitivity to the active substances or to any of the excipients of the drug.
- Hypersensitivity to corticosteroids.
- Systemic fungal infections.
- Intramuscular administration in patients with idiopathic thrombocytopenic purpura.
Interaction with Other Medicinal Products and Other Types of Interactions
Interaction with Other Medicinal Products
Concomitant use of phenobarbital, rifampicin, phenytoin, or ephedrine may enhance corticosteroid metabolism, thereby reducing their therapeutic activity.
Patients receiving corticosteroid therapy should not receive:
- Smallpox vaccination;
- Other immunization methods (especially when high doses are used) due to the risk of neurological complications and inadequate antibody response.
However, immunization may be performed in patients receiving corticosteroids as replacement therapy (e.g., in Addison's disease).
Combination with diuretics such as thiazides may increase the risk of glucose intolerance.
Patients receiving concomitant corticosteroids and estrogens should be monitored for possible excessive corticosteroid effects.
Concomitant use of corticosteroids and cardiac glycosides may increase the risk of arrhythmias or signs of digitalis toxicity associated with hypokalemia. Patients taking cardiac glycosides often also receive diuretics causing potassium loss; in such cases, potassium levels must be closely monitored.
Corticosteroids may enhance potassium loss induced by amphotericin B. In all patients receiving any of these drug combinations, careful monitoring of serum electrolytes, especially serum potassium levels, is required.
Concomitant use of corticosteroids and coumarin-type anticoagulants may lead to an increase or decrease in anticoagulant effect, possibly requiring dose adjustment. In patients receiving anticoagulants in combination with glucocorticoids, the potential for corticosteroid-induced gastrointestinal ulceration or increased risk of internal bleeding should be considered.
Concomitant use may result in corticosteroids reducing plasma salicylate concentrations. Acetylsalicylic acid should be used with caution in combination with corticosteroids in patients with hypoprothrombinemia. When tapering corticosteroid doses or discontinuing treatment, patients should be monitored for possible salicylate poisoning. Combination of corticosteroids with salicylates may increase the frequency and severity of gastrointestinal ulcers.
Combined use of glucocorticosteroids with nonsteroidal anti-inflammatory drugs or alcohol may increase the risk of gastrointestinal ulceration or worsen existing ulcers. In diabetic patients, dosage adjustment of oral antidiabetic agents or insulin may be necessary due to the hyperglycemic effect of corticosteroids.
Concomitant administration of glucocorticosteroids and somatotropin may slow the absorption of the latter. When somatotropin is administered, doses of betamethasone exceeding 300–450 µg (0.3–0.45 mg) per m² of body surface area per day should be avoided.
Combined therapy with CYP3A inhibitors, including drugs containing cobicistat, is expected to increase the risk of systemic adverse effects. Concomitant use should be avoided unless the benefit outweighs the increased risk of systemic corticosteroid side effects; if such use is necessary, patients should be closely monitored for the development of systemic corticosteroid adverse effects.
Other Types of Interactions
Effect on Laboratory Tests
Corticosteroids may interfere with the nitroblue tetrazolium test and produce false-negative results.
Corticosteroid treatment should also be taken into account when interpreting biological parameters and test results in patients (skin tests, thyroid hormone levels).
Special precautions for use
Betafos suspension is not intended for intravenous or subcutaneous administration.
Serious neurological complications, including fatal outcomes, have been reported following epidural injection of corticosteroids. Among these complications, spinal cord infarction, paraplegia, quadriplegia, cortical blindness, and stroke have been reported. These serious neurological complications have occurred both with and without fluoroscopic guidance. Since the safety and efficacy of epidural administration have not been established, corticosteroids are not recommended for epidural use.
Anaphylactoid/anaphylactic reactions, including shock, have been reported rarely in patients receiving parenteral corticosteroid therapy. Appropriate precautionary measures should be taken in patients with a history of allergic reactions to corticosteroids.
Development of a pheochromocytoma crisis, including fatal outcomes, has been reported. Corticosteroids should be administered to patients with diagnosed or suspected pheochromocytoma only after appropriate benefit-risk assessment.
Strict adherence to aseptic techniques is mandatory when using this medicinal product.
Betafos contains two esters of betamethasone, one of which—betamethasone sodium phosphate—is rapidly absorbed from the injection site. Therefore, it should be considered that this soluble component of Betafos may have systemic effects.
Abrupt discontinuation or dose reduction after prolonged use (especially with very high doses over a short period) or during periods of increased corticosteroid requirement (due to stress: infection, trauma, surgery) may precipitate adrenal insufficiency. In such cases, dosage should be tapered gradually. During stress, corticosteroid therapy may need to be reinstituted or dosage increased.
Dosage reduction should be performed under strict medical supervision; sometimes monitoring of the patient may be required for up to one year after discontinuation of prolonged or high-dose therapy.
Symptoms of adrenal insufficiency include malaise, muscle weakness, mental disturbances, drowsiness, muscle and bone pain, skin desquamation, dyspnea, anorexia, nausea, vomiting, fever, hypoglycemia, hypotension, dehydration, and even death following abrupt discontinuation of therapy. Treatment of adrenal insufficiency consists of corticosteroids, mineralocorticoids, water, sodium chloride, and glucose.
Rapid intravenous administration of high-dose corticosteroids may lead to cardiovascular failure; therefore, the injection should be administered over a 10-minute period.
During prolonged corticosteroid therapy, transition from parenteral to oral administration should be considered after evaluation of potential benefits and risks.
When performing intra-articular injections, it is important to know that:
- such administration may produce local and systemic effects;
- examination of any fluid present in the joint is essential to exclude the possibility of septic processes;
- local injection should not be performed into previously infected joints;
- marked increase in pain and local swelling, further limitation of joint mobility, fever, and discomfort may indicate septic arthritis; if this infection is confirmed, appropriate antibacterial therapy should be initiated;
- corticosteroids must not be injected into unstable joints, infected areas, or the intervertebral space;
- repeated intra-articular injections in osteoarthritic joints may lead to increased joint destruction;
- after successful intra-articular therapy, the patient should avoid overloading the joint;
- corticosteroids must not be injected directly into tendons, as this may lead to tendon rupture.
Intramuscular injections of corticosteroids should be administered deeply into the muscle to prevent local tissue atrophy.
Injection of corticosteroids into soft tissue, lesion sites, or joints may result in systemic and local effects.
Special patient groups at risk
Betamethasone may be used in diabetic patients only for a short duration and under strict medical supervision due to its glucocorticoid properties (conversion of proteins into glucose).
Enhanced glucocorticoid effects have been observed in patients with hypothyroidism or hepatic cirrhosis.
Use of Betafos should be avoided in patients with herpetic eye disease (due to the risk of corneal perforation).
Psychiatric disturbances may occur during corticosteroid therapy. Treatment with corticosteroids may increase susceptibility to emotional instability or psychosis.
Precautionary measures are necessary in the following conditions: nonspecific ulcerative colitis, risk of perforation, abscess or other pyogenic infections; diverticulitis; intestinal anastomoses; gastric or duodenal ulcer; renal insufficiency; arterial hypertension; osteoporosis; severe myasthenia; glaucoma; acute psychosis; viral and bacterial infections; growth retardation; tuberculosis; Cushing's syndrome; diabetes; heart failure; difficult-to-treat epilepsy; predisposition to thromboembolism or thrombophlebitis; and during pregnancy.
Since complications associated with corticosteroid therapy depend on dose and duration of treatment, the benefit-risk ratio must be carefully considered for each patient when selecting dosage and treatment duration.
Corticosteroid therapy may mask signs of infection or complicate its diagnosis. Due to decreased resistance during such therapy, new infections may arise.
Prolonged treatment may lead to the development of posterior subcapsular cataract (especially in children) or glaucoma, which may damage the optic nerve and increase the risk of secondary fungal or viral ocular infections. Regular ophthalmological examinations are necessary during prolonged therapy (more than 6 weeks).
Moderate to high doses of corticosteroids may cause elevated blood pressure, fluid and sodium retention, and increased potassium excretion. These effects are less likely with synthetic derivatives unless used in high doses. A low-salt diet and potassium supplementation may be considered. All corticosteroids accelerate calcium excretion from the body.
Patients receiving corticosteroid therapy should not receive the following treatments:
- smallpox vaccination;
- other immunization methods (especially with high-dose corticosteroids) due to the risk of neurological complications and inadequate antibody response.
However, immunization may be performed in patients receiving corticosteroids as replacement therapy (e.g., in Addison's disease).
Patients, particularly children, receiving immunosuppressive doses of corticosteroids should avoid contact with individuals with chickenpox or measles.
Administration of corticosteroids in active tuberculosis is possible only in rapidly progressive or disseminated tuberculosis, in combination with adequate antituberculosis therapy. If corticosteroids are administered to patients with latent tuberculosis or those with a positive tuberculin reaction, close monitoring is essential, as reactivation of the disease may occur. Patients undergoing prolonged corticosteroid therapy should also receive chemoprophylaxis. If rifampicin is used in the chemoprophylaxis regimen, enhanced hepatic metabolic clearance of corticosteroids should be monitored; dose adjustment of corticosteroids may be necessary.
Since corticosteroids may impair growth in children, including infants, and suppress endogenous corticosteroid production, careful monitoring of growth and development is essential during prolonged therapy.
Changes in sperm motility and count may occur in some patients during glucocorticoid therapy.
Betafos contains benzyl alcohol, which may cause toxic reactions and anaphylactoid reactions in infants and children under 3 years of age. This product should not be used in premature infants or full-term newborns.
Betafos contains methylparahydroxybenzoate (E 218) and propylparahydroxybenzoate (E 216), which may cause allergic reactions (possibly delayed), and in rare cases, respiratory distress.
This medicinal product contains less than 1 mmol (23 mg)/dose of sodium, i.e., essentially "sodium-free".
Visual disturbances
Visual disturbances may occur with systemic and local (including intranasal, inhaled, and intraocular) corticosteroid administration. If symptoms such as blurred vision or other visual disturbances occur, patients should undergo ophthalmological examination to evaluate possible causes, including cataract, glaucoma, or rare conditions such as central serous chorioretinopathy, which has been reported after systemic and local corticosteroid use.
Use during pregnancy or breastfeeding
Due to the lack of controlled safety studies, glucocorticoids should be prescribed to pregnant women, breastfeeding women, and women of reproductive age only after careful evaluation of benefit to the mother versus potential risk to the embryo/fetus.
Pregnancy
When prescribing corticosteroids during the prenatal period, the benefits and disadvantages of such therapy and its clinical effects should be weighed against potential adverse effects (including growth suppression and increased risk of infections).
In some cases, corticosteroid therapy may need to be continued or even increased during pregnancy (e.g., in corticosteroid replacement therapy).
Intramuscular administration of betamethasone significantly reduces the incidence of respiratory distress in the fetus when administered more than 24 hours before delivery (before the 32nd week of pregnancy).
Published data indicate that the use of prophylactic corticosteroids after the 32nd week of pregnancy remains controversial. Therefore, when prescribing corticosteroids after the 32nd week of pregnancy, the physician must carefully weigh all benefits of such therapy against potential risks to the mother and fetus.
Corticosteroids should not be used to treat hyaline membrane disease in newborns.
Prophylactic treatment of hyaline membrane disease in preterm infants should not be administered to pregnant women with pre-eclampsia or eclampsia or those with placental pathology.
Infants whose mothers received significant doses of corticosteroids during pregnancy should be under medical supervision (to detect signs of adrenal insufficiency).
Administration of betamethasone to pregnant women before delivery has been associated with transient suppression of embryonic growth hormone activity and possibly pituitary hormones regulating steroid production in both definitive and fetal zones of the fetal adrenal glands. However, suppression of fetal hydrocortisone production did not affect pituitary-adrenal responses to stress after delivery.
Since corticosteroids cross the placenta, newborns and infants whose mothers received corticosteroids during most or part of pregnancy should be carefully examined for rare congenital cataracts.
Women who received corticosteroids during pregnancy should be monitored during and after labor and during delivery to detect adrenal insufficiency due to stress associated with childbirth.
Studies have shown an increased risk of neonatal hypoglycemia after a short antenatal course of betamethasone in women at risk of late preterm delivery.
Breastfeeding
Corticosteroids cross the placental barrier and are excreted in breast milk.
Since Betafos may cause adverse effects in breastfed infants, a decision should be made whether to discontinue breastfeeding or discontinue therapy, taking into account the importance of the therapy for the mother.
Ability to affect reaction speed when driving or operating machinery
Caution should be exercised due to central nervous system effects associated with high-dose administration (e.g., euphoria, insomnia) and visual disturbances that may occur during prolonged therapy (see "Side effects" section for details).
Method of Administration and Dosage
Shake before use.
The dosage regimen is determined individually by a physician, depending on the indications, severity of the disease, and the patient's clinical response to treatment.
Dosage
The dose should be the lowest possible, and the duration of treatment – as short as feasible. The initial dose should be selected to achieve a satisfactory clinical effect. If a satisfactory clinical response is not observed within a certain period of time, treatment with the drug should be discontinued gradually by tapering the dose, and alternative appropriate therapy should be initiated.
In case of a favorable response, the appropriate maintenance dose should be established by gradually reducing the initial dose in acceptable increments until the lowest effective dose producing the desired clinical response is reached.
Method of Administration
Betafos suspension is not intended for intravenous or subcutaneous administration.
Systemic Administration
In systemic use, treatment is usually initiated with 1–2 mL of the drug, which may be repeated as necessary. The dosage and frequency of administration depend on the severity of the patient's condition and response to therapy. The drug should be administered by deep intramuscular injection into the gluteal muscle:
- In severe conditions (systemic lupus erythematosus and asthmatic status) requiring emergency intervention, the initial dose may be 2 mL;
- In various dermatological conditions, 1 mL administered intramuscularly is usually sufficient; repeat injections may be given depending on the response to treatment;
- In respiratory diseases, symptom relief is achieved within several hours after intramuscular injection of Betafos. In bronchial asthma, hay fever, allergic bronchitis, and allergic rhinitis, significant improvement is usually observed after administration of 1–2 mL of the drug;
- In acute and chronic bursitis, the intramuscular dose is 1–2 mL of the drug. Several repeat injections may be necessary if required.
Local Administration
Concomitant use of a local anesthetic agent is required only in isolated cases (the injection is practically painless). If concomitant administration of a local anesthetic is desired, Betafos may be mixed (in the syringe, not in the vial) with 1% or 2% lidocaine hydrochloride or procaine hydrochloride solution, or similar local anesthetics, using formulations that do not contain parabens. Anesthetics containing methylparaben, propylparaben, phenol, or other similar substances are not permitted. When using an anesthetic in combination with Betafos, first draw the required dose of the drug from the vial into the syringe, then add the required amount of local anesthetic into the same syringe and shake the syringe briefly.
In acute bursitis (subdeltoid, subscapular, olecranon, and prepatellar), injection of 1–2 mL of Betafos into the bursa provides pain relief and full restoration of mobility within several hours.
Treatment of chronic bursitis should be performed with lower doses of the drug after suppression of acute symptoms.
In acute tenosynovitis, tendinitis, and peritendinitis, a single injection of Betafos may relieve the patient's condition; in chronic cases, repeat injections may be necessary depending on the patient's condition.
In rheumatoid arthritis and osteoarthritis, intra-articular injection of Betafos in a dose of 0.5–2 mL may reduce pain, tenderness, and joint stiffness within 2–4 hours after administration. The duration of therapeutic effect varies significantly and may last 4 weeks or longer. Intra-articular administration of Betafos is well tolerated by the joint and periarticular tissues.
Recommended doses for injection:
- into large joints (e.g., knee, hip) – 1–2 mL;
- into medium joints (e.g., elbow) – 0.5–1 mL;
- into small joints (e.g., wrist) – 0.25–0.5 mL.
In dermatological conditions, effective treatment is achieved by intradermal injection of the drug directly into the lesion site. Response in some lesions not treated directly may be due to a minor systemic effect of the drug. Inject 0.2 mL/cm² of Betafos intradermally (not subcutaneously) using a tuberculin syringe and a 26 G needle. The total amount of drug administered at the injection site should not exceed 1 mL.
Foot disorders sensitive to corticosteroids. Bursitis under a callus can be treated with two consecutive injections of 0.25 mL each. Conditions such as hallux rigidus (flexion contracture of the big toe), varus deformity of the little toe (inward deviation of the fifth toe), and acute gouty arthritis may respond very quickly. For most foot injections, a tuberculin syringe with a 25 G needle 1.9 cm in length is suitable.
Recommended doses of Betafos (with intervals between injections approximately 1 week):
- bursitis under a callus – 0.25–0.5 mL;
- heel spur – 0.5 mL;
- hallux rigidus – 0.5 mL;
- varus deformity of the little toe – 0.5 mL;
- ganglion cyst – 0.25–0.5 mL;
- Morton’s metatarsalgia – 0.25–0.5 mL;
- tenosynovitis – 0.5 mL;
- cuboid bone inflammation – 0.5 mL;
- acute gouty arthritis – 0.5–1 mL.
Children
There is insufficient clinical data on the use of the drug in children; therefore, its use in this age group is not recommended (risk of growth retardation and development of secondary adrenal insufficiency).
Overdose
Symptoms. Acute overdose of glucocorticoids, including betamethasone, does not typically create life-threatening situations. Administration of high doses of glucocorticosteroids over several days does not usually lead to adverse consequences (except in cases of very high doses or in patients with diabetes mellitus, glaucoma, acute exacerbation of erosive-ulcerative gastrointestinal lesions, or in patients concurrently receiving cardiac glycosides, coumarin anticoagulants, or potassium-depleting diuretics).
Treatment. In case of complications arising from metabolic effects of corticosteroids, adverse outcomes of the primary or concomitant diseases, or drug interactions, appropriate treatment should be administered. Adequate fluid intake should be maintained, and plasma and urinary electrolyte levels (especially sodium and potassium balance) should be monitored. Appropriate therapy should be initiated if an imbalance of these ions is detected.
Side effects
Adverse events observed during the use of Betaphos, as with other corticosteroids, are dose- and duration-dependent.
Among the side effects associated with corticosteroids in general, the following effects should be particularly noted:
Electrolyte and fluid balance disturbances: sodium retention, increased potassium excretion, hypokalemic alkalosis, fluid retention, congestive heart failure in predisposed patients, hypertension, increased calcium excretion.
Musculoskeletal system disorders: muscle weakness, loss of muscle mass, worsening of myasthenic symptoms in severe pseudoparalytic myasthenia, osteoporosis sometimes with severe bone pain and spontaneous fractures (vertebral compression fractures), aseptic necrosis of femoral or humeral heads, tendon ruptures, steroid myopathy, pathological fractures, joint instability.
Skin disorders: skin atrophy, impaired wound healing, thinning and weakening of the skin, petechiae, bruising, skin reactions such as allergic dermatitis, angioneurotic edema, facial erythema, excessive sweating, urticaria.
Gastrointestinal disorders: gastric ulceration with possible perforation and hemorrhage, pancreatitis, abdominal distension, intestinal perforation, esophageal ulcers, nausea, vomiting, hiccups.
Nervous system disorders: convulsions, dizziness, headache, migraine, increased intracranial pressure (pseudotumor cerebri).
Psychiatric disorders: euphoria, mood changes, personality changes, severe depression, increased irritability, insomnia, psychotic reactions (especially in patients with a history of psychiatric disorders), depression.
Eye disorders: increased intraocular pressure (pseudotumor cerebri: see Nervous system disorders), glaucoma, posterior subcapsular cataract, exophthalmos, blurred vision (see also section "Special precautions").
Endocrine system disorders: clinical features of Cushing's syndrome, menstrual cycle disturbances, increased requirement for insulin injections or oral antidiabetic agents in diabetic patients, impaired fetal or childhood growth, impaired carbohydrate tolerance, manifestation of latent diabetes mellitus, secondary suppression of the pituitary and adrenal cortex – particularly harmful under stress conditions (trauma, surgery, or illness).
Metabolic disorders: negative nitrogen balance due to protein catabolism, lipomatosis, weight gain.
Immune system disorders: corticosteroids may suppress skin test reactions, mask signs of infection, activate latent infections, and reduce resistance to infections, particularly to mycobacteria, tuberculosis, Candida albicans, and viruses.
Other disorders: anaphylactic or allergic reactions, hypotensive reactions, or shock-related reactions.
The following adverse reactions may occur with parenteral administration of corticosteroids:
Rare cases of blindness associated with injection into lesions in the head area, including the face, hyper- or hypopigmentation, subcutaneous and cutaneous atrophy, aseptic abscesses, post-injection flare (after intra-articular injection), and Charcot arthropathy.
Repeated intra-articular injections may lead to joint damage. There is a risk of infection.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after medicine authorization is important. It allows ongoing monitoring of the benefit-risk balance of the medicine. Healthcare professionals, pharmacists, patients, and their legal representatives are encouraged to report any suspected adverse reactions and lack of efficacy through the automated pharmacovigilance information system at https://aisf.dec.gov.ua.
Shelf life
2 years.
Storage conditions
Store in the original packaging protected from light at a temperature not exceeding 25 °C.
Incompatibilities
Occasionally, simultaneous administration with a local anesthetic may be required. If Betaphos needs to be administered together with a local anesthetic, it may be mixed (in a syringe, not in the vial) with 1% or 2% lidocaine hydrochloride or procaine hydrochloride solutions, provided these do not contain parabens. Similar local anesthetics may also be used. However, anesthetics containing methylparaben, propylparaben, or phenol should be avoided.
Packaging
1 ml in ampoule, 5 ampoules per cardboard pack.
Prescription status
Prescription only.
Manufacturer
K.T. Rompharm Company S.R.L. / S.C. Rompharm Company S.R.L.
Manufacturer's address and location of operations
Str. Eroilor No. 1A, Otopeni, 075100, Ilfov County, Romania – Rompharm 1 and Rompharm 2 buildings / Eroilor str. No 1A, Otopeni city, 075100, county Ilfov, Romania – building Rompharm 1 and Rompharm 2.
Similar drugs
| Brand name | Dosage form | Active substance / Dosage | Manufacturer |
|---|---|---|---|
| DEPOS | suspension for injection |
|
Farmak JSC |
| DIPROSPAN® | suspension for injection |
|
Organon Heist bv (for ampoules: manufacturer with full cycle; for pre-filled syringes: manufacturer with full cycle) |
| FLOSTERON | suspension for injection |
|
KRKA, d.d., Novo mesto |
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026