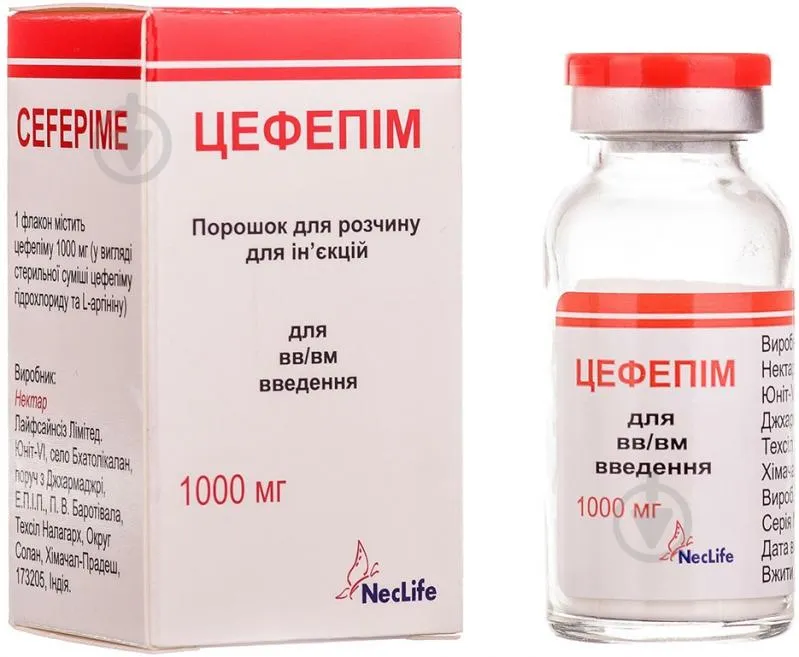
CEFEPIME-O
UkraineThe drug is used to treat various infections caused by susceptible bacteria, including pneumonia, urinary tract infections (including pyelonephritis), skin infections, bacteremia, and complicated intra-abdominal infections.
Frequently asked questions
How should Cefepime-o be taken correctly?
The drug is administered intravenously or intramuscularly. The usual dose for adults is 1 g every 12 hours. The duration of the course is typically 7–10 days. Dosage may vary depending on the severity of the infection, bacterial susceptibility, and the patient's renal status.
What are the contraindications for use?
The drug must not be taken in case of hypersensitivity to cefepime, L-arginine, as well as to cephalosporins, penicillins, or other β-lactam antibiotics.
What side effects may Cefepime-o cause?
Possible reactions include gastrointestinal (diarrhea, nausea, abdominal pain), nervous system (headache, convulsions, altered consciousness), skin (itching, rash), as well as allergic reactions (edema, anaphylaxis). Changes in blood test results and renal impairment are also possible.
Can the drug be taken with other medicines?
Caution is required when used simultaneously with high doses of aminoglycosides (due to the risk of renal impact) and diuretics. The drug solution must not be mixed in the same container with metronidazole, vancomycin, gentamicin, tobramycin, and netilmicin.
Is dosage adjustment necessary for kidney diseases?
Yes, patients with impaired renal function must have their dose or administration intervals adjusted, as the drug is primarily excreted by the kidneys.
Can the drug be used during pregnancy or breastfeeding?
In pregnant women, the drug is prescribed only when the expected benefit to the mother outweighs the risk to the fetus. Since the drug passes into breast milk, the decision to use it or to discontinue breastfeeding must be made by a physician.
Instructions for use
INSTRUCTION for medical use of the medicinal product CEFEPIME-O (CEFEPIME-O)
Composition:
Active substance: cefepime;
1 vial contains cefepime hydrochloride equivalent to cefepime 1 g;
Excipient: L-arginine.
Pharmaceutical form. Powder for solution for injection.
Main physical and chemical characteristics: powder from white to light yellow color.
Pharmacotherapeutic group.
Other β-lactam antibiotics. Fourth-generation cephalosporins. Cefepime.
ATC code J01D E01.
Pharmacological Properties
Pharmacodynamics
Cefepime inhibits the synthesis of enzymes involved in the bacterial cell wall formation and has a broad spectrum of activity against various Gram-positive and Gram-negative bacteria.
Cefepime is highly resistant to hydrolysis by most β-lactamases, has low affinity for chromosomally mediated β-lactamases, and rapidly penetrates Gram-negative bacterial cells.
Cefepime is active against the following microorganisms:
Gram-positive aerobes:
Staphylococcus aureus (only methicillin-susceptible strains);
Streptococcus pneumoniae;
Streptococcus pyogenes (Group A streptococci);
Viridans group streptococci;
Gram-negative aerobes:
Enterobacter spp.;
Escherichia coli;
Klebsiella pneumoniae;
Proteus mirabilis;
Pseudomonas aeruginosa.
There are available in vitro study data, but their clinical significance has not been established. It is known that cefepime exhibits in vitro activity against the majority of strains of the following microorganisms; however, the safety and efficacy of cefepime in treating clinical infections caused by these microorganisms have not been established in adequate and well-controlled clinical trials:
Gram-positive aerobes:
Staphylococcus epidermidis (only methicillin-susceptible strains);
Staphylococcus saprophyticus;
Streptococcus agalactiae (Group B streptococci).
Note: Most strains of enterococci, e.g., Enterococcus faecalis, and methicillin-resistant staphylococci are resistant to cefepime.
Gram-negative aerobes:
Acinetobacter calcoaceticus subsp. lwoffii;
Citrobacter diversus;
Citrobacter freundii;
Enterobacter agglomerans;
Haemophilus influenzae (including β-lactamase-producing strains);
Hafnia alvei;
Klebsiella oxytoca;
Moraxella catarrhalis (including β-lactamase-producing strains);
Morganella morganii;
Proteus vulgaris;
Providencia rettgeri;
Providencia stuartii;
Serratia marcescens.
Note: Cefepime is inactive against many strains of Stenotrophomonas (previously Xanthomonas maltophilia and Pseudomonas maltophilia).
Anaerobic microorganisms:
Clostridium difficile.
Pharmacokinetics
The mean plasma concentrations of cefepime observed in healthy adult male volunteers at various time points after a single 30-minute infusion of cefepime at doses of 500 mg, 1 g, and 2 g are presented in Table 1. Cefepime is eliminated primarily by renal excretion. In healthy volunteers, the mean elimination half-life is 2.0 (± 0.3) hours, the total clearance is 120.0 (± 8.0) mL/min, and no drug accumulation has been observed. The pharmacokinetics of cefepime are linear over the dose range of 250 mg to 2 g.
Absorption
Mean plasma concentrations of cefepime in healthy adult volunteers at various time points after single intravenous and intramuscular administration are presented in the table.
Plasma concentrations of cefepime (mcg/mL) after intravenous (IV) and intramuscular (IM) administration, Table 1:
| Cefepime dose |
0.5 hours |
1 hour |
2 hours |
4 hours |
8 hours |
12 hours |
Cmax, mcg/mL |
T1/2max, hours |
AUC, hours× mcg/mL |
Number of patients (n) |
| 500 mg IV |
38.2 |
21.6 |
11.6 |
5.0 |
1.4 |
0.2 |
39.1 (3.5) |
- |
70.8 (6.7) |
9 |
| 1 g IV |
78.7 |
44.5 |
24.3 |
10.5 |
2.4 |
0.6 |
81.7 (5.1) |
- |
148.5 (15.1) |
9 |
| 2 g IV |
163.1 |
85.8 |
44.8 |
19.2 |
3.9 |
1.1 |
163.9 (25.3) |
- |
284.8 (30.6) |
9 |
| 500 mg IM |
8.2 |
12.5 |
12.0 |
6.9 |
1.9 |
0.7 |
13.9 (3.4) |
1.4 (0.9) |
60 (8) |
6 |
| 1 g IM |
14.8 |
25.9 |
26.3 |
16.0 |
4.5 |
1.4 |
29.6 (4.4) |
1.6 (0.4) |
137 (11) |
6 |
| 2 g IM |
36.1 |
49.9 |
51.3 |
31.5 |
8.7 |
2.3 |
57.5 (9.5) |
1.5 (0.4) |
262 (23) |
12 |
Distribution.
The mean volume of distribution of cefepime is 18.0 (± 2.0) L. Cefepime binding to plasma proteins is approximately 20% and is independent of its concentration.
Therapeutic concentrations of cefepime are achieved in urine, bile, peritoneal fluid, bronchial mucous secretions, sputum, prostate, appendix, and gallbladder.
Cefepime is also excreted into breast milk. Infants consuming approximately 1000 mL of breast milk per day receive approximately 0.5 mg of cefepime daily (see section "Use during pregnancy or breastfeeding").
Cefepime concentrations in tissues and body fluids are presented in the table.
Mean cefepime concentrations in body fluids (µg/mL) or tissues (µg/g), Table 2:
| Tissue or fluid |
Dose / route of administration |
Number of patients |
Mean time after dose administration (hours) |
Mean concentration |
| Fluid from skin vesicles bullae |
2 g intravenously |
6 |
1.5 |
81.4 µg/mL |
| Bronchial mucosal secretions |
2 g intravenously |
20 |
4.8 |
24.1 µg/g |
| Sputum |
2 g intravenously |
5 |
4.0 |
7.4 µg/mL |
| Urine |
500 mg intravenously |
8 |
0–4 |
292 µg/mL |
| 1 g intravenously |
12 |
0–4 |
926 µg/mL |
|
| 2 g intravenously |
12 |
0–4 |
3120 µg/mL |
|
| Bile |
2 g intravenously |
26 |
9.4 |
17.8 µg/mL |
| Peritoneal fluid |
2 g intravenously |
19 |
4.4 |
18.3 µg/mL |
| Appendix |
2 g intravenously |
31 |
5.7 |
5.2 µg/g |
| Gallbladder |
2 g intravenously |
38 |
8.9 |
11.9 µg/g |
| Prostate |
2 g intravenously |
5 |
1.0 |
31.5 µg/g |
There are data indicating that cefepime crosses the blood-brain barrier. The clinical significance of these data is currently undefined.
Metabolism and excretion.
Cefepime is metabolized to N-methylpyrrolidine, which is rapidly converted to the N-methylpyrrolidine oxide. The mean total clearance is 120 mL/min. Cefepime is eliminated from the body almost exclusively via renal elimination mechanisms (mean renal clearance—110 mL/min). Approximately 85% of the administered dose is excreted in urine as unchanged cefepime, 1% as N-methylpyrrolidine, about 6.8% as N-methylpyrrolidine oxide, and about 2.5% as the cefepime epimer. Since renal excretion is a major elimination pathway, dosage adjustment is required for patients with impaired renal function and for patients undergoing hemodialysis (see "Administration and dosage" and "Distribution").
Patients with renal impairment.
Studies conducted in patients with varying degrees of renal impairment have demonstrated an increased elimination half-life. On average, the half-life in patients with severe renal dysfunction requiring dialysis treatment is 13 hours during hemodialysis and 19 hours during peritoneal dialysis.
Total cefepime clearance in patients with impaired renal function decreases proportionally to creatinine clearance—this forms the basis for dosage recommendations in this patient group (see "Administration and dosage").
Patients with hepatic impairment.
The pharmacokinetics of cefepime in patients with impaired liver function or cystic fibrosis who received a single 1 g dose were not altered. Dose adjustment is not necessary for these patients.
Elderly patients.
The pharmacokinetics of cefepime were studied in elderly patients (over 65 years of age), with a mean creatinine clearance of 74.0 (±15.0) mL/min. It appears that the reduction in total cefepime clearance depends on creatinine clearance. Therefore, cefepime dosage should be appropriately adjusted in elderly patients if their creatinine clearance is 60 mL/min or less (see "Administration and dosage").
Children.
The pharmacokinetics of cefepime were studied in children aged 2 months to 11 years after administration of single and multiple doses every 8 and every 12 hours. After a single intravenous dose, the mean total clearance and volume of distribution were 3.3 (±1.0) mL/min/kg and 0.3 (±0.1) L/kg, respectively. Approximately 60.4 (±30.4)% of the administered dose is recovered in urine as unchanged cefepime, and the mean renal clearance is 2.0 (±1.1) mL/min/kg. No significant effect of age or gender on total clearance or body weight-adjusted volume of distribution was observed. No accumulation of cefepime was observed with administration of 50 mg/kg every 12 hours, whereas Cmax, AUC, and T½ increased by approximately 15% after administration of 50 mg/kg every 8 hours. Cefepime exposure following a 50 mg/kg intravenous dose in children is comparable to that in adults receiving a 2 g intravenous dose. The absolute bioavailability of cefepime after intramuscular administration of a 50 mg/kg dose was 82.3 (±15)%.
The use of cefepime is supported by adequate and well-controlled studies in adults, supplemented by pharmacokinetic and safety studies in children. Safety and efficacy in children under 2 months of age have not been established.
Antimicrobial susceptibility testing. Dilution methods.
Minimum inhibitory concentrations (MICs) established by the European Committee on Antimicrobial Susceptibility Testing (EUCAST), Table 3:
| MIC, mg/ml |
|||
| Microorganism |
Susceptible |
Moderately susceptible |
Resistant |
| Microorganisms other than Haemophilus spp.* and Streptococcus pneumoniae* |
≤ 8 |
16 |
≥ 32 |
| Haemophilus spp.* S. pneumoniae* |
≤ 2 |
−* |
−* |
| Streptococcus pneumoniae* |
≤ 0.5 |
1 |
≥ 2 |
* Strains of these species should be tested for susceptibility using specialized susceptibility testing methods. Strains of Haemophilus spp. with MICs greater than 2 μg/mL should be considered suspect and should be further evaluated.
Clinical characteristics.
Indications.
Adults.
Infections caused by microorganisms sensitive to the drug:
- pneumonia;
- empirical therapy in patients with febrile neutropenia;
- uncomplicated and complicated urinary tract infections (including pyelonephritis);
- uncomplicated skin and skin structure infections;
- complicated intra-abdominal infections (in combination with metronidazole);
- bacteremia.
Children.
- pneumonia;
- uncomplicated and complicated urinary tract infections (including pyelonephritis);
- uncomplicated skin and skin structure infections;
- empirical therapy in patients with febrile neutropenia.
Contraindications.
Hypersensitivity to cefepime or L-arginine, as well as to cephalosporins, penicillins, or other β-lactam antibiotics.
Interaction with other medicinal products and other types of interactions.
When administering high doses of aminoglycosides concomitantly with the medicinal product Cefepime-O, renal function should be closely monitored due to the potential nephrotoxicity and ototoxicity of aminoglycoside antibiotics. Nephrotoxicity has been reported after concomitant administration of other cephalosporins with diuretics such as furosemide.
Cefepime-O at concentrations from 1 to 40 mg/mL is compatible with the following parenteral solutions: 0.9% sodium chloride injection; 5% and 10% glucose injection; 6M sodium lactate injection; 5% glucose and 0.9% sodium chloride injection; Ringer's lactate with 5% glucose injection.
To avoid potential drug interactions with other medicinal products, cefepime solutions (like most β-lactam antibiotics) should not be administered simultaneously with solutions of metronidazole, vancomycin, gentamicin, tobramycin sulfate, or netilmicin sulfate.
When cefepime is prescribed together with the above-mentioned drugs, each antibiotic should be administered separately.
Effect on laboratory test results.
Administration of cefepime may cause false-positive glucose in urine tests when using Benedict's reagent. It is recommended to use glucose tests based on enzymatic glucose oxidation reaction.
Special precautions for use.
For patients at high risk of severe infections (e.g., patients with a history of bone marrow transplantation and reduced activity due to severe progressive malignant hemolytic disease with severe progressive neutropenia), monotherapy may be insufficient; therefore, combination antimicrobial therapy is indicated.
Appropriate tests should be performed to identify and determine the pathogen's (or pathogens') susceptibility to cefepime. Cefepime may be used as monotherapy prior to pathogen identification, due to its broad spectrum of antibacterial activity against both gram-positive and gram-negative microorganisms.
As with other drugs in this class, serious adverse reactions such as reversible encephalopathy (including confusion and clouding of consciousness), myoclonia, seizures, and/or renal failure have been observed most frequently in patients with renal impairment who received doses exceeding the recommended dose, or in elderly patients with renal impairment receiving recommended doses of cefepime. Cases of such reactions have been reported in patients who received doses adjusted according to their renal function. In most cases, symptoms of nephrotoxicity were reversible and resolved after discontinuation of cefepime and/or after hemodialysis.
It is essential to determine whether the patient has previously experienced immediate-type hypersensitivity reactions to cefepime, cephalosporins, penicillins, or other β-lactam antibiotics. Antibiotics should be administered cautiously to all patients with any type of allergy, especially drug allergies. If an allergic reaction occurs, the drug should be discontinued. Severe immediate-type hypersensitivity reactions may require administration of epinephrine and other symptomatic treatments.
Use with caution in patients with gastrointestinal disorders, particularly colitis. Broad-spectrum antibiotics, especially when used long-term, may cause pseudomembranous colitis of varying severity, including fatal outcomes. Therefore, diarrhea occurring during cefepime therapy should be monitored. Mild forms of colitis may resolve spontaneously after discontinuation of therapy, while moderate or severe cases may require specific treatment.
Antibacterial agents alter the normal flora of the large intestine and may promote overgrowth of Clostridium. Studies indicate that the toxin produced by Clostridium difficile is the primary cause of antibiotic-associated colitis. After confirming the diagnosis of pseudomembranous colitis, appropriate measures should be taken. Symptoms of mild pseudomembranous colitis may resolve after discontinuation of the drug. In moderate to severe cases, administration of fluids and electrolytes, proteins, and an antibacterial agent effective against Clostridium difficile should be considered.
As with other antibiotics, use of the drug may lead to colonization of the intestine by microorganisms resistant to it. If superinfections develop during treatment, appropriate measures should be taken.
During prolonged therapy, liver and kidney function tests and hematological parameters should be monitored regularly.
The pharmacokinetics of cefepime in patients with impaired liver function are not altered. Dose adjustment is not required in such patients.
Patients with impaired renal function (creatinine clearance ≤ 60 mL/min) should have their dose adjusted to compensate for reduced elimination rate. Since antibiotic serum concentrations remain elevated for longer periods in patients with renal impairment or other conditions that may worsen renal function—even at usual doses—maintenance doses should be reduced in these patients. When determining the next dose, the degree of renal impairment, severity of infection, and microbial susceptibility to the drug should be considered.
Dose adjustment is not required for patients aged 65 years and older with normal renal function, despite their lower renal clearance compared to younger patients. However, elderly patients may have reduced renal function; therefore, caution should be exercised when dosing, and renal function should be closely monitored.
Severe adverse reactions, including life-threatening ones such as encephalopathy, myoclonus, and seizures, have been observed in elderly patients with renal impairment who received unadjusted doses of cefepime (see section "Adverse Reactions").
This drug is primarily excreted by the kidneys, and the risk of toxic reactions is higher in patients with impaired renal function. Since elderly patients are more likely to have decreased renal function, dose adjustment is recommended, and renal function should be carefully monitored.
Prothrombin time should be monitored. Many cephalosporins, including cefepime, are associated with reduced prothrombin activity. High-risk patients include those with impaired liver or kidney function, those who are poorly nourished, and those receiving prolonged courses of antimicrobial therapy. Prothrombin levels should be monitored in high-risk patients, and vitamin K should be administered if necessary.
During cefepime therapy, positive results in the direct Coombs test may occur. When performing hematological or transfusion procedures involving blood group determination by cross-matching, or when performing the Coombs test in newborns whose mothers received cephalosporin antibiotics before delivery, it should be considered that a positive Coombs test may be due to drug administration.
L-arginine is known to alter glucose metabolism and simultaneously increase serum glucose and calcium levels when administered at doses 33 times higher than the maximum recommended dose of cefepime. Effects at lower doses are currently unknown.
When lidocaine is used as a solvent, safety information regarding lidocaine should be taken into account.
Use during pregnancy or breastfeeding.
Adequate and well-controlled studies in pregnant women have not been conducted; therefore, Cefepime-O should be prescribed during pregnancy only if the expected benefit to the mother outweighs the potential risk to the fetus.
Cefepime is excreted in breast milk in very low concentrations (0.5 mcg/mL). The decision whether to discontinue breastfeeding or to discontinue the drug should be made by the physician, taking into account the benefits of breastfeeding for the infant and the therapeutic benefit for the mother.
Ability to influence reaction rate when driving or operating machinery.
Not studied. If dizziness or other adverse reactions occur, patients should refrain from driving or operating machinery.
Method of administration and dosage.
The usual dose for adults is 1 g, administered intravenously or intramuscularly every 12 hours. The usual duration of treatment is 7–10 days; severe infections may require longer therapy.
Dosage and route of administration vary depending on microbial susceptibility, severity of infection, and the patient's renal function.
Dosage recommendations for cefepime in adults with creatinine clearance greater than
60 mL/min are shown in Table 4:
| Type of infection |
Dose |
Dosing frequency |
Duration of treatment (days) |
| Adults: |
|||
| Pneumonia (moderate to severe), caused by S. pneumoniae , P. aeruginosa , K. pneumoniae , or Enterobacter species * |
1−2 g intravenously |
Every 12 hours |
10 |
| Empirical therapy in febrile neutropenic patients |
2 g intravenously |
Every 8 hours |
7** |
| Uncomplicated or complicated urinary tract infections (including pyelonephritis) of mild to moderate severity, caused by E. coli , K. pneumoniae , or P. mirabilis* |
0.5−1 g intravenously, intramuscularly*** |
Every 12 hours |
7−10 |
| Severe uncomplicated or complicated urinary tract infections, including pyelonephritis, caused by E. coli , K. pneumoniae* |
2 g intravenously |
Every 12 hours |
10 |
| Uncomplicated skin and soft tissue infections of moderate or severe severity, caused by S. aureus or S. pyogenes |
2 g intravenously |
Every 12 hours |
10 |
| Complicated intra-abdominal infections (used in combination with metronidazole), caused by E. coli , viridans group streptococci , P. aeruginosa , K. pneumoniae , Enterobacter species , or B. fragilis. |
2 g intravenously |
Every 12 hours |
7−10 |
* including cases of bacteremia associated or potentially associated with any of the specified infections.
** or until resolution of neutropenia. In patients without fever but with neutropenia persisting for more than 7 days, antimicrobial therapy should be re-evaluated.
*** intramuscular administration is indicated only for mild to moderate uncomplicated or complicated urinary tract infections caused by E. coli; intramuscular injection is considered more appropriate for administration of the drug.
Renal function impairment.
For patients with impaired renal function (creatinine clearance less than 60 mL/min), the dose of the drug should be adjusted according to Table 5:
| Creatinine clearance, (mL/min) |
Recommended doses |
|||
| Normal: 60 and above |
Standard dosing according to severity of infection, no dose adjustment required |
|||
| 500 mg every 12 hours |
1 g every 12 hours |
2 g every 12 hours |
2 g every 8 hours |
|
| 30−60 |
Dose adjustment according to creatinine clearance |
|||
| 500 mg every 24 hours |
1 g every 24 hours |
2 g every 24 hours |
2 g every 12 hours |
|
| 11−29 |
500 mg every 24 hours |
500 mg every 24 hours |
1 g every 24 hours |
2 g every 24 hours |
| ≤11 |
250 mg every 24 hours |
250 mg every 24 hours |
500 mg every 24 hours |
1 g every 24 hours |
| Continuous ambulatory peritoneal dialysis |
500 mg every 48 hours |
1 g every 48 hours |
2 g every 48 hours |
2 g every 48 hours |
| Hemodialysis* |
1 g every 24 hours |
1 g once daily on the first day, then 500 mg every 24 hours (and for treatment of febrile neutropenia, the maintenance dose is 1 g every 24 hours) |
||
* Cefepime should be administered after completion of a hemodialysis session, daily at the same time.
During a 3-hour hemodialysis session, approximately 68% of the administered dose of the drug is eliminated from the body. Therefore, after each dialysis session, a supplemental dose equal to the initial dose should be administered.
For continuous ambulatory peritoneal dialysis (CAPD), the drug can be used at the initial standard recommended doses of 500 mg, 1 g, or 2 g, depending on the severity of infection, with a dosing interval of 48 hours.
Creatinine clearance (CCr) can be determined from serum creatinine concentration using the formula below:
Males:
Body weight (kg) × (140 – age)
CCrmale, (mL/min) = ———————————————
72 × serum creatinine (mg/dL)
CCrfemale, (mL/min) = (CCrmale) × 0.85
Children aged 2 months and older. The maximum dose for children should not exceed the recommended adult dose. The usual recommended dose for children weighing less than 40 kg in cases of complicated or uncomplicated urinary tract infections (including pyelonephritis), uncomplicated skin infections, pneumonia, and empirical treatment of febrile neutropenia is 50 mg/kg every 12 hours (for patients with febrile neutropenia – every 8 hours).
Children weighing less than 40 kg receiving treatment with this drug should be closely monitored.
Studies in children with impaired renal function have not been conducted. However, since the pharmacokinetics of cefepime are similar in adults and children, dose reduction or increased dosing intervals proportional to those recommended for adults are advised for children (see Tables 4 and 5).
Calculation of creatinine clearance in children:
0.55 × height (cm)
Creatinine clearance (mL/min/1.73 m²) = ———————————————
serum creatinine (mg/dL)
or
0.52 × height (cm)
Creatinine clearance (mL/min/1.73 m²) = ——————————————— – 3.6
serum creatinine (mg/dL)
The usual duration of treatment is 7–10 days; severe infections may require longer treatment.
For children with body weight of 40 kg or more, cefepime dosing should be the same as for adults.
Administration of the drug.
Cefepime-O can be administered intravenously or by deep intramuscular injection into large muscles (e.g., the upper outer quadrant of the gluteal muscle).
Intravenous administration. The intravenous route is used for patients with severe or life-threatening infections.
For intravenous administration, Cefepime-O should be dissolved in sterile water for injection, 5% dextrose solution for injection, or 0.9% sodium chloride solution, as specified in Table 6. It should be administered slowly over 3–5 minutes. For intravenous infusions, the drug should be infused over approximately 30 minutes.
Intramuscular administration. Cefepime-O can be reconstituted with sterile water for injection, 0.9% sodium chloride solution, 5% dextrose solution for injection, bacteriostatic water for injection containing parabens or benzyl alcohol, or 0.5% or 1% lidocaine hydrochloride solution, at the concentrations specified in Table 6:
| Route of administration |
Volume of diluent (ml) |
Approximate volume of resulting solution (ml) |
Approximate concentration of cefepime (mg/ml) |
| Intravenous administration 1 g/vial |
10 |
11.4 |
90 |
| Intramuscular administration 1 g/vial |
3 |
4.4 |
230 |
As with other parenterally administered medicinal products, prepared solutions of the drug should be inspected for the presence of particulate matter prior to administration.
Cefepime should be reconstituted immediately before use and used as soon as possible. Unused solution should be discarded.
Appropriate microbiological investigations should be carried out to identify the causative microorganism(s) and to determine susceptibility to cefepime. However, Cefepime-O may be used as monotherapy prior to identification of the causative microorganism due to its broad spectrum of antibacterial activity against both gram-positive and gram-negative microorganisms. In patients at risk of mixed aerobic/anaerobic (including Bacteroides fragilis) infections, treatment with Cefepime-O in combination with agents active against anaerobes may be initiated before identification of the causative pathogen.
Children.
The drug is indicated for use in children aged 2 months and older.
There are insufficient clinical data to recommend the use of cefepime in children under 2 months of age, as well as for the treatment of severe infections in children when Haemophilus influenzae type b is suspected or confirmed.
In patients in whom the causative agent of meningitis has been isolated from a distant infection site or in whom meningitis is not confirmed, alternative medicinal products with proven clinical efficacy should be used.
Overdose.
Symptoms. In case of significant overdose, adverse effects are intensified, especially in patients with impaired renal function. Symptoms of overdose include encephalopathy accompanied by hallucinations, impaired consciousness, stupor, coma, myoclonus, seizures, and neuromuscular excitability.
Treatment. Administration of the drug should be discontinued and symptomatic therapy initiated. Hemodialysis accelerates elimination of cefepime from the body; peritoneal dialysis is poorly effective. Severe immediate-type allergic reactions require administration of adrenaline and other forms of intensive therapy.
Adverse Reactions
-
Infections and infestations: vaginal infections, oral and/or vaginal candidiasis.
-
Blood and lymphatic system disorders: eosinophilia, thrombocytopenia, leukopenia, neutropenia, aplastic anemia, hemolytic anemia, agranulocytosis, pancytopenia.
-
Gastrointestinal disorders: nausea, vomiting, altered taste sensation, constipation, abdominal pain, dyspepsia, diarrhea, colitis (including pseudomembranous colitis).
-
Central nervous system disorders: headache, dizziness, insomnia, paresthesia, restlessness, seizures, encephalopathy (loss of consciousness, hallucinations, coma, stupor), altered mental status, myoclonic seizures, epileptiform seizures.
-
Cardiovascular disorders: chest pain, vasodilation, tachycardia, hemorrhage.
-
Immune system disorders: hypersensitivity reactions, including anaphylaxis, anaphylactic shock, angioneurotic edema.
-
Skin and subcutaneous tissue disorders: pruritus, rash, urticaria, toxic epidermal necrolysis, Stevens-Johnson syndrome, erythema multiforme.
-
Hepatobiliary disorders: hepatitis, hepatic dysfunction, including cholestasis.
-
General disorders and administration site conditions: fever; phlebitis and inflammation with intravenous administration; pain or inflammation at the injection site with intramuscular administration.
-
Laboratory test abnormalities: increased levels of alanine aminotransferase, aspartate aminotransferase, alkaline phosphatase, total bilirubin; prolonged prothrombin time or partial thromboplastin time; positive Coombs test without hemolysis; decreased phosphorus levels, hypocalcemia (more common in elderly patients). There are no reports on clinical consequences of changes in calcium or phosphorus levels. Transient increases in blood urea nitrogen and/or serum creatinine levels; anemia, eosinophilia, agranulocytosis, transient thrombocytopenia, elevated calcium levels. Transient leukopenia and neutropenia, decreased hematocrit have also been observed.
-
Renal and urinary disorders: genital pruritus, renal dysfunction, toxic nephropathy, renal failure.
-
Respiratory system disorders: cough, sore throat, dyspnea.
-
Other: asthenia, peripheral edema, back pain, sweating.
Shelf life. 2 years.
Storage conditions. Store in the original packaging in a protected from light place at a temperature not exceeding 25°C.
Keep out of reach of children.
The prepared solution for intramuscular and intravenous injections should be used immediately. Any unused solution should be discarded.
Incompatibilities. Do not mix in the same container with other medicinal products, except those specified in the section "Administration and dosage".
Packaging.
1 g in a glass vial, 1 vial in a cardboard box.
Prescription status.
Prescription only.
Manufacturer.
Nitin Lifesciences Ltd. / Nitin Lifesciences Ltd.
Manufacturer's address and place of business.
Village-Rampur Road, Paonta Sahib, District Sirmour, Himachal Pradesh, India
Marketing Authorization Holder.
Ochoa Impex / Ochoa Impex.
Address of the Marketing Authorization Holder and/or its representative.
E-360, Greater Kailash part-II, New Delhi-110048, India.
E-360, Greater Kailash part-II, New Delhi-110048, India.
Similar drugs
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026