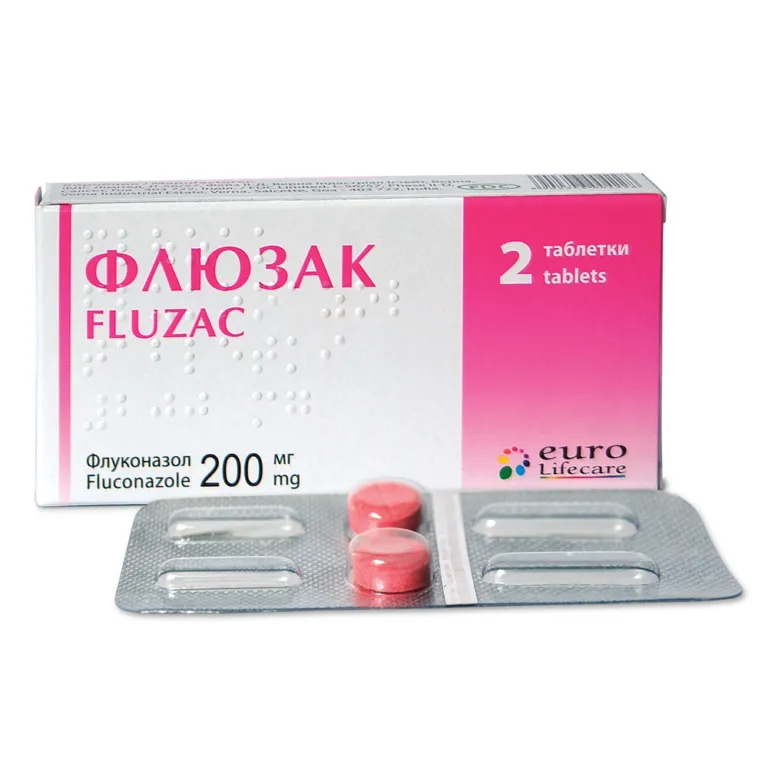
FLUZAC
UkraineThe drug is prescribed for the treatment of various fungal infections in adults and children, including invasive candidiasis, mucosal candidiasis (oropharynx, esophagus), vaginal candidiasis, candidal balanitis, dermatomycoses (foot fungus, skin fungus, etc.), onychomycosis (nail fungus), as well as cryptococcal meningitis and coccidioidomycosis. It is also used to prevent infection recurrences in high-risk patients.
Frequently asked questions
How should Fluzac be taken correctly?
Tablets should be swallowed whole; food intake does not affect absorption. The dosage depends on the type and severity of the infection. For example, for acute vaginal candidiasis or balanitis, 150 mg is usually prescribed as a single dose. For other diseases, a doctor may prescribe a loading dose on the first day, followed by a maintenance dose taken daily or weekly.
Who should not take this drug?
Contraindicated in case of hypersensitivity to fluconazole or other azole compounds. Additionally, the drug must not be taken simultaneously with certain other medications that affect heart rhythm (e.g., cisapride, astemizole, erythromycin, pimozide, quinidine) due to the risk of serious heart rhythm disturbances.
What side effects can Fluzac cause?
The most common side effects are headache, abdominal pain, diarrhea, nausea, vomiting, and skin rash. An increase in liver enzyme levels is also possible. Less commonly, seizures, dizziness, taste disturbances, as well as serious skin reactions or liver dysfunction may occur. If jaundice or severe weakness occurs, you should immediately stop taking the drug and consult a doctor.
Can the drug be taken during pregnancy or breastfeeding?
Use of the drug is not recommended during pregnancy, except in cases of extreme necessity, as there is a risk to the fetus. Breastfeeding is possible after a single dose of a standard dose (150 mg), but breastfeeding is not recommended with multiple applications or the use of high doses.
How does the drug interact with other medicines?
Fluzac can significantly affect the concentration of many other drugs in the blood, increasing their effect or the risk of toxicity. In particular, it interacts with anticoagulants (e.g., warfarin), certain blood pressure medications, anticonvulsants, and immunosuppressants. When taken concurrently with these agents, dosage adjustment and careful monitoring of the patient's condition may be required.
Instructions for use
Table of contents
INSTRUCTIONS FOR MEDICAL USE OF THE MEDICINAL PRODUCT FLUZAC (FLUZAC)
Composition:
Active ingredient: fluconazole;
1 tablet contains fluconazole 150 mg;
Excipients: calcium hydrogen phosphate, maize starch, colloidal anhydrous silicon dioxide, magnesium stearate, sodium starch glycolate (type A), sodium lauryl sulfate, methylparahydroxybenzoate (E 218), propylparahydroxybenzoate (E 216), talc, Ponceau 4R colorant (E 124).
Pharmaceutical form. Tablets.
Main physicochemical characteristics: flat, round pink tablets with speckles, bevelled edges, a break line on one side and smooth on the other.
Pharmacotherapeutic group. Antifungal agents for systemic use. Triazole derivatives. ATC code J02A C01.
Pharmacological properties.
Pharmacodynamics.
Mechanism of action.
Fluconazole is an antifungal agent of the triazole class. Its primary mechanism of action is the inhibition of fungal 14-alpha-lanosterol-demethylation, mediated by cytochrome P450, an essential step in the biosynthesis of fungal ergosterol. Accumulation of 14-alpha-methyl-sterols correlates with subsequent loss of ergosterol from the fungal cell membrane and may account for the antifungal activity of fluconazole. Fluconazole is more selective for fungal cytochrome P450 enzymes than for various cytochrome P450 enzyme systems in mammals.
Administration of fluconazole at a dose of 50 mg once daily for 28 days does not affect plasma testosterone levels in men or endogenous steroid levels in women of reproductive age. Fluconazole at doses of 200–400 mg daily does not produce clinically significant effects on endogenous steroid levels or on the response to adrenocorticotropic hormone (ACTH) stimulation in healthy male volunteers.
Studies on interaction with antipyrine have demonstrated that single or repeated administration of 50 mg fluconazole does not affect antipyrine metabolism.
In vitro susceptibility.
Fluconazole demonstrates in vitro antifungal activity against the most common Candida species (including C. albicans, C. parapsilosis, C. tropicalis). C. glabrata shows reduced susceptibility to fluconazole, while C. krusei and C. auris are resistant to fluconazole. Minimal inhibitory concentrations and epidemiological cut-off values (ECOFF) according to EUCAST for fluconazole against C. guilliermondii are higher than those for C. albicans.
Fluconazole also demonstrates in vitro activity against Cryptococcus neoformans and Cryptococcus gattii, as well as against endemic mould fungi Blastomyces dermatitidis, Coccidioides immitis, Histoplasma capsulatum, and Paracoccidioides brasiliensis.
Relationship between pharmacokinetic and pharmacodynamic properties.
According to animal studies, there is a correlation between minimal inhibitory concentration (MIC) and efficacy against experimental models of mycoses caused by Candida species. Clinical studies have shown a linear relationship between AUC and fluconazole dose (approximately 1:1). There is also a direct, but suboptimal, relationship between AUC or dose and positive clinical response in the treatment of oral candidiasis and, to a lesser extent, candidemia. Similarly, treatment of infections caused by strains exhibiting high minimal inhibitory concentrations to fluconazole is less effective.
Mechanism of resistance.
Candida species exhibit multiple mechanisms of resistance to azole antifungal agents. Fluconazole shows high minimal inhibitory concentrations against fungal strains possessing one or more resistance mechanisms, which negatively affects in vivo efficacy and clinical outcomes. In normally susceptible Candida species, the most common resistance mechanism involves the azole target enzymes responsible for ergosterol biosynthesis. Resistance may be due to mutations, increased enzyme production, drug efflux mechanisms, or development of compensatory pathways.
Superinfections caused by non-albicans Candida species, which often show reduced susceptibility (C. glabrata) or are resistant (e.g., C. krusei, C. auris) to fluconazole, have been reported. Alternative antifungal agents should be used for the treatment of such infections. Resistance mechanisms are not yet fully understood in some intrinsically resistant species (C. krusei) or newly emerging species (C. auris).
EUCAST (European Committee on Antimicrobial Susceptibility Testing) breakpoints.
Based on pharmacokinetic/pharmacodynamic data, in vitro susceptibility, and clinical response, EUCAST has established breakpoints for fluconazole against Candida species (EUCAST explanatory document for fluconazole (2020) – version 3; European Committee on Antimicrobial Susceptibility Testing, Antifungal agents, Breakpoint tables for interpretation of MICs, version 10.0, effective 04.02.2020). These have been categorized into non-species-specific breakpoints, primarily determined based on pharmacokinetic/pharmacodynamic data and not dependent on species-specific distribution of minimal inhibitory concentrations, and species-specific breakpoints, associated with infections commonly seen in humans. These breakpoints are listed below.
| Antifungal agent |
Species-specific breakpoints, S ≤ / R > in mg/l |
Non-species-related breakpoints,a S ≤ / R > in mg/l |
|||||
| Candida albicans |
Candida |
Candida glabrata |
Candida krusei |
Candida parapsilosis |
Candida tropicalis |
||
| Fluconazole |
2/4 |
2/4 |
0.001*/16 |
-- |
2/4 |
2/4 |
2/4 |
S = sensitive;
R = resistant;
a – non-species-related breakpoints, which were primarily determined based on pharmacokinetic/pharmacodynamic information and do not depend on species-specific minimal inhibitory concentration distributions. These were studied only in microorganisms lacking a specific breakpoint;
-- susceptibility testing not recommended, as this species is not a target for therapy;
* All C. glabrata isolates fall into the I category. MICs against C. glabrata should be considered resistant when they exceed 16 mg/L. The susceptible category (≤ 0.001 mg/L) is used solely to prevent misclassification of I strains as S strains. I – susceptible with increased exposure: a microorganism is categorized as "susceptible with increased exposure" when there is a high probability of therapeutic success due to increased drug exposure achieved by adjusting the dosing regimen or higher drug concentrations at the site of infection.
Pharmacokinetics
The pharmacokinetic properties of fluconazole are similar following intravenous and oral administration.
Absorption.
Fluconazole is well absorbed after oral administration, and plasma drug levels and systemic bioavailability exceed 90% of those achieved after intravenous administration. Concomitant food intake does not affect drug absorption following oral administration. Peak plasma concentrations are reached within 0.5–1.5 hours after dosing on an empty stomach. Plasma drug concentrations are proportional to dose. Steady-state 90% concentration is achieved by day 4–5 of once-daily treatment. A steady-state concentration of 90% is reached by day 2 when a loading dose twice the standard daily dose is administered on the first day.
Distribution.
The volume of distribution approximates total body water. Plasma protein binding is low (11–12%).
Fluconazole penetrates well into all studied body fluids. Drug levels in saliva and sputum are similar to plasma concentrations. In patients with fungal meningitis, fluconazole concentrations in cerebrospinal fluid reach 80% of plasma levels.
High fluconazole concentrations in the skin, exceeding serum levels, are achieved in the stratum corneum, epidermis, dermis, and sweat. Fluconazole accumulates in the stratum corneum. With a dose of 50 mg once daily, fluconazole concentration after 12 days of treatment was 73 µg/g, and 7 days after treatment completion, the concentration remained at 5.8 µg/g. With a dose of 150 mg once weekly, the concentration on day 7 of treatment was 23.4 µg/g; 7 days after the next dose, the concentration remained at 7.1 µg/g.
Fluconazole concentrations in nails after 4 months of 150 mg once weekly were 4.05 µg/g in healthy volunteers and 1.8 µg/g in patients with nail disease; fluconazole was detectable in nail samples up to 6 months after therapy completion.
Biotransformation.
Fluconazole is minimally metabolized. After administration of radiolabeled dose, only 11% of fluconazole is excreted in urine in altered form. Fluconazole is a moderate inhibitor of CYP2C9 and CYP3A4 isoenzymes and a potent inhibitor of the CYP2C19 isoenzyme.
Elimination.
The plasma elimination half-life of fluconazole is approximately 30 hours. The majority of the drug is excreted by the kidneys, with 80% of the administered dose recovered unchanged in urine. Fluconazole clearance is proportional to creatinine clearance. No circulating metabolites have been identified.
The prolonged plasma elimination half-life allows single-dose administration for vaginal candidiasis and once-weekly dosing for other indications.
Renal impairment.
In patients with severe renal impairment (glomerular filtration rate < 20 mL/min), the elimination half-life increases from 30 hours to 98 hours. Therefore, this patient group requires dose reduction of fluconazole. Fluconazole is removed by hemodialysis and, to a lesser extent, by intraperitoneal dialysis. A 3-hour hemodialysis session reduces plasma fluconazole levels by approximately 50%.
Lactation.
Fluconazole concentrations in plasma and breast milk were evaluated over 48 hours after a single 150 mg dose in a pharmacokinetic study involving ten lactating women who temporarily or permanently discontinued breastfeeding their infants. In breast milk, fluconazole was detected at an average concentration of approximately 98% of that in maternal plasma. The mean peak concentration in breast milk was 2.61 mg/L, reached 5.2 hours after dosing. The daily dose of fluconazole received by the infant via breast milk (assuming average milk intake of 150 mL/kg/day), calculated based on the mean peak milk concentration of 0.39 mg/kg/day, amounts to approximately 40% of the dose recommended for neonates (age < 2 weeks) or 13% of the dose recommended for infants for treatment of mucosal candidiasis.
Children.
Pharmacokinetic data were evaluated in 113 children across five studies: two single-dose studies, two multiple-dose studies, and one study in premature neonates.
After administration of 2–8 mg/kg fluconazole to children aged 9 months to 15 years, AUC was approximately 38 µg*h/mL per 1 mg/kg dose. After multiple dosing, the mean plasma elimination half-life ranged between 15 and 18 hours; the volume of distribution was 880 mL/kg. A longer plasma elimination half-life of approximately 24 hours was observed after single-dose administration. This is comparable to the plasma elimination half-life of fluconazole after a single 3 mg/kg intravenous dose in children aged 11 days to 11 months. The volume of distribution in this age group was approximately 950 mL/kg.
Experience with fluconazole use in neonates is limited to pharmacokinetic studies in 12 premature infants with a gestational age of approximately 28 weeks. The mean age at first dose was 24 hours (range 9–36 hours); mean birth weight was 900 g (range 750–1100 g). The study protocol was completed in 7 patients. Up to 5 intravenous doses of fluconazole 6 mg/kg were administered every 72 hours. The mean elimination half-life was 74 hours (44–185) on day 1, decreasing to 53 hours (30–131) on day 7 and to 47 hours (27–68) on day 13. The area under the curve (µg*h/mL) was 271 (173–385) on day 1, increased to 490 (292–734) on day 7, then decreased to 360 (167–566) on day 13. The volume of distribution (mL/kg) was 1183 (1070–1470) on day 1, increased to 1184 (510–2130) on day 7 and to 1328 (1040–1680) on day 13.
Elderly patients.
A pharmacokinetic study was conducted in 22 patients (aged ≥65 years) who received 50 mg oral fluconazole. Ten patients were concurrently receiving diuretics. Cmax was 1.54 µg/mL, reached within 1.3 hours after fluconazole administration. Mean AUC was 76.4±20.3 µg*h/mL. Mean elimination half-life was 46.2 hours. These pharmacokinetic parameters are higher than those observed in younger healthy volunteers. Concomitant diuretic use had no significant effect on Cmax or AUC. Similarly, creatinine clearance (74 mL/min), percentage of unchanged fluconazole excreted in urine (0–24 hours, 22%), and renal clearance of fluconazole (0.124 mL/min/kg) in this age group were lower than in younger volunteers. Therefore, pharmacokinetic changes in elderly patients are clearly dependent on renal function parameters.
Clinical characteristics.
Indications.
Fluconazole medication is indicated for the treatment of the following fungal infections in adults (see section "Pharmacodynamics"):
- Acute vaginal candidiasis, when topical therapy is not appropriate.
- Candidal balanitis, when topical therapy is not appropriate.
Antifungal therapy with fluconazole may be initiated before obtaining results of culture and other laboratory tests; however, after receiving test results, antifungal therapy should be adjusted accordingly.
Official recommendations regarding appropriate use of antifungal agents should be taken into account.
Contraindications.
- Hypersensitivity to fluconazole, other azole compounds, or to any of the excipients of the drug.
- Concomitant use of fluconazole and terfenadine in patients receiving repeated doses of fluconazole at 400 mg/day or higher (based on results of multiple-dose interaction studies).
- Concomitant use of fluconazole and other medicinal products that prolong the QT interval and are metabolized by the CYP3A4 enzyme (e.g., cisapride, astemizole, pimozide, quinidine, and erythromycin) (see sections "Special precautions for use" and "Interaction with other medicinal products and other forms of interaction").
Interaction with other medicinal products and other types of interactions.
Concomitant use of fluconazole and the following medicinal products is contraindicated.
Cisapride. Cases of cardiac adverse reactions, including paroxysmal ventricular tachycardia of the torsades de pointes type, have been reported in patients receiving fluconazole and cisapride concomitantly. A controlled study demonstrated that concomitant administration of 200 mg fluconazole once daily and 20 mg cisapride four times daily resulted in a significant increase in plasma levels of cisapride and QT interval prolongation. Concomitant use of fluconazole and cisapride is contraindicated (see section "Contraindications").
Terfenadine. Due to cases of severe cardiac arrhythmias caused by QTc interval prolongation in patients receiving azole antifungal agents concomitantly with terfenadine, interaction studies between these agents were conducted. In one study, administration of fluconazole at a dose of 200 mg daily did not result in QTc interval prolongation. Another study using fluconazole at doses of 400 mg and 800 mg daily demonstrated that fluconazole at doses of 400 mg daily or higher significantly increased plasma levels of terfenadine when administered concomitantly. Concomitant use of fluconazole at doses of 400 mg or higher with terfenadine is contraindicated (see section "Contraindications"). When fluconazole is used at doses below 400 mg daily concomitantly with terfenadine, careful patient monitoring is required.
Astemizole. Concomitant use of fluconazole and astemizole may reduce astemizole clearance. The resulting increase in astemizole plasma concentration may lead to QT interval prolongation and, rarely, to paroxysmal ventricular tachycardia of the torsades de pointes type. Concomitant use of fluconazole and astemizole is contraindicated (see section "Contraindications").
Pimozide and quinidine. Concomitant use of fluconazole and pimozide or quinidine may lead to inhibition of pimozide or quinidine metabolism, although relevant in vitro and in vivo studies have not been conducted. Increased plasma concentrations of pimozide or quinidine may cause QT interval prolongation and, rarely, paroxysmal ventricular tachycardia of the torsades de pointes type. Concomitant use of fluconazole and pimozide or quinidine is contraindicated (see section "Contraindications").
Erythromycin. Concomitant use of erythromycin and fluconazole may increase the risk of cardiotoxicity (QT interval prolongation, paroxysmal ventricular tachycardia of the torsades de pointes type) and, consequently, sudden cardiac death. The use of this combination is contraindicated.
Concomitant use of fluconazole and the following medicinal products is not recommended.
Halofantrine. Fluconazole may increase halofantrine plasma concentrations by inhibiting CYP3A4. Concomitant use of these medicinal products may increase the risk of cardiotoxicity (QT interval prolongation, paroxysmal ventricular tachycardia of the torsades de pointes type) and, consequently, sudden cardiac death. The use of this combination should be avoided (see section "Special precautions for use").
Concomitant use of fluconazole and the following medicinal products requires caution.
Amiodarone. Concomitant use of fluconazole with amiodarone may lead to QT interval prolongation. Fluconazole should be used with caution together with amiodarone, especially when high-dose fluconazole (800 mg) is prescribed.
Concomitant use of fluconazole and the following medicinal products requires caution and dose adjustment.
Effect of other medicinal products on fluconazole.
Interaction studies have demonstrated that oral administration of fluconazole taken simultaneously with food, cimetidine, antacids, or total body irradiation for bone marrow transplantation does not have a clinically significant effect on fluconazole absorption.
Rifampicin. Concomitant use of fluconazole and rifampicin led to a 25% decrease in AUC and a 20% reduction in the elimination half-life of fluconazole. Therefore, for patients receiving rifampicin, consideration should be given to increasing the dose of fluconazole.
Hydrochlorothiazide. In a pharmacokinetic interaction study, multiple concomitant administration of hydrochlorothiazide in healthy volunteers receiving fluconazole increased fluconazole plasma concentration by 40%. Such interaction parameters do not require changes in fluconazole dosing regimen for patients receiving diuretics concomitantly.
Effect of fluconazole on other medicinal products.
Fluconazole is a moderate inhibitor of cytochrome P450 (CYP) isoenzymes 2C9 and 3A4. Fluconazole is a potent inhibitor of isoenzyme CYP2C19. In addition to observed/documented interactions described below, there is a risk of increased plasma concentrations of other compounds metabolized by CYP2C9, CYP2C19, and CYP3A4 when administered concomitantly with fluconazole. Therefore, such combinations should be used with caution; careful monitoring of patients is necessary. The inhibitory effect of fluconazole on enzymes persists for 4–5 days after its administration due to its long elimination half-life (see section "Contraindications").
Abrocitinib. Fluconazole (inhibitor of CYP2C19, 2C9, 3A4) increased exposure to the active moiety of abrocitinib by 155%. When used concomitantly with fluconazole, the dose of abrocitinib should be adjusted according to the instructions for medical use of abrocitinib.
Alfentanil. When alfentanil at a dose of 20 mcg/kg and fluconazole at a dose of 400 mg were administered concomitantly to healthy volunteers, a twofold increase in AUC was observed, possibly due to inhibition of CYP3A4. Dose adjustment of alfentanil may be necessary.
Amitriptyline, nortriptyline. Fluconazole enhances the effect of amitriptyline and nortriptyline. Measurement of concentrations of 5-nortriptyline and/or S-amitriptyline is recommended at the beginning of combination therapy and after 1 week. If necessary, the dose of amitriptyline/nortriptyline should be adjusted.
Amphotericin B. Concomitant use of fluconazole and amphotericin B in immunocompetent and immunocompromised infected mice resulted in: a slight additive antifungal effect in systemic C. albicans infection, no interaction in intracranial Cryptococcus neoformans infection, and antagonism between the two drugs in systemic Aspergillus fumigatus infection. The clinical significance of these study results is unknown.
Anticoagulants. As with other azole antifungal agents, cases of bleeding (hematomas, epistaxis, gastrointestinal bleeding, hematuria, and melena) associated with prolonged prothrombin time have been reported during concomitant use of fluconazole and warfarin. A twofold increase in prothrombin time was observed during concomitant use of fluconazole and warfarin, likely due to inhibition of warfarin metabolism via CYP2C9. Prothrombin time should be closely monitored in patients receiving coumarin anticoagulants or indandiones concomitantly. Dose adjustment of the anticoagulant may be necessary.
Short-acting benzodiazepines, e.g., midazolam, triazolam. Administration of fluconazole after oral administration of midazolam led to a significant increase in midazolam concentration and enhanced psychomotor effects. Concomitant use of fluconazole at a dose of 200 mg and midazolam at a dose of 7.5 mg orally resulted in a 3.7-fold and 2.2-fold increase in AUC and elimination half-life, respectively. Administration of fluconazole at a dose of 200 mg/day and 0.25 mg triazolam orally resulted in a 4.4-fold and 2.3-fold increase in AUC and elimination half-life of triazolam, respectively. Potentiation and prolongation of triazolam effects were observed during concomitant use of fluconazole and triazolam.
If a patient undergoing fluconazole therapy needs to be prescribed benzodiazepines concomitantly, the dose of the latter should be reduced and appropriate patient monitoring should be established.
Carbamazepine. Fluconazole inhibits carbamazepine metabolism and increases serum carbamazepine levels by 30%. There is a risk of carbamazepine toxicity. Dose adjustment of carbamazepine may be necessary depending on its concentration and effect.
Calcium channel blockers. Some calcium antagonists (nifedipine, isradipine, amlodipine, and felodipine) are metabolized by the CYP3A4 enzyme. Fluconazole may potentially increase systemic exposure to calcium channel blockers. Close monitoring for adverse reactions is recommended.
Celecoxib. When fluconazole (200 mg daily) and celecoxib (200 mg) were used concomitantly, Cmax and AUC of celecoxib increased by 68% and 134%, respectively. When celecoxib and fluconazole are used concomitantly, a halving of the celecoxib dose may be necessary.
Cyclophosphamide. Concomitant use of cyclophosphamide and fluconazole leads to increased serum bilirubin and creatinine levels. These drugs may be used concomitantly, considering the risk of increased serum bilirubin and creatinine concentrations.
Fentanyl. A fatal case of fentanyl intoxication due to a possible interaction between fentanyl and fluconazole has been reported. In addition, a study involving healthy volunteers demonstrated that fluconazole significantly slowed fentanyl elimination. Increased fentanyl concentration may lead to respiratory depression; therefore, careful monitoring of the patient is required. Dose adjustment of fentanyl may be necessary.
HMG-CoA reductase inhibitors. Concomitant use of fluconazole and HMG-CoA reductase inhibitors metabolized by CYP3A4 (atorvastatin and simvastatin), or HMG-CoA reductase inhibitors metabolized by CYP2C9 (fluvastatin (reduced hepatic metabolism of statin)), increases the risk of myopathy and rhabdomyolysis (dose-dependent). If concomitant use of these drugs is necessary, careful monitoring of the patient for symptoms of myopathy and rhabdomyolysis and monitoring of creatine kinase levels should be performed. If a significant increase in creatine kinase levels occurs, or if myopathy/rhabdomyolysis is diagnosed or suspected, HMG-CoA reductase inhibitors should be discontinued. Dose reduction of HMG-CoA reductase inhibitors may be necessary, as indicated in the instructions for medical use of statins.
Ibrutinib. Moderate CYP3A4 inhibitors, such as fluconazole, increase plasma concentrations of ibrutinib and may increase the risk of toxicity. If avoiding the combination is not possible, the dose of ibrutinib should be reduced to 280 mg once daily to continue inhibitor use, and continuous clinical monitoring should be ensured.
Ivacaftor (as monotherapy or in combination with drugs of the same therapeutic class). Concomitant use of ivacaftor, a cystic fibrosis transmembrane conductance regulator (CFTR) modulator, increased exposure to ivacaftor by 3 times and exposure to hydroxymethylivacaftor (M1) by 1.9 times. Dose reduction of ivacaftor (as monotherapy or in combination) is necessary, as specified in the medical use instructions for ivacaftor (as monotherapy or in combination).
Olaparib. Moderate CYP3A4 inhibitors, such as fluconazole, increase plasma concentrations of olaparib; their concomitant use is not recommended. If such a combination cannot be avoided, olaparib intake should be limited to 200 mg twice daily.
Immunosuppressants (e.g., cyclosporine, everolimus, sirolimus, and tacrolimus).
Cyclosporine. Fluconazole significantly increases cyclosporine concentration and AUC. When fluconazole at a dose of 200 mg/day and cyclosporine at a dose of 2.7 mg/kg/day were used concomitantly, an 1.8-fold increase in cyclosporine AUC was observed. These drugs may be used concomitantly provided cyclosporine dose is reduced depending on its concentration.
Everolimus. Although in vitro and in vivo studies have not been conducted, it is known that fluconazole may increase everolimus serum concentration by inhibiting CYP3A4.
Sirolimus. Fluconazole increases sirolimus plasma concentration, likely by inhibiting sirolimus metabolism by the CYP3A4 enzyme and P-glycoprotein. These drugs may be used concomitantly provided sirolimus dose is adjusted depending on concentration and drug effects.
Tacrolimus. Fluconazole may increase tacrolimus serum concentrations up to 5 times with oral administration due to inhibition of tacrolimus metabolism by the CYP3A4 enzyme in the intestine. No significant changes in pharmacokinetics were observed with intravenous administration of tacrolimus. Elevated tacrolimus levels are associated with nephrotoxicity. The oral dose of tacrolimus should be reduced depending on tacrolimus concentration.
Losartan. Fluconazole inhibits the metabolism of losartan to its active metabolite (E-31 74), which accounts for most of the angiotensin II receptor antagonism during losartan use. Continuous monitoring of blood pressure in patients is recommended.
Lurasidone. Moderate CYP3A4 inhibitors, such as fluconazole, may increase plasma concentrations of lurasidone. If concomitant use cannot be avoided, the dose of lurasidone should be reduced as specified in the medical use instructions for lurasidone.
Methadone. Fluconazole may increase methadone serum concentration. Dose adjustment of methadone may be necessary when methadone and fluconazole are used concomitantly.
Nonsteroidal anti-inflammatory drugs (NSAIDs). When used concomitantly with fluconazole, Cmax and AUC of flurbiprofen increased by 23% and 81%, respectively, compared to values when flurbiprofen was used alone. Similarly, when fluconazole was used concomitantly with racemic ibuprofen (400 mg), Cmax and AUC of the pharmacologically active isomer S-(+)-ibuprofen increased by 15% and 82%, respectively, compared to values when only racemic ibuprofen was used.
Fluconazole potentially increases systemic exposure to other NSAIDs metabolized by CYP2C9 (e.g., naproxen, lornoxicam, meloxicam, diclofenac). Periodic monitoring for adverse reactions and toxic effects associated with NSAIDs is recommended. Dose adjustment of NSAIDs may be required.
Phenytoin. Fluconazole inhibits hepatic metabolism of phenytoin. Multiple concomitant administration of 200 mg fluconazole and 250 mg phenytoin intravenously leads to a 75% increase in phenytoin AUC24 and a 128% increase in Cmin. Monitoring of phenytoin serum concentration should be performed when these drugs are used concomitantly to avoid phenytoin toxicity.
Prednisone. A case has been reported where a patient after liver transplantation developed acute adrenal insufficiency on the background of prednisone use, which occurred after discontinuation of a three-month course of fluconazole therapy. Discontinuation of fluconazole likely led to increased CYP3A4 activity, resulting in accelerated metabolism of prednisone. Patients who have been receiving fluconazole and prednisone concomitantly for a prolonged period should be closely monitored to prevent adrenal insufficiency after discontinuation of fluconazole.
Rifabutin. Fluconazole increases rifabutin serum concentration, leading to an increase in rifabutin AUC by up to 80%. Cases of uveitis have been reported during concomitant use of fluconazole and rifabutin. Symptoms of rifabutin toxicity should be considered when using this combination of drugs.
Saquinavir. Fluconazole increases AUC and Cmax of saquinavir by approximately 50% and 55%, respectively, due to inhibition of saquinavir metabolism in the liver by the CYP3A4 enzyme and inhibition of P-glycoprotein. Interactions between fluconazole and saquinavir/ritonavir have not been studied, so they may be more pronounced. Dose adjustment of saquinavir may be necessary.
Sulfonylurea derivatives. When used concomitantly, fluconazole prolongs the elimination half-life of oral sulfonylurea derivatives (chlorpropamide, glyburide, glipizide, and tolbutamide) in healthy volunteers. Frequent blood glucose monitoring and appropriate dose reduction of sulfonylurea derivatives are recommended when used concomitantly with fluconazole.
Theophylline. In a placebo-controlled interaction study, administration of fluconazole at 200 mg for 14 days led to an 18% decrease in the average plasma clearance of theophylline. Patients receiving high doses of theophylline or those at increased risk of theophylline toxicity for other reasons should be monitored for signs of theophylline toxicity. Therapy should be modified if signs of toxicity appear.
Tofacitinib. The effect of tofacitinib increases when used concomitantly with medicinal products that cause moderate inhibition of CYP3A4 and potent inhibition of CYP2C19 (e.g., fluconazole). Therefore, it is recommended to reduce the dose of tofacitinib to 5 mg once daily when used in combination with these drugs.
Tolvaptan. Exposure to tolvaptan significantly increased (200% AUC, 80% Cmax) when tolvaptan, a CYP3A4 substrate, was administered concomitantly with fluconazole, a moderate CYP3A4 inhibitor, thereby significantly increasing the risk of adverse reactions, including marked diuresis, dehydration, and acute kidney injury. When co-administered, the dose of tolvaptan should be reduced according to the instructions in the medical use instructions, and the patient should be regularly checked for any adverse reactions associated with tolvaptan.
Vinca alkaloids. Fluconazole, likely through inhibition of CYP3A4, may increase plasma concentrations of vinca alkaloids (e.g., vincristine and vinblastine), leading to neurotoxic effects.
Vitamin A. A case has been reported where a patient receiving concomitant all-trans retinoic acid (acid form of vitamin A) and fluconazole experienced central nervous system (CNS) adverse reactions in the form of pseudotumor cerebri; this effect resolved after discontinuation of fluconazole. These medicinal products may be used concomitantly, but the risk of CNS adverse reactions should be kept in mind.
Voriconazole (inhibitor of CYP2C9, CYP2C19, and CYP3A4). Concomitant oral administration of voriconazole (400 mg every 12 hours on day 1, then 200 mg every 12 hours for 2.5 days) and fluconazole (400 mg on day 1, then 200 mg every 24 hours for 4 days) led to an average increase in Cmax and AUC of voriconazole by 57% (90% CI: 20%, 107%) and 79% (90% CI: 40%, 128%), respectively. It is unknown whether reducing the dose and/or frequency of voriconazole or fluconazole eliminates this effect. When voriconazole is used after fluconazole, monitoring for adverse effects associated with voriconazole should be performed.
Zidovudine. Fluconazole increases Cmax and AUC of zidovudine by 84% and 74%, respectively, due to a decrease in zidovudine clearance by approximately 45% after oral administration. The elimination half-life of zidovudine was also prolonged by approximately 128% after administration of the fluconazole and zidovudine combination. Patients receiving this combination of medicinal products should be monitored for adverse reactions associated with zidovudine use. Consideration may be given to reducing the dose of zidovudine.
Azithromycin. In an open-label, randomized, three-way crossover study involving 18 healthy volunteers, the effect of azithromycin and fluconazole on each other's pharmacokinetics was evaluated after single oral doses of 1200 mg and 800 mg, respectively. No significant pharmacokinetic interactions were observed.
Oral contraceptives. Two pharmacokinetic studies of multiple-dose fluconazole and combined oral contraceptives were conducted. When fluconazole was administered at a dose of 50 mg, no effect on hormone levels was observed, whereas administration of fluconazole at a dose of 200 mg daily resulted in a 40% increase in AUC of ethinylestradiol and a 24% increase in levonorgestrel. This indicates that multiple administration of fluconazole at these doses is unlikely to affect the efficacy of combined oral contraceptives.
Special precautions for use.
Dermatophytosis. According to studies on fluconazole for the treatment of dermatophytosis in children, fluconazole is not superior to griseofulvin in efficacy, and the overall efficacy rate is less than 20%. Therefore, Fluzaс should not be used for the treatment of dermatophytosis.
Cryptococcosis. There is insufficient evidence of efficacy of fluconazole in the treatment of cryptococcosis at other sites (e.g., pulmonary cryptococcosis and cutaneous cryptococcosis); therefore, dosage recommendations for the treatment of such infections are not available.
Deep endemic mycoses. There is insufficient evidence of efficacy of fluconazole in the treatment of other forms of endemic mycoses, such as paracoccidioidomycosis, histoplasmosis, and cutaneous-lymphatic sporotrichosis; therefore, dosage recommendations for the treatment of such infections are not available.
Renal system. The drug should be used with caution in patients with impaired renal function (see section "Dosage and administration").
Adrenal insufficiency. Ketoconazole is known to cause adrenal insufficiency, and this may also apply to fluconazole, although it is rarely observed. Adrenal insufficiency associated with concomitant treatment with prednisone is described in the section "Interaction with other medicinal products and other forms of interaction. Effect of fluconazole on other medicinal products."
Hepatobiliary system. The drug should be used with caution in patients with impaired liver function. Rare cases of severe hepatotoxicity, including fatal outcomes, have been associated with the use of fluconazole, primarily in patients with serious underlying diseases. When hepatotoxicity has been associated with fluconazole use, no clear dependence on the total daily dose, duration of therapy, sex, or age of the patient has been observed. Hepatotoxicity caused by fluconazole is usually reversible, and symptoms resolve after discontinuation of therapy.
Patients who develop abnormalities in liver function tests during fluconazole treatment should be closely monitored for the development of more severe liver damage.
Patients should be informed about symptoms that may indicate serious liver effects (marked asthenia, anorexia, persistent nausea, vomiting, and jaundice). In such cases, fluconazole treatment should be discontinued immediately and medical advice sought.
Cardiovascular system. Some azoles, including fluconazole, have been associated with QT interval prolongation on electrocardiogram. Fluconazole prolongs the QT interval by inhibiting the rectifier potassium channel (Ikr). QT interval prolongation caused by other medicinal products (e.g., amiodarone) may be potentiated due to inhibition of the CYP3A4 enzyme of cytochrome P450. Very rare cases of QT interval prolongation and torsades de pointes ventricular tachycardia have been reported with fluconazole use. These reports involved patients with severe underlying diseases and multiple risk factors, such as structural heart disease, electrolyte disturbances, and concomitant use of other medicinal products affecting the QT interval. Patients with hypokalemia and progressive heart failure have an increased risk of life-threatening ventricular arrhythmias and torsades de pointes.
Fluzaс should be used with caution in patients at risk of developing arrhythmias. Concomitant use with medicinal products that prolong the QTc interval and are metabolized by the CYP3A4 enzyme of cytochrome P450 is contraindicated (see sections "Contraindications" and "Interaction with other medicinal products and other forms of interaction").
Halofantrine. Halofantrine is a substrate of the CYP3A4 enzyme and prolongs the QTc interval when used at recommended therapeutic doses. Concomitant use of halofantrine and fluconazole is not recommended (see section "Interaction with other medicinal products and other forms of interaction").
Cutaneous reactions. Rare cases of exfoliative skin reactions such as Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported during fluconazole use. Drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) has also been reported. Patients with AIDS are more prone to develop severe skin reactions when using many medicinal products. If a patient with superficial fungal infection develops a rash that may be related to fluconazole use, further treatment with the drug should be discontinued. If a patient with invasive/systemic fungal infection develops a skin rash, careful monitoring is required, and fluconazole treatment should be discontinued in case of bullous eruptions or development of erythema multiforme.
Hypersensitivity. In rare cases, anaphylactic reactions have been reported (see section "Contraindications").
Cytochrome P450. Fluconazole is a moderate inhibitor of CYP2C9 and CYP3A4 enzymes. Fluconazole is also an inhibitor of the CYP2C19 enzyme. Patients receiving concomitant Fluzaс and medicinal products with a narrow therapeutic window that are metabolized by CYP2C9, CYP2C19, and CYP3A4 should be closely monitored (see section "Interaction with other medicinal products and other forms of interaction").
Terfenadine. Careful monitoring of the patient is required when terfenadine and fluconazole are used concomitantly at a dose of less than 400 mg per day (see sections "Contraindications" and "Interaction with other medicinal products and other forms of interaction").
Candidiasis. Studies have demonstrated an increasing prevalence of infections caused by Candida species other than C. albicans. These are often intrinsically resistant (e.g., C. krusei and C. auris) or show reduced susceptibility to fluconazole (C. glabrata). Such infections may require alternative antifungal therapy after failed treatment. Therefore, physicians prescribing this agent are advised to consider the prevalence of resistance of various Candida species to fluconazole.
Use during pregnancy or breastfeeding.
Women of reproductive potential
Before initiating treatment, the patient should be informed about the potential risk to the fetus.
After a single dose, a washout period of approximately 1 week (corresponding to 5–6 half-lives) should be observed before attempting pregnancy (see section "Pharmacokinetics").
For prolonged treatment courses, women of reproductive potential should consider using contraception throughout the treatment period and for 1 week after the last dose.
Pregnancy
Observational studies indicate an increased risk of spontaneous abortion in women who received fluconazole during the first and/or second trimester compared to women who did not take fluconazole or received topical azoles during the same period.
Data from several thousand women who received a cumulative dose of ≤150 mg of fluconazole during the first trimester of pregnancy do not indicate an increased overall risk of congenital malformations. In one large observational cohort study, oral fluconazole use during the first trimester was associated with a small increased risk of musculoskeletal malformations, corresponding to approximately 1 additional case per 1000 women receiving a cumulative therapeutic dose ≤450 mg compared to women who received topical azoles, and approximately 4 additional cases per 1000 women receiving cumulative doses >450 mg. The relative risk was 1.29 (95% CI 1.05–1.58) for a 150 mg dose of fluconazole and 1.98 (95% CI 1.23–3.17) for doses >450 mg.
Available epidemiological studies on the risk of cardiac malformations following fluconazole use during pregnancy provide conflicting results. However, a meta-analysis of 5 observational studies involving several thousand pregnant women who received fluconazole during the first trimester showed a 1.8- to 2-fold increased risk of congenital heart defects in infants compared to infants of mothers who did not use fluconazole and/or used topical azoles.
Congenital malformations have been reported in infants whose mothers received high doses (400–800 mg/day) of fluconazole during pregnancy for more than 3 months for the treatment of coccidioidomycosis. Among the congenital malformations observed in these children were brachycephaly, ear dysplasia, enlarged anterior fontanelle, femoral bowing, and radiohumeral synostosis. A causal relationship between fluconazole use and congenital malformations has not been established.
Fluconazole at usual doses and short-term fluconazole treatment should not be used during pregnancy except when clearly needed.
High-dose fluconazole and/or prolonged fluconazole treatment should not be used during pregnancy except for the treatment of life-threatening infections.
Breastfeeding
Fluconazole passes into breast milk and reaches concentrations similar to those in plasma (see section "Pharmacokinetics"). Breastfeeding may continue after a single dose of fluconazole at the usual dose of 150 mg.
Breastfeeding is not recommended with repeated administration of fluconazole or with high-dose fluconazole. The benefit of breastfeeding for the child's development and health, the mother's clinical need for fluconazole, and any potential adverse effects of fluconazole or the mother's underlying condition on the breastfed infant should be carefully evaluated.
Fertility
Fluconazole did not affect fertility in male and female rats.
Ability to affect reaction speed when driving or operating machinery.
No studies on the effect of Fluzaс on the ability to drive or operate machinery have been conducted.
Patients should be informed about the possibility of developing dizziness or seizures during Fluzaс treatment. If such symptoms occur, driving or operating machinery is not recommended.
Method of Administration and Dosage
Tablets should be swallowed whole. The administration of the drug is not affected by food intake.
Adults.
The drug is administered orally at a single dose of 150 mg.
Elderly patients.
In the absence of signs of renal impairment, this patient category should receive the standard adult dose.
Renal impairment.
Fluconazole is primarily excreted unchanged in the urine. Dose adjustment is not required in this patient group when the drug is administered as a single dose.
Hepatic impairment.
Fluconazole should be used with caution in patients with hepatic dysfunction, as there is insufficient data on the use of fluconazole in this patient population.
Children.
The efficacy and safety of the drug for the treatment of genital candidiasis in children have not been established, despite comprehensive data on the use of fluconazole in pediatric patients. If there is an urgent need to administer the drug to adolescents (aged 12 to 17 years), the standard adult doses should be used.
Overdose.
Cases of fluconazole overdose have been reported, with concomitant hallucinations and paranoid behavior.
In case of overdose, symptomatic and supportive therapy should be administered, and gastric lavage should be performed if necessary.
Fluconazole is substantially excreted in the urine; forced diuresis may accelerate drug elimination. A 3-hour hemodialysis session reduces plasma fluconazole levels by approximately 50%.
Adverse Reactions.
Summary of safety profile
Drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) has been reported with fluconazole treatment (see section "Special precautions for use").
The most commonly reported adverse reactions were: headache, abdominal pain, diarrhea, nausea, vomiting, rash, increased alanine aminotransferase (ALT) levels, increased aspartate aminotransferase (AST) levels, increased alkaline phosphatase levels.
The following classification is used to assess the frequency of adverse reactions: very common (≥ 1/10), common (≥ 1/100 to < 1/10), uncommon (≥ 1/1000 to < 1/100), rare (≥ 1/10,000 to < 1/1000), very rare (< 1/10,000), frequency not known (cannot be estimated from available data).
Blood and lymphatic system disorders.
Uncommon: anemia.
Rare: agranulocytosis, leukopenia, neutropenia, thrombocytopenia.
Immune system disorders.
Rare: anaphylaxis.
Metabolism and nutrition disorders.
Uncommon: decreased appetite.
Rare: hypertriglyceridemia, hypercholesterolemia, hypokalemia.
Psychiatric disorders.
Uncommon: insomnia, somnolence.
Nervous system disorders.
Common: headache.
Uncommon: convulsions, dizziness, paresthesia, taste disturbance.
Rare: tremor.
Ear and labyrinth disorders.
Uncommon: vertigo.
Cardiac disorders.
Rare: paroxysmal ventricular tachycardia of the torsades de pointes type, QT interval prolongation (see section "Special precautions for use").
Gastrointestinal disorders.
Common: abdominal pain, diarrhea, nausea, vomiting.
Uncommon: constipation, dyspepsia, flatulence, dry mouth.
Hepatobiliary disorders.
Common: increased alanine aminotransferase (ALT) levels, increased aspartate aminotransferase (AST) levels, increased alkaline phosphatase levels (see section "Special precautions for use").
Uncommon: cholestasis, jaundice, increased bilirubin levels (see section "Special precautions for use").
Rare: hepatic failure, hepatocellular necrosis, hepatitis, hepatocellular injury (see section "Special precautions for use").
Skin and subcutaneous tissue disorders.
Common: rash (see section "Special precautions for use").
Uncommon: pruritus, drug eruption (including fixed drug eruption), urticaria, increased sweating (see section "Special precautions for use").
Rare: toxic epidermal necrolysis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, exfoliative dermatitis, angioneurotic edema, facial swelling, alopecia (see section "Special precautions for use").
Not known: drug reaction with eosinophilia and systemic symptoms (DRESS syndrome).
Musculoskeletal and connective tissue disorders.
Uncommon: myalgia.
General disorders and administration site conditions.
Uncommon: increased fatigue, malaise, asthenia, fever.
The presence of the dye Ponceau 4R (E 124) may cause allergic reactions, and methylparahydroxybenzoate (E 218) and propylparahydroxybenzoate (E 216) may cause allergic reactions (possibly delayed-type).
Children. The frequency and nature of adverse reactions and laboratory abnormalities observed in clinical trials involving children are comparable to those in adults.
Reporting of suspected adverse reactions.
Reporting suspected adverse reactions after marketing authorization is important. It allows continued monitoring of the benefit-risk balance of the medicinal product. Healthcare professionals are encouraged to report any suspected adverse reactions in accordance with local regulatory requirements.
Shelf life. 3 years.
Storage conditions. Store at temperatures not exceeding 25 °C. Keep out of reach of children.
Packaging. 1 tablet in a blister; 1 blister in a cardboard box.
Prescription status. Over-the-counter.
Manufacturer.
FDC Limited.
Manufacturer's address and location of operations.
L-56/57, Phase II-D, Verna Industrial Estate, Verna, Salcette, Goa – 403 722, India.
INSTRUCTIONS
for medical use of the medicinal product
FLUZAC
(FLUZAC)
Composition:
Active substance: fluconazole;
1 tablet contains 50 mg, 150 mg, or 200 mg of fluconazole;
Excipients: calcium hydrogen phosphate, maize starch, colloidal anhydrous silicon dioxide, magnesium stearate, sodium starch glycolate (type A), sodium lauryl sulfate, methylparahydroxybenzoate (E 218), propylparahydroxybenzoate (E 216), talc, Ponceau 4R color (E 124).
Pharmaceutical form. Tablets.
Main physical and chemical properties: flat, round pink tablets with speckles, beveled edges, a score line on one side, and smooth on the other.
Pharmacotherapeutic group. Antifungal agents for systemic use. Triazole derivatives. ATC code J02A C01.
Pharmacological Properties
Pharmacodynamics
Mechanism of Action
Fluconazole is an antifungal agent of the triazole class. Its primary mechanism of action is the inhibition of fungal 14-alpha-lanosterol-demethylation, mediated by cytochrome P450, an essential step in the biosynthesis of fungal ergosterol. Accumulation of 14-alpha-methyl sterols correlates with subsequent depletion of ergosterol in the fungal cell membrane and is considered responsible for the antifungal activity of fluconazole. Fluconazole is more selective for fungal cytochrome P450 enzymes than for various cytochrome P450 enzyme systems in mammals.
Administration of fluconazole at a dose of 50 mg once daily for 28 days does not affect plasma testosterone levels in men or endogenous steroid levels in women of reproductive age. Fluconazole at doses of 200–400 mg daily does not have clinically significant effects on endogenous steroid levels or on the response to adrenocorticotropic hormone (ACTH) stimulation in healthy male volunteers.
A study on antipyrine interaction demonstrated that single or repeated administration of 50 mg fluconazole does not affect antipyrine metabolism.
In vitro susceptibility
Fluconazole demonstrates in vitro antifungal activity against the most commonly encountered Candida species (including C. albicans, C. parapsilosis, and C. tropicalis). C. glabrata shows reduced susceptibility to fluconazole, while C. krusei and C. auris are resistant to fluconazole. The minimal inhibitory concentrations (MICs) and epidemiological cutoff values (ECOFF) for C. guilliermondii according to EUCAST are higher than those for C. albicans.
Fluconazole also demonstrates in vitro activity against Cryptococcus neoformans and Cryptococcus gattii, as well as against endemic mould fungi such as Blastomyces dermatitidis, Coccidioides immitis, Histoplasma capsulatum, and Paracoccidioides brasiliensis.
Pharmacokinetic/Pharmacodynamic Relationships
According to animal studies, there is a correlation between the minimal inhibitory concentration (MIC) and efficacy against experimental models of mycoses caused by Candida species. Clinical studies have shown a linear relationship between AUC and fluconazole dose (approximately 1:1). There is also a direct, although not fully sufficient, correlation between AUC or dose and positive clinical response in the treatment of oral candidiasis and, to a lesser extent, candidemia. Similarly, treatment outcomes for infections caused by strains exhibiting high MIC values for fluconazole are less favorable.
Mechanisms of Resistance
Candida species exhibit multiple mechanisms of resistance to azole antifungal agents. Fluconazole shows high minimal inhibitory concentrations against fungal strains possessing one or more resistance mechanisms, which negatively impacts its in vivo and clinical efficacy. In normally susceptible Candida species, the most common resistance mechanism involves the target enzymes of azoles responsible for ergosterol biosynthesis. Resistance may result from mutations, increased enzyme production, drug efflux mechanisms, or development of compensatory pathways.
Superinfections caused by Candida spp. other than C. albicans, often exhibiting reduced susceptibility (e.g., C. glabrata) or resistance (e.g., C. krusei, C. auris) to fluconazole, have been reported. Alternative antifungal agents should be used for the treatment of such infections. Resistance mechanisms in some intrinsically resistant species (e.g., C. krusei) or emerging species (e.g., C. auris) are not yet fully understood.
EUCAST (European Committee on Antimicrobial Susceptibility Testing) Breakpoints
Based on pharmacokinetic/pharmacodynamic data, in vitro susceptibility, and clinical response, EUCAST has established breakpoints for fluconazole against Candida species (EUCAST Fluconazole Guidance Document (2020) – version 3; European Committee on Antimicrobial Susceptibility Testing, Antifungal agents, Breakpoint tables for interpretation of MICs, version 10.0, effective 04.02.2020). These breakpoints are categorized into non-species-specific breakpoints, primarily determined based on pharmacokinetic/pharmacodynamic data and not dependent on species-specific MIC distributions, and species-specific breakpoints, associated with species most commonly causing human infections. These breakpoints are listed below.
| Antifungal agent |
Species-specific breakpoints, S ≤ / R > in mg/L S ≤ / R > in mg/L |
Non-species-related breakpoints,a S ≤ / R > in mg/L |
|||||
| Candida albicans |
Candida |
Candida glabrata |
Candida krusei |
Candida parapsilosis |
Candida tropicalis |
||
| Fluconazole |
2/4 |
2/4 |
0.001*/16 |
-- |
2/4 |
2/4 |
2/4 |
S = susceptible;
R = resistant;
a – breakpoints not associated with a specific species, which are primarily determined based on pharmacokinetic/pharmacodynamic data and do not depend on species-specific minimal inhibitory concentration distributions. These were studied only in microorganisms lacking a species-specific breakpoint;
-- susceptibility testing not recommended, as this species is not a target for drug therapy;
* All C. glabrata isolates fall within category I. MICs against C. glabrata should be considered resistant when they exceed 16 mg/L. The susceptible category (≤ 0.001 mg/L) is used solely to prevent misclassification of I strains as S strains. I – susceptible with increased exposure: a microorganism is categorized as "susceptible with increased exposure" when there is a high likelihood of therapeutic success due to increased drug exposure achieved by adjusting the dosing regimen or increasing drug concentration at the site of infection.
Pharmacokinetics.
The pharmacokinetic properties of fluconazole are similar following intravenous and oral administration.
Absorption.
Fluconazole is well absorbed after oral administration, and plasma drug levels and systemic bioavailability exceed 90% of those achieved with intravenous administration. Concomitant food intake does not affect absorption when the drug is administered orally. Peak plasma concentration is reached within 0.5–1.5 hours after dosing on an empty stomach. Plasma drug concentration is proportional to dose. Steady-state 90% concentration is achieved by day 4–5 of repeated once-daily dosing. A steady-state concentration of 90% is reached by day 2 when a loading dose twice the standard daily dose is administered on the first day.
Distribution.
The volume of distribution is approximately equal to total body water. Plasma protein binding is low (11–12%).
Fluconazole penetrates well into all studied body fluids. Drug levels in saliva and sputum are similar to plasma concentrations. In patients with fungal meningitis, fluconazole concentrations in cerebrospinal fluid reach 80% of plasma levels.
High fluconazole concentrations exceeding serum levels are achieved in the skin, particularly in the stratum corneum, epidermis, dermis, and sweat. Fluconazole accumulates in the stratum corneum. With a 50 mg once-daily dose, fluconazole concentration after 12 days of treatment was 73 µg/g, and 7 days after treatment completion, the concentration remained at 5.8 µg/g. With a 150 mg once-weekly dose, fluconazole concentration on day 7 of treatment was 23.4 µg/g; 7 days after the next dose, the concentration remained at 7.1 µg/g.
Fluconazole concentration in nails after 4 months of 150 mg once-weekly dosing was 4.05 µg/g in healthy volunteers and 1.8 µg/g in patients with nail disease; fluconazole was detectable in nail samples up to 6 months after therapy completion.
Metabolism.
Fluconazole is minimally metabolized. After administration of radiolabeled dose, only 11% of fluconazole is excreted in urine as metabolites. Fluconazole is a moderate inhibitor of CYP2C9 and CYP3A4 isoenzymes and a potent inhibitor of the CYP2C19 isoenzyme.
Elimination.
The plasma half-life of fluconazole is approximately 30 hours. The majority of the drug is excreted by the kidneys, with 80% of the administered dose recovered unchanged in urine. Fluconazole clearance is proportional to creatinine clearance. No circulating metabolites have been identified.
The prolonged plasma half-life allows for single-dose administration in vaginal candidiasis and once-weekly dosing for other indications.
Renal impairment.
In patients with severe renal impairment (glomerular filtration rate < 20 mL/min), the elimination half-life increases from 30 hours to 98 hours. Therefore, fluconazole dosage must be reduced in these patients. Fluconazole is removed by hemodialysis and, to a lesser extent, by peritoneal dialysis. A 3-hour hemodialysis session reduces plasma fluconazole levels by approximately 50%.
Lactation.
Fluconazole concentrations in plasma and breast milk were evaluated over 48 hours after a single 150 mg dose in a pharmacokinetic study involving ten lactating women who temporarily or permanently discontinued breastfeeding. In breast milk, fluconazole was detected at an average concentration of approximately 98% of that in maternal plasma. The mean peak concentration in breast milk was 2.61 mg/L, reached 5.2 hours after dosing. The daily fluconazole dose received by the infant via breast milk (assuming average milk intake of 150 mL/kg/day), calculated based on mean peak milk concentration, was 0.39 mg/kg/day, which corresponds to approximately 40% of the dose recommended for neonates (age < 2 weeks) or 13% of the dose recommended for infants for treatment of mucosal candidiasis.
Pediatric population.
Pharmacokinetic data were evaluated in 113 children across five studies: two single-dose studies, two multiple-dose studies, and one study in premature neonates.
After administration of 2–8 mg/kg fluconazole to children aged 9 months to 15 years, AUC was approximately 38 µg*h/mL per 1 mg/kg dose. After multiple dosing, the mean plasma elimination half-life ranged between 15 and 18 hours, and volume of distribution was 880 mL/kg. A longer plasma half-life of approximately 24 hours was observed after single-dose administration. This is comparable to the plasma half-life of fluconazole after a single 3 mg/kg intravenous dose in children aged 11 days to 11 months. The volume of distribution in this age group was approximately 950 mL/kg.
Experience with fluconazole in neonates is limited to pharmacokinetic studies in 12 premature infants with a gestational age of approximately 28 weeks. The mean age at first dose was 24 hours (range 9–36 hours); mean birth weight was 900 g (range 750–1100 g). The study protocol was completed in 7 patients. Up to 5 intravenous doses of fluconazole 6 mg/kg were administered every 72 hours. The mean elimination half-life was 74 hours (range 44–185) on day 1, decreasing to 53 hours (range 30–131) on day 7 and to 47 hours (range 27–68) on day 13. The area under the curve (µg*h/mL) was 271 (range 173–385) on day 1, increased to 490 (range 292–734) on day 7, then decreased to 360 (range 167–566) on day 13. The volume of distribution (mL/kg) was 1183 (range 1070–1470) on day 1, increased to 1184 (range 510–2130) on day 7, and to 1328 (range 1040–1680) on day 13.
Elderly patients.
A pharmacokinetic study was conducted in 22 patients (aged 65 years and older) who received 50 mg oral fluconazole. Ten patients were concurrently receiving diuretics. Cmax was 1.54 µg/mL, reached 1.3 hours after fluconazole administration. Mean AUC was 76.4 ± 20.3 µg*h/mL. Mean elimination half-life was 46.2 hours. These pharmacokinetic parameters are higher than those observed in younger healthy volunteers. Concomitant diuretic use had no significant effect on Cmax or AUC. Additionally, creatinine clearance (74 mL/min), percentage of unchanged fluconazole excreted in urine (0–24 hours, 22%), and renal clearance of fluconazole (0.124 mL/min/kg) in this patient group were lower than in younger volunteers. Therefore, pharmacokinetic changes in elderly patients are clearly dependent on renal function parameters.
Clinical characteristics.
Indications.
Treatment of fungal infections in adults (see section “Pharmacodynamics”), such as:
- cryptococcal meningitis (see section “Special precautions for use”);
- coccidioidomycosis (see section “Special precautions for use”);
- invasive candidiasis;
- mucosal candidiasis, including oropharyngeal candidiasis, esophageal candidiasis, candiduria, chronic cutaneous and mucosal candidiasis;
- chronic atrophic oral candidiasis (denture stomatitis), when oral hygiene or topical therapy is ineffective;
- vaginal candidiasis, acute or recurrent, when topical therapy is inappropriate;
- candidal balanitis, when topical therapy is not appropriate;
- dermatomycoses, including tinea pedis, cutaneous dermatophytosis, tinea cruris, pityriasis versicolor, and cutaneous candidal infections, when systemic therapy is indicated;
- dermatophytic onychomycosis, when the use of other medicinal products is not appropriate.
Prevention of the following conditions in adults:
- recurrence of cryptococcal meningitis in patients at high risk of developing it;
- recurrence of oropharyngeal or esophageal candidiasis in HIV-infected patients at high risk of developing it;
- reduction in the frequency of recurrent vaginal candidiasis (4 or more episodes per year);
- prophylaxis of candidal infections in patients with prolonged neutropenia (e.g., patients with hematological malignancies receiving chemotherapy or patients undergoing hematopoietic stem cell transplantation) (see section “Pharmacological properties. Pharmacodynamics”).
Children.
The tablet form of the medicinal product may be administered to this patient group only when children are able to swallow tablets safely, which is usually possible from the age of 5 years.
Fluconazole is used in children for the treatment of mucosal candidiasis (oropharyngeal candidiasis, esophageal candidiasis), invasive candidiasis, cryptococcal meningitis, and for prophylaxis of candidal infections in immunocompromised patients. The drug may be used as maintenance therapy to prevent recurrence of cryptococcal meningitis in children at high risk of developing it (see section “Special precautions for use”).
Treatment with Fluconazole may be initiated before the results of culture and other laboratory tests are available; however, after obtaining the results, antimicrobial therapy should be adjusted accordingly.
Contraindications.
- Hypersensitivity to fluconazole, other azole compounds, or to any of the excipients of the drug.
- Concomitant use of fluconazole and terfenadine in patients receiving fluconazole repeatedly at doses of 400 mg/day or higher (based on results of multiple-dose interaction studies).
- Concomitant use of fluconazole and other medicinal products that prolong the QT interval and are metabolized via the CYP3A4 enzyme (e.g., cisapride, astemizole, pimozide, quinidine, and erythromycin) (see sections “Special precautions for use” and “Interaction with other medicinal products and other forms of interaction”).
Interaction with other medicinal products and other forms of interaction.
Concomitant use of fluconazole and the following medicinal products is contraindicated.
Cisapride. Cases of cardiac adverse reactions, including paroxysmal ventricular tachycardia of the “torsade de pointes” type, have been reported in patients concurrently receiving fluconazole and cisapride. A controlled study demonstrated that concomitant administration of 200 mg fluconazole once daily and 20 mg cisapride four times daily significantly increased plasma levels of cisapride and prolonged the QT interval. Concomitant use of fluconazole and cisapride is contraindicated (see section “Contraindications”).
Terfenadine. Due to cases of severe cardiac arrhythmias caused by QTc interval prolongation in patients receiving azole antifungal agents concomitantly with terfenadine, interaction studies between these drugs were conducted. In one study, administration of fluconazole at a dose of 200 mg daily did not result in QTc prolongation. Another study using fluconazole at doses of 400 mg and 800 mg daily demonstrated that fluconazole at doses of 400 mg daily or higher significantly increased plasma levels of terfenadine when administered concomitantly. Concomitant use of fluconazole at doses of 400 mg or higher with terfenadine is contraindicated (see section “Contraindications”). When fluconazole is used at doses below 400 mg daily concomitantly with terfenadine, careful patient monitoring is required.
Astemizole. Concomitant use of fluconazole and astemizole may reduce the clearance of astemizole. This increase in plasma concentration of astemizole may lead to QT interval prolongation and, rarely, to paroxysmal ventricular tachycardia of the “torsade de pointes” type. Concomitant use of fluconazole and astemizole is contraindicated (see section “Contraindications”).
Pimozide and quinidine. Concomitant use of fluconazole and pimozide or quinidine may lead to inhibition of pimozide or quinidine metabolism, although appropriate in vitro and in vivo studies have not been conducted. Increased plasma concentrations of pimozide or quinidine may cause QT interval prolongation and, rarely, lead to the development of paroxysmal ventricular tachycardia of the “torsade de pointes” type. Concomitant use of fluconazole and pimozide or quinidine is contraindicated (see section “Contraindications”).
Erythromycin. Concomitant use of erythromycin and fluconazole may increase the risk of cardiotoxicity (QT interval prolongation, paroxysmal ventricular tachycardia of the “torsade de pointes” type) and, as a consequence, sudden cardiac death. The use of this combination is contraindicated (see section “Contraindications”).
Concomitant use of fluconazole and the following medicinal products is not recommended.
Halofantrine. Fluconazole may increase plasma concentrations of halofantrine by inhibiting CYP3A4. Concomitant use of these medicinal products may increase the risk of cardiotoxicity (QT interval prolongation, paroxysmal ventricular tachycardia of the “torsade de pointes” type) and, as a consequence, sudden cardiac death. The combination of these medicinal products should be avoided (see section “Special precautions for use”).
Concomitant use of fluconazole and the following medicinal products requires caution.
Amiodarone. Concomitant use of fluconazole and amiodarone may lead to QT interval prolongation. Fluconazole should be used with caution together with amiodarone, especially when high-dose fluconazole (800 mg) is prescribed.
Concomitant use of fluconazole and the following medicinal products requires caution and dose adjustment.
Effect of other medicinal products on fluconazole.
Interaction studies have demonstrated that oral administration of fluconazole concomitantly with food, cimetidine, antacids, or total body irradiation for bone marrow transplantation has no clinically significant effect on fluconazole absorption.
Rifampicin. Concomitant use of fluconazole and rifampicin resulted in a 25% decrease in AUC and a 20% shortening of the elimination half-life of fluconazole. Therefore, for patients receiving rifampicin, consideration should be given to increasing the dose of fluconazole.
Hydrochlorothiazide. In a pharmacokinetic interaction study, repeated multiple-dose administration of hydrochlorothiazide in healthy volunteers receiving fluconazole increased plasma concentrations of fluconazole by 40%. Such interaction parameters do not require changes in the dosing regimen of fluconazole for patients concurrently receiving diuretics.
Effect of fluconazole on other medicinal products.
Fluconazole is a moderate inhibitor of the CYP2C9 isoenzyme of cytochrome P450 (CYP) and a moderate inhibitor of CYP3A4. Fluconazole is a potent inhibitor of the CYP2C19 isoenzyme. In addition to observed/documentarily confirmed interactions described below, there is a risk of increased plasma concentrations of other compounds metabolized by CYP2C9, CYP2C19, and CYP3A4 when used concomitantly with fluconazole. Therefore, such combinations should be used with caution; careful monitoring of patients is necessary. The inhibitory effect of fluconazole on enzymes persists for 4–5 days after its administration due to its long elimination half-life (see section “Contraindications”).
Abrocitinib: fluconazole (inhibitor of CYP2C19, 2C9, 3A4) increased exposure to the active moiety of abrocitinib by 155%. When used concomitantly with fluconazole, the dose of abrocitinib should be adjusted according to the instructions for medical use of abrocitinib.
Alfentanil. In healthy volunteers receiving concomitant alfentanil at a dose of 20 µg/kg and fluconazole at a dose of 400 mg, a twofold increase in AUC was observed, possibly due to inhibition of CYP3A4. Dose adjustment of alfentanil may be necessary.
Amitriptyline, nortriptyline. Fluconazole enhances the effect of amitriptyline and nortriptyline. Measurement of concentrations of 5-nortriptyline and/or S-amitriptyline is recommended at the beginning of combination therapy and after 1 week. If necessary, the dose of amitriptyline/nortriptyline should be adjusted.
Amphotericin B. Concomitant use of fluconazole and amphotericin B in immunocompetent and immunocompromised infected mice yielded the following results: a slight additive antifungal effect in systemic C. albicans infection, no interaction in intracranial Cryptococcus neoformans infection, and antagonism between the two drugs in systemic Aspergillus fumigatus infection. The clinical significance of these findings is unknown.
Anticoagulants. As with other azole antifungal agents, cases of bleeding (hematomas, epistaxis, gastrointestinal bleeding, hematuria, and melena) associated with prolonged prothrombin time have been reported with concomitant use of fluconazole and warfarin. A twofold increase in prothrombin time was observed with concomitant use of fluconazole and warfarin, likely due to inhibition of warfarin metabolism via CYP2C9. Prothrombin time should be carefully monitored in patients receiving coumarin anticoagulants or indanediones concomitantly. Dose adjustment of the anticoagulant may be necessary.
Benzodiazepines of short duration of action, e.g., midazolam, triazolam. Administration of fluconazole after oral administration of midazolam led to a significant increase in midazolam concentration and enhanced psychomotor effects. Concomitant use of fluconazole at a dose of 200 mg and midazolam at a dose of 7.5 mg orally resulted in a 3.7-fold and 2.2-fold increase in AUC and elimination half-life, respectively. Administration of fluconazole at a dose of 200 mg/day and 0.25 mg triazolam orally resulted in a 4.4-fold and 2.3-fold increase in AUC and elimination half-life of triazolam, respectively. Potentiation and prolongation of triazolam effects were observed with concomitant use of fluconazole and triazolam.
If a patient undergoing fluconazole therapy needs to be prescribed benzodiazepines concomitantly, the dose of the latter should be reduced and appropriate patient monitoring established.
Carbamazepine. Fluconazole inhibits carbamazepine metabolism and causes a 30% increase in serum carbamazepine levels. There is a risk of carbamazepine toxicity. Dose adjustment of carbamazepine may be necessary depending on its serum concentration and drug effects.
Calcium channel blockers. Some calcium antagonists (nifedipine, isradipine, amlodipine, and felodipine) are metabolized by the CYP3A4 enzyme. Fluconazole may potentially increase systemic exposure to calcium channel blockers. Careful monitoring for adverse reactions is recommended.
Celecoxib. With concomitant use of fluconazole (200 mg daily) and celecoxib (200 mg), Cmax and AUC of celecoxib increased by 68% and 134%, respectively. With concomitant use of celecoxib and fluconazole, a halving of the celecoxib dose may be necessary.
Cyclophosphamide. Concomitant use of cyclophosphamide and fluconazole leads to increased serum levels of bilirubin and creatinine. These drugs may be used concomitantly, considering the risk of increased serum bilirubin and creatinine concentrations.
Fentanyl. A fatal case of fentanyl intoxication due to a possible interaction between fentanyl and fluconazole has been reported. In addition, a study involving healthy volunteers demonstrated that fluconazole significantly slowed fentanyl elimination. Increased fentanyl concentration may lead to respiratory depression; therefore, careful patient monitoring is required. Dose adjustment of fentanyl may be necessary.
HMG-CoA reductase inhibitors. Concomitant use of fluconazole and HMG-CoA reductase inhibitors metabolized by CYP3A4 (atorvastatin and simvastatin), or HMG-CoA reductase inhibitors metabolized by CYP2C9 (fluvastatin [reduced hepatic metabolism of the statin]), increases the risk of myopathy and rhabdomyolysis (dose-dependent). If concomitant use of these drugs is necessary, careful monitoring for symptoms of myopathy and rhabdomyolysis and monitoring of creatine kinase levels should be performed. If a significant increase in creatine kinase levels is observed, or if myopathy/rhabdomyolysis is diagnosed or suspected, HMG-CoA reductase inhibitors should be discontinued. Dose reduction of HMG-CoA reductase inhibitors may be necessary, as indicated in the instructions for medical use of statins.
Ibrutinib. Moderate CYP3A4 inhibitors, such as fluconazole, increase plasma concentrations of ibrutinib and may increase the risk of toxicity. If combination therapy cannot be avoided, the dose of ibrutinib should be reduced to 280 mg once daily to continue inhibitor therapy, with continuous clinical monitoring.
Ivacaftor (as monotherapy or in combination with drugs of the same therapeutic class). Concomitant use of ivacaftor, a cystic fibrosis transmembrane conductance regulator (CFTR) modulator, increased exposure to ivacaftor by 3-fold and exposure to hydroxymethylivacaftor (M1) by 1.9-fold. Dose reduction of ivacaftor (as monotherapy or in combination) is required, as specified in the instructions for medical use of ivacaftor (as monotherapy or in combination).
Olaparib. Moderate CYP3A4 inhibitors, such as fluconazole, increase plasma concentrations of olaparib; their concomitant use is not recommended. If such a combination cannot be avoided, olaparib intake should be limited to 200 mg twice daily.
Immunosuppressants (e.g., cyclosporine, everolimus, sirolimus, and tacrolimus).
Cyclosporine. Fluconazole significantly increases the concentration and AUC of cyclosporine. With concomitant use of fluconazole at a dose of 200 mg/day and cyclosporine at a dose of 2.7 mg/kg/day, an 1.8-fold increase in AUC of cyclosporine was observed. These drugs may be used concomitantly provided the cyclosporine dose is reduced depending on its concentration.
Everolimus. Although in vitro and in vivo studies have not been conducted, it is known that fluconazole may increase serum concentrations of everolimus by inhibiting CYP3A4.
Sirolimus. Fluconazole increases plasma concentrations of sirolimus, likely by inhibiting sirolimus metabolism by the CYP3A4 enzyme and P-glycoprotein. These drugs may be used concomitantly provided the sirolimus dose is adjusted depending on its concentration and drug effects.
Tacrolimus. Fluconazole may increase serum concentrations of tacrolimus up to 5-fold with oral administration due to inhibition of tacrolimus metabolism by the CYP3A4 enzyme in the intestine. No significant changes in pharmacokinetics were observed with intravenous administration of tacrolimus. Elevated tacrolimus levels are associated with nephrotoxicity. The oral dose of tacrolimus should be reduced depending on tacrolimus concentration.
Losartan. Fluconazole inhibits the metabolism of losartan to its active metabolite (E-3174), which accounts for most of the angiotensin II receptor antagonism during losartan use. Continuous monitoring of blood pressure in patients is recommended.
Lurasidone: moderate CYP3A4 inhibitors, such as fluconazole, may increase plasma concentrations of lurasidone. If concomitant use cannot be avoided, the dose of lurasidone should be reduced as specified in the instructions for medical use of lurasidone.
Methadone. Fluconazole may increase serum concentrations of methadone. Dose adjustment of methadone may be necessary with concomitant use of methadone and fluconazole.
Nonsteroidal anti-inflammatory drugs (NSAIDs). With concomitant use of fluconazole, Cmax and AUC of flurbiprofen increased by 23% and 81%, respectively, compared to values with flurbiprofen alone. Similarly, with concomitant use of fluconazole and racemic ibuprofen (400 mg), Cmax and AUC of the pharmacologically active isomer S-(+)-ibuprofen increased by 15% and 82%, respectively, compared to values with racemic ibuprofen alone.
Fluconazole may potentially increase systemic exposure to other NSAIDs metabolized by CYP2C9 (e.g., naproxen, lornoxicam, meloxicam, diclofenac). Periodic monitoring for adverse reactions and toxic effects associated with NSAIDs is recommended. Dose adjustment of NSAIDs may be required.
Phenytoin. Fluconazole inhibits hepatic metabolism of phenytoin. Repeated multiple-dose administration of 200 mg fluconazole and 250 mg phenytoin intravenously increases AUC24 of phenytoin by 75% and Cmin by 128%. Monitoring of phenytoin serum concentration should be performed with concomitant use of these drugs to avoid phenytoin toxicity.
Prednisone. A case has been reported in which a patient after liver transplantation developed acute adrenal insufficiency while on prednisone, following discontinuation of a three-month course of fluconazole therapy. Discontinuation of fluconazole likely led to increased CYP3A4 activity, resulting in accelerated metabolism of prednisone. Patients receiving long-term concomitant fluconazole and prednisone should be carefully monitored to prevent adrenal insufficiency after discontinuation of fluconazole.
Rifabutin. Fluconazole increases serum concentrations of rifabutin, leading to an up to 80% increase in AUC of rifabutin. Cases of uveitis have been reported with concomitant use of fluconazole and rifabutin. Symptoms of rifabutin toxicity should be considered when using this combination of drugs.
Saquinavir. Fluconazole increases AUC and Cmax of saquinavir by approximately 50% and 55%, respectively, due to inhibition of hepatic saquinavir metabolism by the CYP3A4 enzyme and inhibition of P-glycoprotein. Interactions between fluconazole and saquinavir/ritonavir have not been studied and may be more pronounced. Dose adjustment of saquinavir may be necessary.
Sulfonylurea derivatives. With concomitant use, fluconazole prolongs the elimination half-life of oral sulfonylurea derivatives (chlorpropamide, glyburide, glipizide, and tolbutamide) in healthy volunteers. Frequent blood glucose monitoring and appropriate dose reduction of sulfonylurea derivatives are recommended when used concomitantly with fluconazole.
Theophylline. Administration of fluconazole at 200 mg for 14 days resulted in an 18% decrease in the average plasma clearance of theophylline. Patients receiving high-dose theophylline or those at increased risk of theophylline toxicity for other reasons should be monitored for signs of theophylline toxicity. Therapy should be modified if signs of toxicity appear.
Tofacitinib. The effect of tofacitinib increases with concomitant use of drugs causing moderate inhibition of CYP3A4 and potent inhibition of CYP2C19 (e.g., fluconazole). Therefore, it is recommended to reduce the dose of tofacitinib to 5 mg once daily when used in combination with these drugs.
Concomitant use of fluconazole and the following medicinal products requires caution and dose adjustment.
Tolvaptan. Exposure to tolvaptan significantly increased (200% AUC, 80% Cmax) when tolvaptan, a CYP3A4 substrate, was administered concomitantly with fluconazole, a moderate CYP3A4 inhibitor, thereby significantly increasing the risk of adverse reactions, including marked diuresis, dehydration, and acute kidney injury. In case of concomitant administration, the dose of tolvaptan should be reduced according to the instructions in the medical use instructions, and the patient should be regularly checked for any adverse reactions associated with tolvaptan.
Vinca alkaloids. Fluconazole, likely via inhibition of CYP3A4, may increase plasma concentrations of vinca alkaloids (e.g., vincristine and vinblastine), leading to neurotoxic effects.
Vitamin A. A case has been reported in which a patient receiving all-trans retinoic acid (the acid form of vitamin A) concomitantly with fluconazole experienced central nervous system (CNS) adverse reactions in the form of pseudotumor cerebri; this effect disappeared after discontinuation of fluconazole. These medicinal products may be used concomitantly, but the risk of CNS adverse reactions should be kept in mind.
Voriconazole (inhibitor of CYP2C9, CYP2C19, and CYP3A4). Concomitant oral administration of voriconazole (400 mg every 12 hours for 1 day, then 200 mg every 12 hours for 2.5 days) and fluconazole (400 mg on the first day, then 200 mg every 24 hours for 4 days) resulted in an average increase in Cmax and AUC of voriconazole by 57% (90% CI: 20%, 107%) and 79% (90% CI: 40%, 128%), respectively. It is unknown whether reducing the dose and/or frequency of voriconazole or fluconazole eliminates this effect. When voriconazole is administered after fluconazole, monitoring for adverse effects associated with voriconazole is recommended.
Zidovudine. Fluconazole increases Cmax and AUC of zidovudine by 84% and 74%, respectively, due to a decrease in zidovudine clearance by approximately 45% with oral administration. The elimination half-life of zidovudine was also prolonged by approximately 128% after administration of the fluconazole and zidovudine combination. Patients receiving this combination of medicinal products should be monitored for adverse reactions associated with zidovudine use. Dose reduction of zidovudine may be considered.
Azithromycin. In an open-label, randomized, three-way crossover study involving 18 healthy volunteers, the effect of azithromycin and fluconazole on each other's pharmacokinetics was evaluated after single oral administration at doses of 1200 mg and 800 mg, respectively. No significant pharmacokinetic interactions were observed.
Oral contraceptives. Two multiple-dose pharmacokinetic studies of fluconazole and combined oral contraceptives were conducted. With fluconazole at a dose of 50 mg, no effect on hormone levels was observed, whereas with fluconazole at a dose of 200 mg daily, AUC of ethinylestradiol increased by 40% and levonorgestrel by 24%. This indicates that repeated administration of fluconazole at these doses is unlikely to affect the efficacy of combined oral contraceptives.
Special precautions for use.
Dermatophytosis. According to studies on fluconazole for the treatment of dermatophytosis in children, fluconazole does not exceed griseofulvin in efficacy, and the overall efficacy rate is less than 20%. Therefore, Fluzaс should not be used for the treatment of dermatophytosis.
Cryptococcosis. Evidence of fluconazole efficacy for the treatment of cryptococcosis at other sites (e.g., pulmonary cryptococcosis and cutaneous cryptococcosis) is insufficient; therefore, dosage recommendations for the treatment of such conditions are not available.
Deep endemic mycoses. Evidence of fluconazole efficacy for the treatment of other forms of endemic mycoses, such as paracoccidioidomycosis, histoplasmosis, and cutaneous-lymphatic sporotrichosis, is insufficient; therefore, dosage recommendations for the treatment of such conditions are not available.
Renal system. The drug should be used with caution in patients with impaired renal function (see section "Dosage and administration").
Adrenal insufficiency. Ketoconazole is known to cause adrenal insufficiency, and this may also apply to fluconazole, although it is rarely observed. Adrenal insufficiency associated with concomitant prednisone therapy is described in the section "Effect of fluconazole on other medicinal products".
Hepatobiliary system. The drug should be used with caution in patients with impaired liver function. The use of fluconazole has been associated with rare cases of severe hepatotoxicity, including fatal outcomes, primarily in patients with serious underlying diseases. When hepatotoxicity has been associated with fluconazole use, no clear dependence on the total daily dose, duration of therapy, sex, or age of the patient has been observed. Hepatotoxicity caused by fluconazole is usually reversible, and symptoms resolve after discontinuation of therapy.
Patients who develop abnormalities in liver function tests during fluconazole treatment should be closely monitored for the development of more severe liver injury.
Patients should be informed about symptoms that may indicate serious liver effects (marked asthenia, anorexia, persistent nausea, vomiting, and jaundice). In such cases, fluconazole should be discontinued immediately and medical advice should be sought.
Cardiovascular system. Some azoles, including fluconazole, are associated with QT interval prolongation on electrocardiogram. Fluconazole prolongs the QT interval by inhibiting the rectifying potassium channel (Ikr). QT interval prolongation caused by other medicinal products (e.g., amiodarone) may be potentiated due to inhibition of the CYP3A4 cytochrome P450 enzyme. Very rare cases of QT interval prolongation and torsades de pointes ventricular tachycardia have been reported with fluconazole use. These reports involved patients with severe underlying conditions and multiple risk factors, such as structural heart disease, electrolyte imbalances, and concomitant use of other drugs affecting the QT interval. Patients with hypokalemia and progressive heart failure have an increased risk of life-threatening ventricular arrhythmias and torsades de pointes.
Fluzaс should be used with caution in patients at risk of developing arrhythmias. Concomitant use with medicinal products that prolong the QTc interval and are metabolized by the CYP3A4 cytochrome P450 enzyme is contraindicated (see sections "Contraindications" and "Interaction with other medicinal products and other forms of interaction").
Halofantrine. Halofantrine is a substrate of the CYP3A4 enzyme and prolongs the QTc interval when used at recommended therapeutic doses. Concomitant use of halofantrine and fluconazole is not recommended.
Skin reactions. Rare cases of exfoliative skin reactions, such as Stevens-Johnson syndrome and toxic epidermal necrolysis, have been reported during fluconazole use. Drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) has also been reported. Patients with AIDS are more prone to developing severe skin reactions when using many medicinal products. If a patient with superficial fungal infection develops a rash that may be related to fluconazole use, further administration of the drug should be discontinued. If a patient with invasive/systemic fungal infection develops a skin rash, careful monitoring is required, and fluconazole treatment should be discontinued in case of bullous eruptions or erythema multiforme.
Hypersensitivity. Rare cases of anaphylactic reactions have been reported.
Cytochrome P450. Fluconazole is a potent inhibitor of the CYP2C9 enzyme and a moderate inhibitor of the CYP3A4 enzyme. Fluconazole is also an inhibitor of the CYP2C19 enzyme. Patients receiving concomitant Fluzaс and drugs with a narrow therapeutic window metabolized by CYP2C9, CYP2C19, and CYP3A4 should be closely monitored.
Terfenadine. Careful monitoring of the patient is required when terfenadine and fluconazole are used concomitantly at fluconazole doses below 400 mg per day (see sections "Contraindications" and "Interaction with other medicinal products and other forms of interaction").
Candidiasis. Studies have demonstrated an increasing prevalence of infections caused by Candida species other than C. albicans. These are often intrinsically resistant (e.g., C. krusei and C. auris) or show reduced susceptibility to fluconazole (C. glabrata). Such infections may require alternative antifungal therapy after failed treatment. Therefore, prescribers are advised to consider the prevalence of resistance of various Candida species to fluconazole.
Use during pregnancy or breastfeeding.
Women of childbearing potential
Before initiating treatment, the patient should be informed about the potential risk to the fetus.
After a single dose, a washout period of fluconazole, approximately 1 week (corresponding to 5–6 half-lives), should be observed before conception (see section "Pharmacokinetics").
For prolonged treatment courses in women of childbearing potential, the use of contraception should be considered throughout the treatment period and for 1 week after the last dose.
Pregnancy
Observational studies indicate an increased risk of spontaneous abortion in women who received fluconazole during the first and/or second trimester, compared to women who did not take fluconazole or received topical azoles during the same period.
Data from several thousand women who received a cumulative dose of ≤ 150 mg fluconazole during the first trimester of pregnancy do not indicate an increased overall risk of fetal malformations. In one large observational cohort study, the effect of oral fluconazole use during the first trimester of pregnancy was associated with a slight increase in the risk of musculoskeletal disorders, corresponding to approximately 1 additional case per 1000 women who received a cumulative therapeutic dose of ≤ 450 mg compared to women who received topical azoles, and approximately 4 additional cases per 1000 women who received cumulative doses exceeding 450 mg. The relative risk was 1.29 (95% CI 1.05–1.58) for oral fluconazole 150 mg and 1.98 (95% CI 1.23–3.17) for doses exceeding 450 mg.
Available epidemiological studies on the risk of congenital heart defects following fluconazole use during pregnancy provide conflicting results. However, a meta-analysis of 5 observational studies involving several thousand pregnant women who received fluconazole during the first trimester showed a 1.8–2-fold increased risk of congenital heart defects in infants compared to infants of mothers who did not use fluconazole and/or used topical azoles.
Congenital malformations have been reported in infants whose mothers received high doses (400–800 mg/day) of fluconazole during pregnancy for more than 3 months for the treatment of coccidioidomycosis. Among the congenital malformations observed in these children were brachycephaly, ear dysplasia, enlarged anterior fontanelle, femoral bowing, and radiohumeral synostosis. A causal relationship between fluconazole use and congenital malformations has not been established.
Standard doses of fluconazole and short-term fluconazole treatment should not be used during pregnancy, except when absolutely necessary.
High-dose fluconazole and/or prolonged fluconazole treatment should not be used during pregnancy, except for the treatment of life-threatening infections.
Lactation
Fluconazole passes into breast milk and reaches concentrations similar to those in plasma. Breastfeeding may be continued after a single standard dose of fluconazole (150 mg).
The benefit of breastfeeding for the child's development and health, the mother's clinical need for fluconazole, and any potential adverse effects of fluconazole or the mother's underlying condition on the breastfed child should be carefully evaluated.
Breastfeeding is not recommended with repeated use of fluconazole or with high-dose fluconazole therapy.
Fertility
Fluconazole did not affect fertility in male and female rats.
Ability to affect reaction speed when driving vehicles or operating machinery.
No studies on the effect of Fluzaс on the ability to drive vehicles or operate machinery have been conducted.
Patients should be informed about the possibility of developing dizziness or seizures during Fluzaс treatment. If such symptoms occur, driving vehicles or operating machinery is not recommended.
Administration and Dosage
The daily dose of fluconazole depends on the type and severity of the fungal infection. For most cases of vaginal candidiasis, a single dose is sufficient.
If repeated administration is necessary, treatment of infections should be continued until clinical and laboratory signs of fungal activity have disappeared. Inadequate duration of treatment may lead to recurrence of active infection.
Fluconazole is administered either orally or intravenously by infusion, depending on the dosage form. The route of administration depends on the patient's clinical condition. There is no need to adjust the daily dose when switching from oral to intravenous administration or vice versa.
Tablets should be swallowed whole. The drug may be taken independently of food intake.
Adults.
Cryptococcosis.
- Treatment of cryptococcal meningitis: loading dose is 400 mg on the first day. Maintenance dose – 200–400 mg/day. Duration of treatment is usually at least 6–8 weeks. For life-threatening infections, the daily dose may be increased up to 800 mg.
- Maintenance therapy to prevent relapse of cryptococcal meningitis in patients at high risk: the recommended dose is 200 mg/day for an indefinite duration.
Coccidioidomycosis.
- The recommended dose is 200–400 mg/day. Treatment duration is 11–24 months or longer, depending on the patient's condition. For certain forms of infection, especially meningitis, a daily dose of 800 mg may be appropriate.
Invasive Candidiasis.
- Loading dose is 800 mg on the first day. Maintenance dose – 400 mg/day. The recommended duration of treatment for candidemia is usually 2 weeks after the first negative blood culture and resolution of signs and symptoms of candidemia.
Oropharyngeal and Mucosal Candidiasis.
- Oropharyngeal candidiasis: loading dose is 200–400 mg on the first day, maintenance dose – 100–200 mg/day. Treatment duration is 7–21 days (until remission is achieved), but may be extended in patients with severe immunodeficiency.
- Esophageal candidiasis: loading dose is 200–400 mg on the first day, maintenance dose – 100–200 mg/day. Treatment duration is 14–30 days (until remission is achieved), but may be extended in patients with severe immunodeficiency.
- Candiduria: recommended dose is 200–400 mg/day for 7–21 days. Treatment duration may be prolonged in patients with severe immunodeficiency.
- Chronic atrophic candidiasis: recommended dose is 50 mg/day for 14 days.
- Chronic cutaneous and mucosal candidiasis: recommended dose is 50–100 mg/day. Treatment duration is up to 28 days, but may be extended depending on the severity and type of infection or degree of immunosuppression.
Prevention of recurrent mucosal candidiasis in HIV-infected patients at high risk.
- Oropharyngeal candidiasis, esophageal candidiasis: recommended dose is 100–200 mg/day or 200 mg three times per week. Treatment duration is indefinite in immunocompromised patients.
Prophylaxis of candidiasis in patients with prolonged neutropenia.
- Recommended dose is 200–400 mg/day. Treatment should be initiated several days before anticipated onset of neutropenia and continued for 7 days after neutrophil count rises above 1000/mm³.
Genital Candidiasis.
- Acute vaginal candidiasis, candidal balanitis: recommended dose is a single 150 mg dose.
- Treatment and prevention of recurrent vaginal candidiasis (4 or more episodes per year): recommended regimen is 150 mg once every 3 days. A total of 3 doses should be administered (on day 1, day 4, and day 7). After this, maintenance therapy with 150 mg once weekly should be continued for 6 months.
Dermatomycoses.
- Tinea pedis, tinea of smooth skin, tinea cruris, cutaneous candidiasis: recommended dose is 150 mg once weekly or 50 mg once daily. Treatment duration is 2–4 weeks. Treatment of tinea pedis may last up to 6 weeks.
- Pityriasis versicolor: recommended dose is 300–400 mg once weekly for 1–3 weeks or 50 mg daily for 2–4 weeks.
- Dermatophytic onychomycosis: recommended dose is 150 mg once weekly. Treatment should continue until the infected nail is replaced by healthy nail. Healthy nail regrowth typically takes 3–6 months for fingernails and 6–12 months for toenails. However, nail growth rate may vary among patients and depend on age. After successful treatment of long-standing chronic infections, nail appearance may sometimes remain altered.
Geriatric Patients.
Dosage should be adjusted according to renal function (see below).
Patients with Renal Impairment.
Fluconazole is primarily excreted unchanged in urine. No dose adjustment is required for single-dose administration. In patients (including children) with impaired renal function requiring multiple-dose therapy, an initial dose of 50–400 mg should be administered on the first day, depending on the indication. Thereafter, the daily dose (depending on the indication) should be adjusted according to Table 1:
Table 1
| Creatinine clearance (mL/min) |
Percentage of recommended dose |
| > 50 |
100 % |
| ≤ 50 (without dialysis) |
50 % |
| Regular dialysis |
100 % after each dialysis |
Patients undergoing regular dialysis should receive 100 % of the recommended dose after each dialysis session. On days when dialysis is not performed, the patient should receive a dose adjusted according to creatinine clearance.
Patients with hepatic impairment.
Fluconazole should be administered with caution to patients with hepatic dysfunction, as there is insufficient data regarding the use of fluconazole in this patient population.
Children.
The maximum daily dose of 400 mg should not be exceeded.
As with similar infections in adults, the duration of treatment depends on the clinical and mycological response. FluZAK is administered once daily.
Dosage recommendations for children with renal impairment are provided below. The pharmacokinetics of fluconazole have not been studied in children with renal insufficiency.
Children aged 12 years and older.
Depending on body weight and pubertal development, the physician should assess whether the adult or pediatric dosage is optimal for the patient. Clinical data indicate that fluconazole clearance is higher in children than in adults. Administration of 100, 200, and 400 mg doses in adults and 3, 6, and 12 mg/kg doses in children results in comparable systemic exposure.
The efficacy and safety of the drug for the treatment of genital candidiasis in children have not been established, despite extensive data on the use of fluconazole in pediatric patients. If there is a compelling need to administer the drug to adolescents (aged 12 to 17 years), standard adult doses should be used.
Children aged 5 to 11 years.
Mucosal candidiasis: initial dose is 6 mg/kg/day, maintenance dose is 3 mg/kg/day. The initial dose may be administered on the first day to achieve steady-state concentration more rapidly.
Invasive candidiasis, cryptococcal meningitis: dosage is 6–12 mg/kg/day depending on the severity of the disease.
Maintenance therapy for prevention of relapse of cryptococcal meningitis in children at high risk of recurrence: dosage is 6 mg/kg/day depending on the severity of the disease.
Prophylaxis of candidiasis in immunocompromised patients: dosage is 3–12 mg/kg/day depending on the severity and duration of induced neutropenia (see adult dosing).
Children.
The tablet formulation of the drug may be used in this patient population only when children are able to swallow tablets safely, which is generally possible from the age of 5 years (see section "Dosage and administration").
Overdose.
Cases of fluconazole overdose have been reported; hallucinations and paranoid behavior have been reported concurrently.
In case of overdose, symptomatic and supportive treatment should be initiated, and gastric lavage should be performed if necessary.
Fluconazole is predominantly excreted in urine; forced diuresis may accelerate drug elimination. A 3-hour hemodialysis session reduces plasma fluconazole levels by approximately 50%.
Adverse reactions.
Summary of safety profile
Drug reaction with eosinophilia and systemic symptoms (DRESS syndrome) has been reported in association with fluconazole treatment (see section "Special precautions for use"). The most frequently reported (>1/10) adverse reactions were: headache, abdominal pain, diarrhoea, nausea, vomiting, rash, increased alanine aminotransferase (ALT) levels, increased aspartate aminotransferase (AST) levels, increased alkaline phosphatase levels in blood.
The following classification is used to assess the frequency of adverse reactions: very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1000 to <1/100), rare (≥1/10000 to <1/1000), very rare (<1/10000), frequency not known (cannot be estimated from the available data).
Blood and lymphatic system disorders.
Uncommon: anaemia.
Rare: agranulocytosis, leucopenia, neutropenia, thrombocytopenia.
Immune system disorders.
Rare: anaphylaxis.
Metabolism and nutrition disorders.
Uncommon: decreased appetite.
Rare: hypertriglyceridaemia, hypercholesterolaemia, hypokalaemia.
Psychiatric disorders.
Uncommon: insomnia, somnolence.
Nervous system disorders.
Common: headache.
Uncommon: convulsions, dizziness, paraesthesia, taste disturbance.
Rare: tremor.
Ear and labyrinth disorders.
Uncommon: vertigo.
Cardiac disorders.
Rare: paroxysmal ventricular tachycardia of the "torsades de pointes" type, QT interval prolongation (see section "Special precautions for use").
Gastrointestinal disorders.
Common: abdominal pain, diarrhoea, nausea, vomiting.
Uncommon: constipation, dyspepsia, flatulence, dry mouth.
Hepatobiliary disorders.
Common: increased alanine aminotransferase (ALT) levels, increased aspartate aminotransferase (AST) levels, increased alkaline phosphatase levels (see section "Special precautions for use").
Uncommon: cholestasis, jaundice, increased bilirubin levels (see section "Special precautions for use").
Rare: hepatic failure, hepatocellular necrosis, hepatitis, hepatocellular injury (see section "Special precautions for use").
Skin and subcutaneous tissue disorders.
Common: rash (see section "Special precautions for use").
Uncommon: pruritus, drug eruption (including fixed drug eruption), urticaria, increased sweating (see section "Special precautions for use").
Rare: toxic epidermal necrolysis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, exfoliative dermatitis, angioneurotic oedema, facial swelling, alopecia (see section "Special precautions for use").
Frequency not known: drug reaction with eosinophilia and systemic symptoms (DRESS syndrome).
Musculoskeletal and connective tissue disorders.
Uncommon: myalgia.
General disorders and administration site conditions.
Uncommon: increased fatigue, malaise, asthenia, fever.
The presence of the colouring agent Ponceau 4R (E 124) may cause allergic reactions, and methylparahydroxybenzoate (E 218) and propylparahydroxybenzoate (E 216) may cause allergic reactions (possibly delayed-type).
Children.
The frequency and nature of adverse reactions and laboratory abnormalities observed in clinical trials involving children are comparable to those in adults.
Reporting of suspected adverse reactions.
Reporting suspected adverse reactions after medicinal product authorization is important. It allows continued monitoring of the benefit-risk balance of the medicinal product. Healthcare professionals are requested to report any suspected adverse reactions in accordance with local regulatory requirements.
Shelf life. 3 years.
Storage conditions.
Store at temperatures not exceeding 25 °C. Keep out of the reach of children.
Packaging.
50 mg tablets: 4 or 10 tablets in a blister; 1 blister in a cardboard box.
150 mg tablets: 1 tablet in a blister; 3 blisters in a cardboard box.
200 mg tablets: 2 tablets in a blister; 1 or 2 blisters in a cardboard box.
Prescription category. Prescription only.
Manufacturer.
FDC Limited.
Manufacturer's address and place of business.
L-56/57, Phase II-D, Verna Industrial Estate, Verna, Salcette, Goa – 403 722, India.
Similar drugs
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026