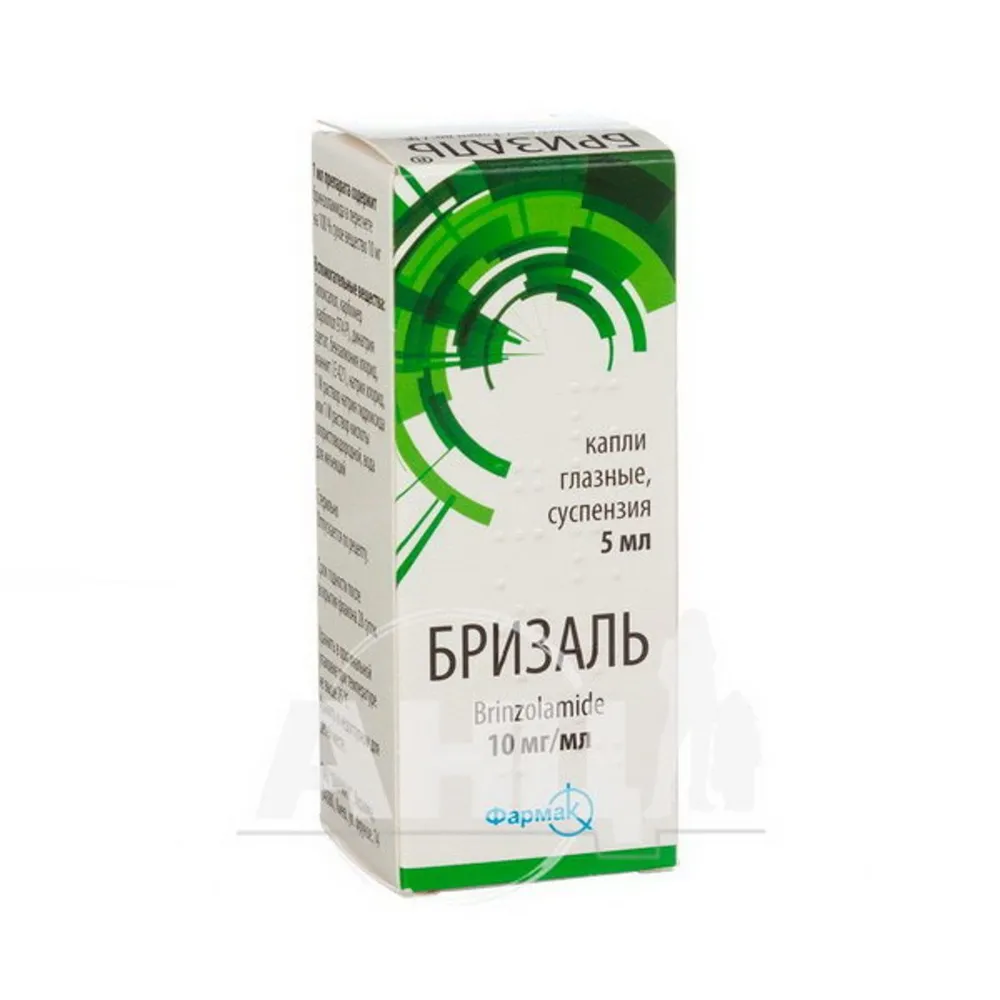
BRIZAL®
UkraineThe drug is indicated for reducing elevated intraocular pressure in ocular hypertension and open-angle glaucoma. It can be used as monotherapy or as adjunctive therapy in combination with other agents.
Frequently asked questions
How should Brizal® be taken correctly?
It is usually recommended to instill 1 drop into the affected eye (or both eyes) 2 times a day. In some cases, the physician may prescribe 1 drop 3 times a day. Shake the bottle well before use. If you are using other eye drops, wait at least 5 minutes between applications.
Can contact lenses be worn during treatment?
Soft contact lenses must be removed before instillation. After applying the drug, you must wait 15 minutes before putting the lenses back in, as the composition of the drops may irritate the eyes and discolor the lenses.
Who should not use this drug?
Brizal® should not be used in case of hypersensitivity to the active substance or sulfonamides, severe renal impairment, or hyperchloremic acidosis. The drug is also not recommended for use in children under 18 years of age and pregnant women.
What are the possible side effects of Brizal®?
Patients most commonly experience a bitter taste in the mouth and temporary blurred vision after instillation. Eye irritation, eye pain, a foreign body sensation, or redness are also frequently encountered. In rare cases, serious skin reactions may occur, so it is important to monitor the condition of the skin.
How can the unpleasant taste in the mouth be reduced?
To reduce the risk of a bitter taste, it is recommended to press the area near the nasolacrimal duct or gently close the eyelids after instillation. This will help minimize the amount of the drug entering the nasopharynx.
How long can the opened bottle be stored?
After opening the bottle, the drug can be used for 28 days.
Instructions for use
INSTRUCTIONS FOR MEDICAL USE OF THE MEDICINAL PRODUCT BRIZAL® (BRIZAL)
Composition:
Active substance: brinzolamide;
1 ml of the preparation contains 10 mg of brinzolamide calculated as 100% dry substance;
Excipients: tyloxapol, carbomer (carbopol 974P), edetate disodium, benzalkonium chloride, mannitol (E 421), sodium chloride, 1 M sodium hydroxide solution or 1 M hydrochloric acid solution, water for injections.
Pharmaceutical form. Eye drops, suspension.
Main physicochemical properties: white or almost white homogeneous suspension.
Pharmacotherapeutic group. Agents used in ophthalmology. Antiglaucoma agents and miotics. Carbonic anhydrase inhibitors. ATC code S01E C04.
Pharmacological Properties.
Pharmacodynamics.
Carbonic anhydrase (CA) is an enzyme found in many tissues of the human body, including ocular tissues. Carbonic anhydrase catalyzes the reversible reaction of hydration of carbon dioxide and dehydration of carbonic acid.
Inhibition of carbonic anhydrase in the ciliary body of the eye reduces the secretion of aqueous humor, primarily by slowing the formation of bicarbonate ions, followed by a decrease in sodium and fluid transport. As a result, intraocular pressure (IOP), which is the main risk factor in the pathogenesis of optic nerve damage and visual field loss due to glaucoma, is reduced. Brinzolamide is a carbonic anhydrase II (CA-II) inhibitor, the predominant isoenzyme in the eye, with in vitro IC50 = 3.2 nM and Ki = 0.13 nM against CA-II.
The IOP-lowering effect of brinzolamide in combination therapy with the prostaglandin analog travoprost has been studied. After 4 weeks of travoprost treatment, patients with IOP ≥ 19 mmHg were additionally randomized to receive either brinzolamide or timolol. An additional reduction in mean diurnal IOP was observed, ranging from 3.2 to 3.4 mmHg in the brinzolamide group and from 3.2 to 4.2 mmHg in the timolol group. In the brinzolamide-travoprost treatment groups, the most frequently observed adverse reactions were mild ophthalmic events, primarily related to local irritation. Adverse effects were generally mild and did not significantly influence decisions to discontinue participation in the study (see also section "Adverse Reactions").
A clinical study of brinzolamide use was conducted in 32 children under 6 years of age diagnosed with glaucoma and ocular hypertension. Some patients had not previously received treatment for elevated IOP, while others were already using other IOP-lowering medications. Patients already receiving IOP-lowering medications did not discontinue their therapy prior to initiating brinzolamide monotherapy.
Based on conventional preclinical safety studies, including repeated-dose toxicity, genotoxicity, and carcinogenicity, no specific risk for humans has been identified with the use of brinzolamide.
In rabbit studies of oral brinzolamide administration at doses up to 6 mg/kg/day (125 times the recommended therapeutic dose for ophthalmic use), no effect on fetal development was observed despite significant maternal toxicity. Similar studies in rats revealed minor reductions in fetal skull and sternum ossification in dams receiving brinzolamide at 18 mg/kg/day (375 times the recommended therapeutic dose for ophthalmic use), but this effect was not observed in dams receiving 6 mg/kg/day. These findings occurred at doses causing metabolic acidosis, reduced maternal body weight gain, and reduced fetal weight. Dose-dependent reductions in fetal weight were observed in dams receiving oral brinzolamide: approximately 5–6% reduction at 2 mg/kg/day and up to approximately 14% at 18 mg/kg/day. During lactation, the no-observed-adverse-effect dose on the fetus was 5 mg/kg/day.
Pharmacokinetics.
After topical ocular administration, brinzolamide is absorbed into the systemic circulation. Due to its high affinity for CA-II, brinzolamide actively penetrates red blood cells (erythrocytes) and demonstrates a prolonged half-life in blood (on average approximately 24 weeks). In clinical practice, the metabolite N-desethylbrinzolamide has been observed, which also binds to CA and accumulates in erythrocytes. This metabolite primarily binds to CA-I in the presence of brinzolamide. Plasma concentrations of both brinzolamide and N-desethylbrinzolamide are low, typically below the lower limit of quantification (< 7.5 ng/mL).
Protein binding in plasma is incomplete (approximately 60%). Brinzolamide is primarily excreted by the kidneys (approximately 60%). Nearly 20% of the dose is recovered in urine as metabolite. Brinzolamide and N-desethylbrinzolamide are the predominant components excreted in urine, along with trace amounts (< 1%) of N-desmethylpropyl and O-desmethyl metabolites.
In pharmacokinetic studies, healthy volunteers received oral brinzolamide 1 mg capsules twice daily for 32 weeks. Systemic inhibition of CA was assessed by measuring CA activity in erythrocytes.
Saturation of erythrocyte CA-II by brinzolamide was achieved within 4 weeks (concentration approximately 20 µM). N-desethylbrinzolamide accumulated in erythrocytes until reaching steady-state concentrations ranging from 6 to 30 µM within 20–28 weeks. Inhibition of total erythrocyte CA-II activity at steady state was approximately 70–75%.
Patients with moderate renal impairment (creatinine clearance 30–60 mL/min) received 1 mg brinzolamide orally twice daily for 54 weeks. Brinzolamide concentration in erythrocytes after 4 weeks ranged from 20 to 40 µM. At steady state, brinzolamide and its metabolite concentrations in erythrocytes ranged from 22 to 46.1 µM and 17.1 to 88.6 µM, respectively.
As creatinine clearance decreased, N-desethylbrinzolamide concentrations in erythrocytes increased, and total CA activity in erythrocytes decreased, while brinzolamide concentrations in erythrocytes and CA-II activity remained unchanged. In patients with severe renal impairment, total CA activity inhibition was greater, although it remained below 90% at steady state.
In studies of topical ocular administration, brinzolamide concentrations in erythrocytes at steady state were similar to those observed after oral administration, but N-desethylbrinzolamide concentrations were lower. Carbonic anhydrase activity was approximately 40–70% of baseline levels.
Clinical characteristics.
Indications.
Brisal® is indicated for reduction of elevated intraocular pressure in:
- ocular hypertension,
- open-angle glaucoma,
- as monotherapy in adult patients who are unresponsive to beta-blockers,
- in adult patients for whom beta-blockers are contraindicated, or as adjunctive therapy to beta-blockers or prostaglandin analogs.
Contraindications.
- Hypersensitivity to the active substance or to any of the excipients.
- Known hypersensitivity to sulfonamides (see also section "Special precautions").
- Severe renal impairment.
- Hyperchloremic acidosis.
Interaction with other medicinal products and other forms of interaction.
No specific studies on the interaction of brinzolamide with other medicinal products have been conducted. During clinical trials, brinzolamide was used in combination with prostaglandin analogs and timolol in the form of ophthalmic drops; no evidence of adverse interactions was observed. Interaction between brinzolamide and miotics or adrenergic agonists has not been evaluated during combined therapy of glaucoma.
Brinzolamide is a carbonic anhydrase inhibitor, and although it is administered locally, it is absorbed systemically. Disturbances in acid-base balance have been reported with oral administration of carbonic anhydrase inhibitors. This potential interaction should be considered in patients receiving Brisal®.
Cytochrome P450 isoenzymes responsible for brinzolamide metabolism are CYP3A4 (major), CYP2A6, CYP2C8, and CYP2C9. Inhibitors of CYP3A4 such as ketoconazole, itraconazole, clotrimazole, ritonavir, and troleandomycin are expected to inhibit CYP3A4-mediated metabolism of brinzolamide. Caution should be exercised when co-administering CYP3A4 inhibitors. Since brinzolamide is primarily eliminated via the kidneys, accumulation is unlikely. Brinzolamide is not an inhibitor of cytochrome P450 isoenzymes.
Special precautions for use
Systemic effects
Brisal® is a sulfonamide-type carbonic anhydrase inhibitor, and although administered locally, it is systemically absorbed. When applied topically, the same adverse reactions characteristic of sulfonamides may occur, including Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN). Patients receiving Brisal® eye drops should be informed about the signs and symptoms of adverse reactions and the need for careful monitoring of skin reactions. If signs of serious adverse reactions or hypersensitivity occur, the drug should be discontinued.
Disturbances in acid-base balance have been reported with oral administration of carbonic anhydrase inhibitors. Since there is a risk of metabolic acidosis, the drug should be used with caution in patients at risk of renal impairment (see section "Dosage and administration").
The use of brinzolamide in preterm newborns (less than 36 weeks of gestation) or newborns under 1 week of age has not been studied. Brinzolamide may be administered to patients with significant immaturity of renal tubules or tubular abnormalities only after careful assessment of the risk-benefit ratio, due to the potential risk of metabolic acidosis.
Oral carbonic anhydrase inhibitors may impair the ability to perform tasks requiring mental concentration and/or physical coordination. Brisal® is systemically absorbed; therefore, such effects may also occur with topical administration.
Concomitant use
In patients receiving oral carbonic anhydrase inhibitors and Brisal®, there is a potential for increased systemic adverse reactions associated with carbonic anhydrase inhibitors. Concomitant use of Brisal® and oral carbonic anhydrase inhibitors has not been studied; therefore, such concomitant use is not recommended (see also section "Interaction with other medicinal products and other forms of interaction").
Brinzolamide has primarily been evaluated in combination with timolol for the combined treatment of glaucoma. Additionally, the intraocular pressure (IOP)-lowering effect of brinzolamide in combination with the prostaglandin analogue travoprost has been studied. Long-term studies on the combined use of brinzolamide with travoprost are lacking (see section "Pharmacodynamics").
Limited experience exists with the use of brinzolamide in patients with pseudoexfoliative glaucoma and pigmentary glaucoma. Such patients should be treated with caution and intraocular pressure should be closely monitored. Studies on the use of brinzolamide in patients with angle-closure glaucoma have not been conducted; therefore, the use of the drug in these patients is not recommended.
The potential effect of brinzolamide on corneal endothelial function in patients with compromised corneas (particularly those with low endothelial cell counts) has not been studied. Direct studies on the use of the drug in patients wearing contact lenses have not been conducted; therefore, careful monitoring is recommended when using brinzolamide in such patients, as carbonic anhydrase inhibitors may affect corneal hydration, and the concurrent use of contact lenses may increase the risk of corneal damage. Careful monitoring is recommended in patients with corneal abnormalities, such as those with diabetes mellitus or corneal dystrophy.
Benzalkonium chloride, commonly used as a preservative in ophthalmic preparations, may cause punctate keratopathy and/or toxic ulcerative keratopathy. Since Brisal® contains benzalkonium chloride, careful monitoring is required during frequent or prolonged treatment in patients with dry eye or corneal damage.
The use of brinzolamide in patients wearing contact lenses has not been studied. Brisal® contains benzalkonium chloride, which may cause eye irritation and is known to discolor soft contact lenses. Contact with soft contact lenses should be avoided. Patients should be advised to remove contact lenses before administering Brisal® eye drops and to wait 15 minutes after instillation before reinserting contact lenses.
The effects of withdrawal that may potentially occur after discontinuation of Brisal® have not been studied; however, a reduction in intraocular pressure is expected to persist for 5–7 days.
Use during pregnancy or breastfeeding
Pregnancy
Data on the ophthalmic use of brinzolamide in pregnant women are lacking or limited. Animal studies have demonstrated toxic effects on reproductive function following systemic administration (see also section "Pharmacological properties"). Brisal® should not be administered during pregnancy or to women of childbearing potential who are not using contraceptive measures.
Breastfeeding
It is unknown whether brinzolamide/metabolites pass into breast milk following topical ophthalmic administration. Animal studies have shown that brinzolamide passes into breast milk in minimal amounts after oral administration.
A risk to newborns and infants cannot be excluded. A decision should be made whether to discontinue breastfeeding or to discontinue/abstain from treatment with Brisal®, taking into account the benefits of breastfeeding for the child and the benefits of therapy for the mother.
Reproductive function
No effects of brinzolamide on reproductive function were observed in animal studies. Studies on the potential effect of brinzolamide on human reproductive function following topical ophthalmic use have not been conducted.
Ability to affect reaction speed when driving or operating machinery
Brisal® has minimal influence on the ability to drive or operate machinery.
Transient blurred vision or other visual disturbances may negatively affect the ability to drive or operate machinery (see also section "Special precautions for use"). If blurred vision occurs after instillation, patients should wait until vision clears before driving or operating machinery.
Oral carbonic anhydrase inhibitors may impair the ability to perform tasks requiring mental concentration and/or physical coordination (see also sections "Special precautions for use" and "Adverse reactions").
Dosage and Administration
When using Brizal® as monotherapy or adjunctive therapy, the dosage is 1 drop into the conjunctival sac of the affected eye(s) twice daily. In some patients, better results may be achieved by administering 1 drop three times daily.
When switching from another ophthalmic anti-glaucoma medication to Brizal®, discontinue the other medication and begin Brizal® the following day.
If more than one ophthalmic medication is used locally, the interval between their administration should be at least 5 minutes. Ophthalmic ointments should be applied last.
If a dose is missed, treatment should be continued according to the prescribed schedule. The dosage should not exceed 1 drop in the affected eye(s) three times daily.
Administration Instructions
For ophthalmic use only.
It is recommended to press gently on the nasolacrimal duct or close the eyelids carefully after instillation. This reduces systemic absorption of ophthalmic medications, thereby minimizing the risk of systemic adverse effects.
The bottle should be shaken well before each use. To prevent contamination of the dropper tip and the contents of the bottle, care should be taken not to touch the eyelids or adjacent surfaces or other surfaces with the dropper tip. The bottle should be kept tightly closed during storage.
Special Patient Groups
Use in elderly patients
No dose adjustment is required for elderly patients.
Use in hepatic and renal impairment
The use of brinzolamide in patients with hepatic insufficiency has not been studied; therefore, the drug is not recommended for treatment in such patients.
Studies on the use of brinzolamide in patients with severe renal impairment (creatinine clearance < 30 mL/min) or in patients with hyperchloremic acidosis have not been conducted. Since brinzolamide and its main metabolite are primarily excreted by the kidneys, Brizal® is contraindicated in such patients (see also section "Contraindications").
Children
The efficacy and safety of Brizal® in patients under 18 years of age have not been established. Available data on use in this patient group are presented in the sections "Special Warnings and Precautions for Use" and "Pharmacodynamics". Brizal® is not recommended for use in children.
Overdose
No cases of overdose have been reported.
Treatment of overdose should be symptomatic and supportive. Electrolyte imbalance and acidosis may occur, as well as possible effects on the central nervous system. Serum electrolyte levels (particularly potassium) and blood pH should be monitored.
Adverse reactions
In clinical studies involving 2732 patients who received brinzolamide as monotherapy or in combination with timolol maleate 5 mg/mL, the most frequently reported adverse reactions considered related to the study drug were dysgeusia 6.0% (bitter or unusual taste, see description below) and transient blurred vision (5.4%) following instillation, lasting from several seconds to several minutes (see also section "Effect on ability to drive and use machines").
The adverse reactions listed below were considered related to the administration of the medicinal product and were classified as follows: very common (≥1/10), common (≥1/100 to <1/10), uncommon (≥1/1000 to <1/100), rare (≥1/10,000 to <1/1000), very rare (<1/10,000), or not known (cannot be estimated from the available data). Within each frequency grouping, adverse reactions are listed in order of decreasing severity. Information on adverse reactions was obtained from clinical trials and spontaneous reports during the post-marketing period.
| System Organ Classes |
Preferred MedDRA Term (version 15.1) |
| Infections and infestations |
Uncommon: rhinopharyngitis, pharyngitis, sinusitis Unknown: rhinitis |
| Blood and lymphatic system disorders |
Uncommon: decreased red blood cell count, increased blood chloride levels |
| Immune system disorders |
Unknown: hypersensitivity |
| Psychiatric disorders |
Uncommon: apathy, depression, mood depression, decreased libido, nightmares, nervousness Sporadic: insomnia |
| Metabolism and nutrition disorders |
Unknown: decreased appetite |
| Nervous system disorders |
Uncommon: coordination disorder, amnesia, dizziness, paraesthesia, headache Sporadic: memory impairment, somnolence Unknown: tremor, hypoaesthesia, ageusia |
| Ophthalmological disorders |
Common: blurred vision, eye irritation, eye pain, foreign body sensation in the eye, eye hyperemia. Uncommon: corneal erosion, keratitis, punctate keratitis, keratopathy, ocular precipitates, corneal staining, corneal epithelial defect, corneal epithelial disorder, blepharitis, eye pruritus, conjunctivitis, eye swelling, meibomitis, photophobia, dry eyes, allergic conjunctivitis, pterygium, scleral pigmentation, asthenopia, eye discomfort, abnormal eye sensitivity, dry keratoconjunctivitis, subconjunctival cyst, conjunctival hyperemia, eyelid pruritus, eye discharge, scaling along eyelid margins, increased lacrimation Sporadic: corneal edema, diplopia, reduced visual acuity, photopsia, ocular hypoaesthesia, periorbital edema, increased intraocular pressure, increased optic disc excavation Unknown: corneal disorder, visual disturbance, allergic eye reactions, madarosis, eyelid disorder, eyelid erythema |
| Ear and labyrinth disorders |
Sporadic: tinnitus Unknown: vertigo |
| Cardiac disorders |
Uncommon: cardiorespiratory distress, bradycardia, palpitations Sporadic: angina pectoris, irregular heartbeat Unknown: arrhythmia, tachycardia, hypertension, elevated blood pressure, decreased blood pressure, increased heart rate |
| Respiratory, thoracic and mediastinal disorders |
Uncommon: dyspnea, epistaxis, oropharyngeal pain, pharyngeal and laryngeal pain, throat irritation, excessive nasopharyngeal mucus secretion, upper respiratory tract cough syndrome, rhinitis, sneezing Sporadic: bronchial hyperreactivity, upper respiratory tract congestion, nasal sinus mucosal edema, nasal congestion, cough, dry nose Unknown: asthma |
| Gastrointestinal disorders |
Common: dysgeusia Uncommon: esophagitis, diarrhea, nausea, vomiting, dyspepsia, upper abdominal pain, abdominal discomfort, stomach discomfort, flatulence, increased intestinal peristalsis, gastrointestinal disorder, oral hypoaesthesia, oral paraesthesia, dry mouth |
| Hepatobiliary disorders |
Unknown: abnormal liver function test results |
| Skin and subcutaneous tissue disorders |
Uncommon: rash, maculopapular rash, skin induration Sporadic: urticaria, alopecia, generalized pruritus Unknown: Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN) (see section Special warnings and precautions for use), dermatitis, erythema |
| Musculoskeletal and connective tissue disorders |
Uncommon: back pain, muscle spasms, myalgia Unknown: arthralgia, limb pain |
| Renal and urinary disorders |
Uncommon: renal pain Unknown: polyuria |
| Reproductive system and breast disorders |
Uncommon: erectile dysfunction |
| General disorders and administration site conditions |
Uncommon: chest pain, discomfort in chest, fatigue, discomfort Sporadic: breast pain, feeling of anxiety, asthenia, irritability Unknown: peripheral edema, malaise |
| Injury, poisoning and procedural complications |
Uncommon: foreign body sensation in the eye |
In clinical studies with brinzolamide ophthalmic drops, systemic adverse reactions such as dysgeusia (bitter or unusual taste in the mouth after instillation) were frequently reported. This reaction was most likely due to the entry of eye drops into the nasopharynx through the nasolacrimal duct. Applying pressure to the tear duct area or tightly closing the eyelids after instillation may reduce the likelihood of this reaction (see also section "Dosage and Administration").
Brinzolamide is a sulfonamide-class carbonic anhydrase inhibitor with systemic absorption. Generally, when systemic carbonic anhydrase inhibitors are used, adverse reactions involving the gastrointestinal and nervous systems, as well as hematological, renal, and metabolic disturbances, may occur. The same types of adverse reactions associated with orally administered carbonic anhydrase inhibitors may also occur with their topical use.
No unexpected adverse reactions were observed in clinical studies combining brinzolamide ophthalmic drops with travoprost. Adverse reactions observed during combination therapy were those previously reported with the use of each drug individually.
Children
During short-term clinical studies, adverse reactions related to the use of this medicinal product were observed in approximately 12.5% of children. Most were mild, non-serious local ocular reactions, including conjunctival hyperemia, eye irritation, eye discharge, and increased lacrimation (see section "Pharmacodynamics").
Reporting suspected adverse reactions
It is important to report suspected adverse reactions after marketing authorization of the medicinal product. This ensures continued monitoring of the benefit-risk balance of the medicinal product. Healthcare professionals are requested to report any suspected adverse reactions via the national reporting system.
Shelf life. 2 years.
Do not use after the expiry date stated on the packaging.
Shelf life after first opening of the container: 28 days.
Storage conditions.
Store in the original packaging at a temperature not exceeding 25 °C.
Keep out of the reach and sight of children.
Packaging. 5 ml in a bottle. 1 bottle per carton.
Prescription status. Prescription only.
Manufacturer. JSC "Farmak".
Manufacturer's address and place of business.
74, Kyrylivska Street, Kyiv, 04080, Ukraine.
Similar drugs
| Brand name | Dosage form | Active substance / Dosage | Manufacturer |
|---|---|---|---|
| BRINEX | drops, ophthalmic, suspension |
|
Centiss Pharma Pvt. Ltd. |
The original data is available in the language of the country of manufacture.
Data source: State Register of Medicinal Products of Ukraine
Data last verified: August 13, 2026